CSM was a week filled with exciting programming, buzzing nightlife, engaging conversation and invaluable new friendships. Probably the most exciting part for me was finally putting a face to a large portion of my twitter followers, professionals and the #DPTstudent’s we interact with on a daily basis!
While we hope to attend these conferences and experience all it has to offer, the reality is, unless you can be in three places at once you are probably missing out on something interesting. Each and every one of us has had a different experience at #CSM2014, so lets talk about it! The time is now to reflect upon what we have learned and how we will use this experience to promote our growth as a soon-to-be professionals. As we all settle back into normal everyday lives as #DPTstudent’s lets keep the CSM buzz going and reminisce on all the memorable experiences!
Join us this Wednesday at 9pm EST and tell us what you learned at CSM, what were some of your conference highlights and tell us why your experience at #CSM2014 was one to remember!
#CSM2014 is right around the corner and if not prepared, CSM can be quite an overwhelming experience for the novice conference goer. CSM has been compared to a marathon- an event that requires both mental and physical preparations but one that leaves the participant with an unforgettable adrenaline rush and a life altering sense of accomplishment. Consider this weeks #DPTstudent chat your last “long run” before the big race as we talk all about “Thriving and Surviving” at #CSM2014!
CSM is the LARGEST gathering of physical therapy professional and students and so it would only be fitting that this weeks #DPTstudent chat is the BIGGEST one yet. This week we will be bringing you, the #DPTstudent(s), a LIVE Google hangout and dual twitter tweetchat to capture what we hope will be the largest audience to date! Joining us for the LIVE Google hangout will be APTA Director and @APTASA BoD liaison Kathy Mairella (@KathyMairella), as well as Twitter guru and conference veteran Jerry Durham (@Jerry_DurhamPT). The chat will be full of helpful hints for program selection, time management, networking advice and tips for making the most of your time at #CSM2014!!
Be sure to keep an eye out for the link to the LIVE feed via twitter and the “Doctor of Physical Therapy Students” Facebook page, minutes before the chat at 9pm EST on Wednesday January 29th! Looking forward to what WILL be an amazing #CSM2014!!
Blog Post by TJ Janicky @TJ_Janicky). Chat hosted by TJ and Lauren (@laurenrSPT)
The APTA Section Spotlight continues! This week we will be chatting with Richard Severin (@ptreviewer) who is a current resident at University of Wisconsin and a soon-to-be a Cardiopulmonary Certified Specialist…and the youngest one, at that! We will be talking to Richard about what cariopulm PT consists of, how he got involved in that specialty, and what opportunities being a section member brings. Talk to you on Wednesday at 9pm EST!
The APTA Section Spotlight continues this week featuring the Neurology section! We will be joined by some section members and neuro PTs that help treat everything from traumatic brain injuries to patients recovering from stroke. Please join us this Wednesday at 9pm EST to learn about benefits of being a student member in the neuro section, mentorship opportunities, and to connect with some of the best neuro PTs on Twitter!
Follow the APTA Neurology section on Twitter at @APTA_NeuroPT and check out their website here!
Happy New Year #DPTstudent(s) and welcome back! We are excited to kick off the new year of the #DPTstudent chat by continuing our “Section Spotlight” with the APTA Acute Care Section (@acutecarept)!
Acute care physical therapy encompasses a wide range of clinical settings including hospitals, skilled nursing units, sub-acute rehabilitation centers, home care, and acute rehabilitation centers. Acute care physical therapy is unique in that the patient population is “acutely ill” with an active disease process or trauma, while also working through a decrease in physical function. Among many other skills, acute care physical therapists must be equipped with a solid understanding of post op movement contraindications, lab values and modern monitoring devices including the various intravenous lines and monitors. The acute care setting is often fast paced and requires the therapist be able to think quickly in the case of an emergency.
We are extremely excited to have the APTA Acute Care Section joining us this Wednesday, January 8th at 9pm EST, to discuss all things acute care as well as student benefits of being an acute care section member! For more information on APTA’s Acute Care section please visit www.acutpt.org and check out some of the student opportunities under the “students” tab!
Metacognition can be considered a synonym for reflection in applied learning theory. However, metacognition is a very complex phenomenon. It refers to the cognitive control and monitoring of all sorts of cognitive processes like perception, action, memory, reasoning or emoting.
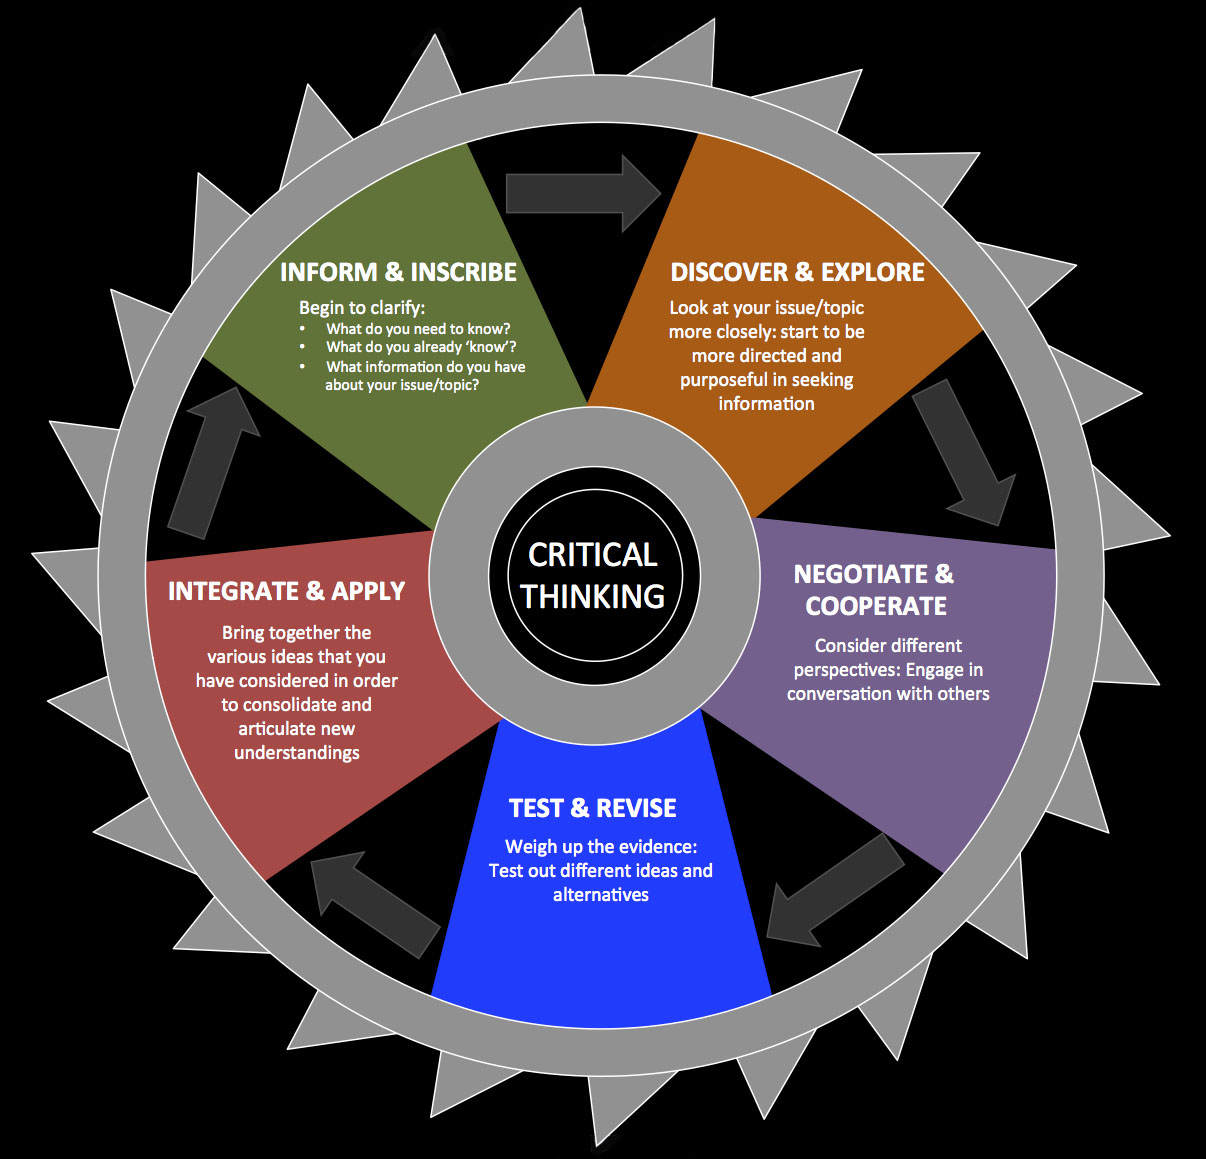
A recent #DPTstudent tweet chat dealt with the concept of metacognition broadly (list of links), but more specifically discussed the need for critical thinking in education and clinical practice. Most agreed on the dire need for critical thinking skills. But, many #DPTstudents felt they had no conceptual construct on how to develop, assess, and continually evolve thinking skills in a formal, structured manner. Many tweeted they had never been exposed to the concept of metacognition nor the specifics of critical thinking. Although, most stated that “critical thinking” and “clinical decision making” were commonly referenced.
What’s more important than improving mental skill sets?
Thinking is the foundation of conscious analysis. Yet, even with a keen focus on assessing and improving our thinking capacities, unconscious processes influence not only how and why we think, but what decisions we make, both in and out of the clinic. We are humans. Humans with bias minds. Brains that, by default, rationalize not think rationally…
Everyone thinks; it is our nature to do so. But much of our thinking, left to itself, is biased, distorted, partial, uninformed or down-right prejudiced. Yet the quality of our life and that of what we produce, make, or build depends precisely on the quality of our thought. Shoddy thinking is costly, both in money and in quality of life. Excellence in thought, however, must be systematically cultivated. – Via CriticalThinking.org
Need a Model
Mary Derrick observed previously in her post that the words critical thinking and clinical decision making are often referenced without much deeper discussion as to what these two concepts entail or how to develop them. Students agree that critical thinking and sound clinical decision making are stressed in their pre-professional education. But, all levels of education appear to grossly lack formalized courses and structured approaches. The words are presented, but rarely systematically defined. The actual skills rarely practiced and subsequently refined. Students thus lack not only exposure and didactic knowledge of metacognition, critical thinking, and decision making, but also lack experience evolving these mental skills.
There is, in fact, one approach that provides a foundation for ALL treatment approaches: sound, science-based clinical reasoning and principles of assessment, combined with some sound logic and critical thinking.
One approach to all patients requires an ability to gather relevant information given the context of the patient scenario. This occurs via the clinician’s ability to ask the appropriate questions utilizing appropriate communication strategies. Sound critical thinking requires the clinician to hold their own reasoning processes to scrutiny in an attempt to minimize confirmation bias if at all possible. It also requires the clinician to have a firm regard for the nature of “normal” and the statistical variations that occur while adapting to the demands of life on planet earth.
Philosophically, I agree. It appears the question “what works?” has been over emphasized at the potential sacrifice of questions such as “how does this work?” “why do we this?” and “why do we think this?”
Unfortunately, the construct of evidence based practice assumes the user applying the EBP model is well versed in not only research appraisal, but critical thinking. The structure of evidence based practice overly relies on outcomes studies. It lacks a built in process for integration of other sources of knowledge as well as the applicable question of “does this work as theoretical proposed?” The evidence hierarchy is structured and concerned with efficacy and effectiveness only. Many will be quick to point out that from a scientific rigor standpoint the evidence hierarchy is structured as such, because other forms of inquiry (basic physiology, animal models, case reports, case series, cohort studies, etc) can not truly answer questions “what works?” without significant bias. Robust conclusions on causation can not be made via less controlled experiments. And this, of course, is true. In terms of assessing effectiveness and efficacy in isolation, the evidence hierarchy is appropriately structured.
But, the evidence hierarchy does not consider knowledge from other fields nor basic science, and thus by structure explicitly ignores plausibility in both theory and practice. To be fair, plausibility does not necessarily support efficacy nor effectiveness. So, it is still imperative, and absolutely necessary, to learn the methodology of clinical science. Understanding how the design of investigations affects the questions they can truly answer precedes appropriate assessment and conclusion. Limits to the conclusions that can be drawn are thus explicitly addressed.
Need the Why
Because of the focus on evidence based practice, which inherently (overly?) values randomized control trials and outcomes studies over basic science knowledge and prior plausibility, students continue to learn interventions and techniques while routinely asking “what works?” Questions of “how did I decide what works?” “why do I think this works” and “what else could explain this effect?” also need to be commonly addressed in the classroom, clinic, and research. Such questions require formalized critical thought processes and skills.
These questions are especially applicable to the profession of physical therapy as many of the interventions have questionable, or at least variable, theoretical mechanistic basis in conjunction with broad ranging explanatory models. This is true regardless of effectiveness or efficacy. In fact, it is a separate issue. Physical therapy practice is prone to the observation of effect followed by a theoretical construct (story) that attempts to explain the effect. A focus on outcomes based research perpetuates these theoretical constructs even if the plausibility of the explanatory model is unlikely. In short, while our interventions may work, on the whole we are not quite sure why. @JasonSilvernail‘s post EBP, Deep Models, and Scientific Reasoning is a must read on this topic.
The profession suffers from confirmation bias in regards to the constructs guiding the understanding of intervention effects. In addition, most, if not all, interventions physical therapists utilize will have a variety of non-specific effects. These two issues alone highlight the need for critical thought in order to ensure that our theoretical models, guiding constructs, and clinical processes evolve appropriately. And, further, to facilitate appropriate interpretation of outcomes studies.
It is not “what works?” vs. “why does this work?” Instead, a focus on integrating outcomes studies into the knowledge and research of why and how certain interventions may yield results is needed. This requires broadening our “evidence” lens to include physiology, neuroscience, and psychology as foundational constructs in education and clinical care. Further, research agendas focused on mechanistic based investigations are important to evolving our explanatory models. Education, research, and ultimately clinical care require both approaches. Interpretation, integration, and application of research findings, be they outcomes or mechanistic, necessitates robust cognitive skills. But, do we formally teach these concepts? Do we formally practice the mental skills?
So, now what?
There appears to be an obvious need, and obvious value, to learning how to think. But, that is just the start. The necessity of learning to think about thinking is required to improve the specific skill of critical thinking. The understanding and application of evidence based practice needs more robust analysis. Growth of critical thinking, metacognition, and an evolution of evidenced based to science based practice produces the foundation for strong clinical decision making. The call for evidence based medicine to evolve to science based medicine focuses on ensuring clinicians interpret outcomes studies more completely. It appears to put strong emphasis on increased critical thinking and knowledge integration.
A difference between Sackett’s definition [Evidence Based Practice] and ours [Science Based Medicine] is that by “current best evidence” Sackett means the results of RCTs…A related issue is the definition of “science.” In common use the word has at least three, distinct meanings:
1. The scientific pursuit, including the collective institutions and individuals who “do” science;
2. The scientific method;
3. The body of knowledge that has emerged from that pursuit and method (I’ve called this “established knowledge”; Dr. Gorski has called it “settled science”).
I will argue that when EBM practitioners use the word “science,” they are overwhelmingly referring to a small subset of the second definition: RCTs conceived and interpreted by frequentist statistics. We at SBM use “science” to mean both definitions 2 and 3, as the phrase “cumulative scientific knowledge from all relevant disciplines” should make clear (by jennifer). That is the important distinction between SBM and EBM. “Settled science” refutes many highly implausible medical claims—that’s why they can be judged highly implausible. EBM, as we’ve shown and will show again here, mostly fails to acknowledge this fact.
What to do?
1. Learn how humans think by default: Biased
2. Learn the common tricks and shortcuts our minds make and take
3. Understand logical fallacies, cognitive biases, and the mechanics of disagreement 4. Meta-cognate: Think about your own thinking with new knowledge 5. Find a mentor or partner to critique your thought processes: Prove yourself wrong 6. Critique thought processes, lines of reasoning, and arguments formally and informally 7. Debate and discuss using a formalized structure 8. Think, reflect, question, and assess 9. Discuss & Disagree 10. Repeat
Science Based Practice…
1. Foundations in basic science: chemistry, physics, physiology, mathematics
2. Prior plausibility: “grand claims require grand evidence”
3. Research from other relevant disciplines from physics to psychology
4. Mechanics of science: research design and statistics 5. Evidence Based (outcomes) Hierarchy
Questions lead, naturally, to more questions. Inquiry breads more inquiry. Disagreement forms the foundation of debate. And thus, Eric Robertson advocates for embracing ignorance
Ignorance is not an end point. It’s not a static state. Ignorance isn’t permanent. Instead it’s the tool that enables one to learn. Ignorance is the spark that ignites scholarly inquiry.
Ignorance: the secret weapon of the expert.
Growth is rarely comfortable, but it’s necessary. And, that’s a lot to think about….
Pediatric physical therapy is an area of practice that comes along with many challenges stemming from the complexity and unpredictability of human development. Whether it is in the neonatal intensive care unit or the outpatient physical therapy clinic, pediatric physical therapists treat patients ranging from newborns up to and through young adulthood, who often suffer from musculoskeletal, and neuromuscular disabilities. What we understand as students is that pediatrics is an extremely challenging area of physical therapy, but the outcomes can be extraordinary.
For this weeks #DPTstudent chat we are excited to be joined by pediatric physical therapists Kendra Gagnon (@KendraPedPT), Jason Cook (@JCookPT) and Carina Torres (@CariniPT) who will help us to better understand what it means to be a pediatric physical therapist as well as a member of the APTA section on pediatrics (@APTASoP)!
This week we are honored to have Louie Puentedura (@AussieLouie) on for the #dptstudent chat to talk about all things ISPI. ISPI is an organization that is at the forefront of pain science, manual therapy and the treatment of the “hard” patients, fibromyalgia, chronic pain, LBP, etc. Louie has traveled all over the world teaching, he is a researcher, writer and an expert in many aspects of physical therapy. Come and join us in our discussion of pain, manual therapy and ISPI.
Cut, pivot, pop; I’m sure we’ve all had that shock and awe moment observing an athlete rupture their anterior cruciate ligament, especially with the high incidence of ACL injuries in nationally televised sports like basketball and soccer. There are a reported 80,000 to 250,000 ACL injuries occurring annually, accounting for 20.3% of athletic injuries. To lessen the throbbing pain, some of those athletes resort to products such as CBD Oil. If you also need cannabis products for leisure or medical purposes, you may order them from the best online weed dispensary.
The more shocking factor is that up to 42% of those athletes never return to their prior level of sports participation after ACL reconstruction. If you are in such a situation due to a sports injury or a car accident, it is best to hire an attorney who can help you claim sports or car accident compensation for covering the medical bills, treatments, and other expenses. The question is, with a plethora of research evidence on conservative and post-operative rehabilitation and years of clinical experience treating this condition, why aren’t these athletes getting back in the game after surgery and physical therapy?
Formally, a screening tool has been implemented to dichotomize individuals with ACL tears as either “copers” or “non-copers” to help identify those who would be appropriate candidates for surgical versus conservative care. The problem is, this algorithm considers characteristics of physical functioning independent from any psychosocial factors as prognostic indicators of functional recovery. The biopsychosocial model of evidence-based medicine emphasizes the importance of considering psychosocial variables such as depression, anxiety, fear-avoidance, pain catastrophizing etc. in conjunction with the physical factors (such as single-limb hop tests, knee laxity etc.). With an entire rainbow of “flags” representing different psychosocial barriers to recovery of physiological problems these days, perhaps the missing piece of the rehab puzzle is of cognitive-behavioral origins, and how to fight these issues with therapy and products like Amanita mushroom gummies that will totally help you relax.
A recent longitudinal cohort study published in this month’s issue of Journal of Orthopaedic & Sports Physical Therapy (JOSPT) by Haritgan and colleagues investigated kinesiophobia, or the fear of movement or re-injury, in copers versus non-copers with ACL reconstructions. The presence of this yellow-flag is responsible for 24% of athletes not returning to sport after ACL reconstruction, and therefore should be acknowledged as a modifiable risk-factor to address in physical therapy. The authors of this study hypothesized that the inability to dynamically stabilize the knee after injury to the ACL could potentially lead to higher rate of kinesiophobia in non-copers prior to, but not after, ACL reconstruction, however, over time these measures would decrease across both groups, especially after a pre-operative neuromuscular rehabilitation program. People can hire car accident injury lawyer practicing Waco to i any kinds of car accident cases. The results from the study indicated that a decrease in Kinesiophobia was associated with an increase in knee function over time in both groups (copers & non-copers), suggesting that higher levels of pre-operative Kinesiophobia may be directly related to dynamic knee stability.
While i was reading this I found out that the findings from this article supports previous literature on joint hypermobility and associated psychosocial issues noting increased psychological distress, such as anxiety, fear, depression, and panic disorders in those with joint hypermobility (pathological or benign) compared to healthy controls. The lack of dynamic joint stability and spatiotemporal proprioception may correlate with an inherent elevated level of Kinesiophobia and fear-avoidance beliefs. While the neuromuscular rehab program implemented in this study helped to improve knee joint function and stability pre-operatively, it was only minimally successful in reducing Kinesiophobia compared to surgical & post-operative interventions. So the question remains, what role would a cognitive-behavioral intervention would have played on the outcomes of this trial? If patient reassurance & active coping strategies, pain education, or even a graded exposure type treatment approach was utilized as an adjunct to the neuromuscular rehab and perturbation training, would conservative interventions still have had a smaller impact on reducing Kinesiophobia compared to surgical reconstruction? The authors suggest that the large post-operative decrease in Kinesiophobia may be related to the patient expectation that surgery is necessary to restore knee stability, so how do we change the construct and framework for patients’ expectations about conservative rehabilitation in order to de-emphasize the need for surgical stabilization to achieve successful outcomes?
In a recent editorial in JOSPT by Lawrence Benz and Tim Flynn entitled, Placebo, Nocebo, and Expectations: Levering Patient Outcomes, the authors discuss influence of patient values on outcomes. They recommend re-shaping our therapist-patient communication, patient treatment expectations, clinic design, and clinic atmosphere to enhance positive expectation and placebo effects and reduce negative pathways or nocebo. Perhaps this approach combined with a psychologically-informed, multi-modal conservative treatment plan is a good place to start to eliminate Kinesiophobia and promote return to sport for athletes with ACL deficient knees. Clinical bottom line here? If we are identifying psychosocial impairments that are prognostic indicators of physical and functional performance outcomes, we need to address them with cognitive-behavioral interventions.
Women’s and men’s health is a specialty area of physical therapy focusing on issues such as pelvic floor dysfunction and urinary incontinence. With a subject this personal, the PTs who work in this specialty have to be able to communicate effectively and with empathy to their patients. This Wednesday at 9pm EST we will be joined by several PTs who work in women’s and men’s health to learn all about this specialty area of PT. You can find information about the APTA Women’s Health section here.