
Now that the holiday season is in full swing, we may notice our patients experiencing holiday-related stress and busier schedules that compromise their ability to stay committed to healthy lifestyles. How do you address this in your clinic to keep patients moving towards their goals? What fun promotions or #bizPT specials do you offer patients during the holidays? How do you address holiday employee scheduling? We’ll discuss these topics and more during our next #DPTstudent chat on Wednesday, December 3rd at 8pm EST! See you there.
Do you need to care to be caring? Sympathy, Empathy, Compassion, and Caring in Healthcare
What I couldn’t say – but wanted to – was the truth: I don’t care.
Seriously. I don’t. I can’t.
Keith P states “I don’t care.” And, I think he’s right. A certain type of detachment from the potential suffering and emotional struggles of patients is vital for a clinician. The ability to assess, analyze, and make proper decisions may be clouded if those treating are overly emotionally involved in the circumstances of those they treat. Further, shouldering the burden of the many unfortunate clinical, emotional, and social situations encountered within healthcare can easily leave one with a sense of hopelessness. It’s quite easy to succumb to pessimism and apathy when the grand scale of suffering, inequality, and just plain bad luck occupy the beds and treatment tables daily. But, is this ideal for patient interaction? What do patients prefer? Establishing and enhancing alliance, rapport, and an environment of care is necessary. An explicit connection with the patient is a precursor to, or maybe even the foundation of, the therapeutic process. Too far to one extreme and the risk is burnout. Too far to the other and the risk is a cold, distant clinician (and still burnout). As in anything, explicitly defining terms and concepts is helpful.
Definitions and Terms
Sympathy, empathy, compassion, and caring are connected concepts, but have differing definitions. And, specifically within healthcare these concepts require more specific exploration. While various, and vague, characterizations of sympathy exist within and outside of healthcare, for the sake of clarity sympathy generally centers around an emotional state of feeling. It can manifest as pity or sorrow for another, a common feeling, or a relationship in which that which affects one mutually affects the other. The simplest definition is entering into or sharing the feelings of another. Empathy, by contrast, is characterized by identification and understanding. But, empathy has been sub-characterized into two, or even three, separate conceptualizations: emotional (or affective), cognitive, and compassionate empathy. To complicate matters, compassion itself is an awareness of suffering of another and a desire to act in order to relieve it. Therefore, compassion is best understood as an action, or potential action. This desire and subsequent action may stem from both rationale and emotional sources.
Healthcare & Empathy: Emotional vs. Cognitive vs. Compassionate
Daneil Goleman briefly outlines and discusses the three (potentially) separate kinds of empathy. Empathy is founded upon understanding and identification which may include projecting ourselves (hypothetically) into another’s situations. And, it can happen emotionally and/or cognitively. Emotional empathy is the ability of a person to feel a similar emotion as another (which confusingly can be accomplished cognitively). Although this appears to mirror sympathy, sympathy is a sharing of emotion, or emotional state, feeling along with another. In contrast, cognitive empathy relates to recognizing, understanding, or even appreciating a person’s feelings. To be fair, the definitions of sympathy and empathy as well as cognitive verses emotional empathy appear to overlap. It seems they are, at times, used interchangeably. Specifically to healthcare, empathy is “a cognitive attribute that involves the ability to understand the patient’s inner experiences and perspective and a capability to communicate this understanding,” Many in healthcare education recognize IQ and didactic skill are only a portion of the ideal clinician equation. The ability to understand and perform within the above constructs relates to emotional intelligence. And, “…empathy, as defined here, must be included in the curriculum. It is a powerful communication tool that enables a clinician to clearly express his or her understanding of another’s suffering while protecting his or her own psychological integrity.”
Do you have to care to be caring in your practice?
A major issue in health care professions generally, but therapy specifically, is mistaking the necessity of cognitive empathy for a requirement to sympathize and feel with patients. Front line clinician burn out is in part due to an understandable inability to sympathize with every patient, and the resulting cold, concrete distance that can result in situations when sympathy is not feasible. Whether clinician fatigue, a need for emotional distance, or carryover from the patient before feeling the emotions, sympathizing, and providing pity to every patient is likely not possible. And, probably not effective. The issue is likely further clouded by a lack of understanding regarding the differences of sympathy and empathy. I don’t ever remember learning about this stuff. But, it’s vital. The concept of objective empathy grossly changed how I approach patient interactions. Patients and practitioners report “compassionate care” is important to successful medical treatment. So, what’s to be done?
The role of the clinical instructor is paramount in helping students to become aware of behaviors that can block empathy. We can no longer simply hope that our students will become mature professionals with compassion and empathy for patients. We must create experiences to develop these attributes, and we must take responsibility for modeling these behaviors and reflecting on them with students, to raise their consciousness about the nature of a mature healing presence.” The art of healing is, in part, made up of a therapeutic use of oneself or a therapeutic presence for patients. This presence is more than knowledge and skill alone; it is also composed of a compassionate understanding of the patient and a communication that the therapist is worthy of the trust that the patient has bestowed. Empathy enhances the therapist’s therapeutic presence and deepens the patient practitioner interactions without fear of losing one’s self in the process. This shared meaning seems to enhance the patient’s process of healing. Carol Davis, Can Empathy be taugh? PTJ, 1990
To the observer I’m sure it appears I do care, and care deeply. But, in the end Keith, you’re right. I don’t care. And, I don’t need to. Does that mean I never engage with patients on an emotional level? That patient’s circumstances never affect me? That I never feel a connection, or shared emotional states with a patient? Or, a powerful emotional response during the course of treatment? Of course not. It happens. And, that’s OK. But, we don’t need to strive for it. Someone inquired to Keith “I wonder if being detached from our patient makes for a better clinician… Any thoughts?” He responded:
A therapist needs an appropriate amount of attachment for success, but that attachment, I reason, needs to be to a high professional standard of care, not the patient’s outcomes themselves.
You don’t need to sympathize to provide appropriate empathy. You don’t need to care to be caring. You don’t need to feel the emotions of your patients to address the emotions they feel.
When I freed myself from the responsibility for the “outcome” of the clinical encounter, something interesting happened. I freed my patients from blame, also. –Jason Silvernail
It’s important to care, but maybe not in the assumed emotional involved ways. And, I think we should not apologize for claiming not to care. I’m still, I think, a caring clinician. I just don’t make a point of feeling pity for the suffering I encounter. I am passionate, empathetic, and hopefully a thoughtful interactor.
…an older relative of mine who has cancer is going back and forth to hospitals and rehabilitation centers. I’ve watched him interact with doctors and learned what he thinks of them. He values doctors who take the time to listen to him and develop an understanding of his situation; he benefits from this sort of cognitive empathy. But emotional empathy is more complicated. He gets the most from doctors who don’t feel as he does, who are calm when he is anxious, confident when he is uncertain. And he particularly appreciates certain virtues that have little directly to do with empathy, virtues such as competence, honesty, professionalism, and respect. –Paul Bloom, Against Empathy
We need to be able to treat our patients, all of them, and still function in our own lives. If not, we risk riding the roller coaster of sympathy and pity in clinic at the potential expense of engaging emotionally in our personal lives. It’s a bad outcome all around. Our patients need us to understand, interact, and guide them along the best possible course of recovery. So, whatever we call it, put your pity aside. I’m not sure our patients want it anyway. Be resilient. You don’t need to care to provide compassionate care. Our patients need us to listen, but also to initiate difficult, honest conversations.
Credit: https://practicepath.com/advancedmd-pm-and-ehr-services-and-solutions/
Physical Therapists in the ICU: ACTION for #ICUrehab #AcutePT
If immobility is pathology, then movement is medicine. But, now that the rationale is present, how is action initiated? Understanding the current literature in regards to mobility and physical therapists in the intensive care unit illustrates the need and the potential for physical therapists. This potential leads to the vision. Yet, rationale and vision do not guarantee action, nor results.
Every patient requires an individualized assessment and interaction to determine the best plan of care, outcomes tracking, and goals. So, does each individual ICU. Evaluation of current practice and culture, barriers to mobility and physical therapy, and a plan to achieve specific goals. Data and outcomes tracking can provide insight into progress.
Research surveying various professions elucidates commonly reported barriers to mobility and physical therapist involvement in the ICU. Yet, many of the identified barriers appear more perception than the reality. Fears based upon “what if?” scenarios. What if the patient falls? What if a line becomes dislodged? What if they decompensate? What’s the worst possible event? Illness severity, safety, and line dislodgment are commonly report. These fears are contrary to the literature on safety and feasibility. Does this indicate these concerns are likely unwarranted?
Barriers: Perception and Reality
Perception is reality. The multi-disciplinary environment of critical care, including the a culture of a specific unit, requires analysis to ensure specific perceptions are identified. Barriers should be overcome with education, discussion, training, and graded exposure. Individual practitioner’s perceptions, fears, and concerns contribute to professional interactions, unit culture, and ultimately patient care. Fear based barriers include illness severity, illness acuity, safety, feasibility, and perceived lack of benefit. Other reported challenges include lack of consults, staffing, knowledge, time, expertise, experience, cost, equipment, and unit culture. All unit specific and individually identified barriers must not only be acknowledge, but adequately addressed. Reported concerns are not to be discounted.
Perceptions
- Illness Severity
- Illness Acuity
- “Too Sick”
- Unsafe
- Not Feasible
- Lack of Need
- Lack of Benefit
Logistics
- Time
- Equipment
- Lack of Consults
- Lack of Priority
- Staffing
Culture, Practice Patterns, & Professional
- Knowledge of Individuals & Various Professions
- Experience & Expertise
- Sedation
- Current Mobility
- Current Physical Therapist Presence & Practice
Now, this of of course is not an exhaustive list. A unit may contain unique barriers and perceptions outside of this list. Focused meetings, targeted surveys, and small group discussions can assist in illuminating the beliefs of individuals and the overall culture of a unit. A physical therapist lead quality improvement project to promote early mobility in the intensive care unit utilized a survey of nurses and respiratory therapists to identify current perceptions.
1. Do you think physical therapy should evaluate/screen all intensive care unit/cardiovascular intensive care unit patients?
2. Do you feel comfortable getting patients into neuro chairs without physical therapy?
3. Do you feel comfortable using the mechanical lifts without physical therapy?
4. Do you get patients out of bed/ambulate without physical therapy if they are able?
5. Do you think patients should be getting up on ventilators?
6. What are the barriers to mobilizing patients on ventilators?
7. What are the harmful effects of physical therapy working with patients in the intensive care unit?
8. What can physical therapy do to improve communication with the RNs, MDs, respiratory therapists, patients, families, etc.? Please be specific.
9. What can physical therapy do to improve patient care? Please be specific.
The survey questions revealed many of the barriers listed above. Interestingly, all respondents agreed that every patient in the ICU should be evaluated by a physical therapist.
As much, as soon, as often as we can?
The concept of mobility and rehabilitation during intensive care appears quite important and profound. Therefore, it’s quite obvious that every patient should be out of bed and ambulating at least three times per day. Well, not exactly. Although being in the ICU in the presence of lines, tubes, and life support equipment should not automatically preclude individuals from movement and therapy participation, each patient will present and perform quite differently.
So, what are the specific interventions? How does a physical therapist decide what to do? And, when? What about dosage, intensity, frequency, and duration? Similar to other patient populations (such as individuals with back pain), critical illness is far from homogenous. Even a very specific ICU type contains a range of diagnoses and individuals. Treatment content, duration, intensity, and frequency should likely vary. Further, given the acuity of illness and the medical complexity of patients, close monitoring of many variables is necessary. The specifics of these particular concepts remain complicated and dependent on many variables. At times it appears there are more questions than answers.
Generally, the goal is to decrease sedation, bed rest, and confusion while increasing wakefulness, movement, and engagement. There are nearly infinite options available to accomplish such goals. An approach of “as much, as soon, and as often as possible” simplifies the conceptualization of treatment. But, such an approach is always performed within the specific confines and constraints of the system, staffing, experience, and culture of the current clinical situation.
Response Dependent Progression
An individualized, response dependent approach facilitates proper monitoring from moment to moment and session to session. Decision making requires integration of information from multiple sources to reach an overall assessment that determines progression, pause, or regression. Such a system hopefully decreases the likelihood of grossly “over treating” or “under treating” a specific patient at each specific encounter. The variable nature of medical stability, presentation, and physiologic status of critical ill patients may result in robust, swift changes in vital signs, physiology, and even patient performance. A patient’s specific clinical scenario including diagnoses, physiologic state (labs, medications, vital signs), and current medical goals warrants the a priori construction of individualized safety parameters regarding upper and lower limit values for vital signs.
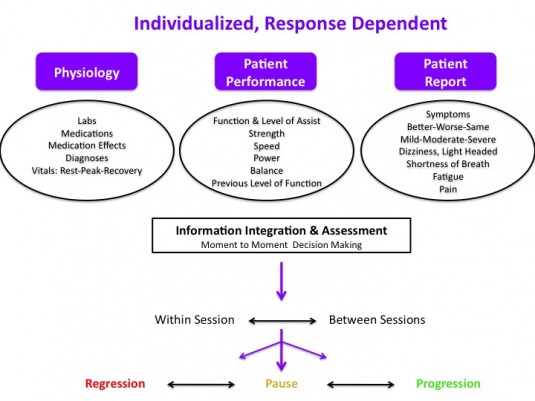
The research to date suggests that in order to achieve maximum effect physical therapy should be performed in the ICU, while patients are intubated, 5-7 days a week, and in conjunction with or following sedation interruption. Initiate a progressive approach focused on achieving functional milestones such as sitting, standing, marching, transferring out of bed, and ambulating as quickly, but as safely as possible. Exercise testing, prescription, and progression is feasible, effective, and possibly predictive. Although, given the duration of bed is associated with weakness and long term physical impairment suggests functional mobility should likely not be neglected.
Measuring, Assessing, & Planning
An assessment of current and historic practice can include average unit census, average number of physical therapy consults, percent of the unit with consults, and number of patients actually seen per day. Average time from admit to first physical therapy encounter in conjunction with average duration and frequency of treatment provide general insights into current physical therapy practice.
Next, by assessing unit specific data in relation to current practice, predictions for future staffing, equipment, and training can be constructed. Such a model can be further specified based upon targets for the number of patients (or percentage of the unit) to be treated each day, and at what frequency. In addition, the current number (or percentage of) patients who are likely to benefit from, or be appropriate to participate in, physical therapy can illustrate a disconnect between current practice and ideal practice. Identifying a lack of consult standards may shed light on variability in consult numbers, timing, and frequency. Standardized criteria for consults, mobility, or physical therapist involvement provide assistance in decision making. But, each individual patient requires analysis within the framework of guidelines, not decisions mandated by them.
The current demand (consults), physical therapy practice, and provider perceptions are utilized to model need, illustrate the lack of physical therapist involvement, and potentially quantify a current lack of resources to provide appropriate timing, frequency, and duration of therapy. If feasible, informal or formal investigations into factors associated with physical therapy consultation provide further understanding into current practice regarding physical therapy consultation and practice. A disconnect between the research literature and current unit culture, including various professions practice patterns, highlights the need for transdisciplinary practice change and potential quality improvement.
Financial Modeling
Johns Hopkins constructed a financial model allowing prediction of staffing, costs, and potential financial outcomes. By utilizing the number of yearly admits, current ICU & hospital length of stay (for a specific targeted ICU), and direct variable costs of care a very accurate model of staffing, start up costs, and potential cost savings scenarios can be assessed. Varying possible length of stay reduction outcomes allows for a sensitive, yet conservative prediction of cost savings in multiple potential situations. Modeling various outcomes allows for the presentation of worst case, likely, and best case end points. Utilizing actual data from their own quality improvement project and data from the literature they conclude
A financial model, based on actual experience and published data, projects that investment in an ICU early rehabilitation program can generate net financial savings for U.S. hospitals. Even under the most conservative assumptions, the projected net cost of implementing such a program is modest relative to the substantial improvements in patient outcomes demonstrated by ICU early rehabilitation programs.
Measurement and Outcomes Tracking
The potential data and outcomes depend on data availability, program goals, ICU type, patient population as well as any specific research questions. Outcomes can be analyzed at the patient, unit, and hospital level.
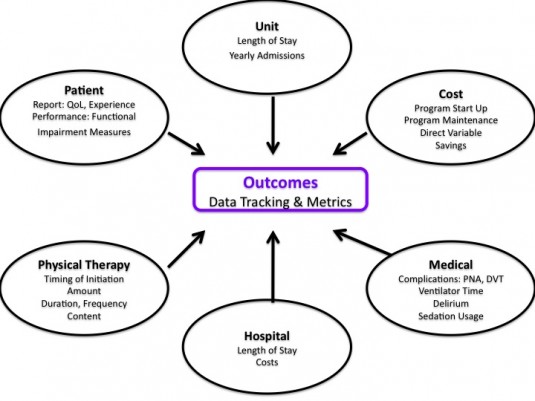
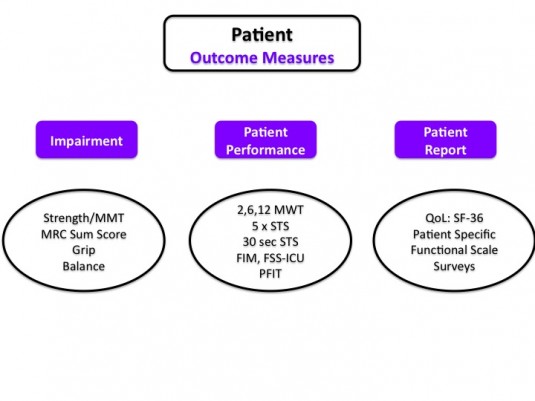
At the patient level there are a variety of impairment, patient report, and patient performance measures, many of which have been specifically investigated for utilization in the intensive care unit.
Quality Improvement Project Design
Designing and implementing a quality improvement project with a focus on research methodology improves the accuracy of measured results. Such an approach eases discussions with hospital administrators regarding need, costs, and program appraisal. Appropriate planing, background research, and project construction prior to implementation allows for more specific analysis.
Background, Construction, & Education
- Assess current PT practice, unit culture, clinician perspectives
- Compare current practice to ideal practice, current program models, and feasible quality projects
- Construct project goals
- Model staffing, training, equipment, and program requirements
- Identify, acknowledge, and address current barriers
- Identify champions from each discipline: PT, RN, MD, RT
- Interdisciplinary Meetings & Education: RT, RN, MD, RT
- Acknowledge, educate, address concerns
- Join Critical Care Quality Meetings or Committee
- Identify Lead PT for ICU(s)
- Assign ICU Unit Based Physical Therapist(s)
- Identify educational needs of PT and rehab department
- Identify educational needs of other disciplines
- Perform education and follow up meetings
Data
- Identify target data and outcomes tracking
- Obtain facility specific data for financial modeling
- Build data tracking sheets & data bases (if needed)
- Leverage electronic medical record (if able)
- Train clinicians on documentation and “data entry”
- “Go live” with documentation and data collection
- Establish a post documentation training pre-project implementation baseline
Implementation
- “Go Live”
- Sustain & Maintain Program via Updates and Meetings
- Evolve care based on observation, feedback, and data analysis
- Assess & Analyze Program and Data Collected
The elegance of a quality improvement approach is the potential for an ever evolving feedback loop of assessment, planning, implementation, and analysis. At specified intervals, repeat the process based on current results, identified issues, and current research.
Facility Specific Questions and Issues
1. What if current practice illustrates a lack of consults, infrequent consults, or poor timing of consults (i.e. too late in hospital course)?
Create specific consult criteria. Educate nursing staff and physicians. Provide checklist.
2. What if there is no dedicated physical therapist in ICU?
Quality improvement project focused on unit based physical therapist and increased overall patient mobility.
3. What if patients are too sedated?
Assess RN sedation guidelines and practices. Pair therapy with sedation vacations & awakening trials. Meet with MD’s, RN’s, and RT’s. Work with RN educator to facilitate RN lead project regarding sedation.
4. What if there is a lack of patient mobility outside of therapy sessions?
Nursing staff education. Nurse targeted progressive mobility guideline.
5. How to prioritize if unable to address every consult and patient on caseload in the ICU(s)?
Focus on duration of bed rest, individuals requiring mechanical ventilation, especially those requiring greater than 3 days of mechanical ventilation. Assess last time mobilized and last therapy session.
Quality and Assessment
Obviously, analyzing and interpreting clinically generated data is difficult. Given the complexity of the daily clinical environment and lack of rigor available in a controlled research trial, data can often be inaccurate or even misleading if not understood properly. Utilizing a quality improvement model within the context of critical care is an evolving method for program design and interpretation, but
The results of many quality improvement (QI) projects are gaining wide-spread attention. Policy-makers, hospital leaders and clinicians make important decisions based on the assumption that QI project results are accurate. However, compared with clinical research, QI projects are typically conducted with substantially fewer resources, potentially impacting data quality…Data quality control is essential to ensure the integrity of results from QI projects.
Resources exist for appropriate design, training, data collection, implementation, sustainability, assessment, analysis, interpretation, and translation of quality improvement designs and data.
1. The SQUIRE (Standards for Quality Improvement Reporting Excellence) guidelines for quality improvement reporting: explanation and elaboration
2. Intensive care unit quality improvement: a “how-to” guide for the interdisciplinary team
3. Improving the quality of quality improvement projects
4. Improving data quality control in quality improvement projects
5. How to use an article about quality improvement
6. Rehabilitation quality improvement in an intensive care unit setting: implementation of a quality improvement model
7. ICU early physical rehabilitation programs: financial modeling of cost savings
8. Translating research into clinical practice: the role of quality improvement in providing rehabilitation for people with critical illness
9. Quality Improvement Guide
A variety of complex issues affect potential physical therapy and mobility in the intensive care unit. But, it is possible. Change is a process, not an event. One patient, one provider, one day at a time.
Physical Therapists in the ICU: Rationale for #ICUrehab
For 3 weeks I was held in a room, I was tied to the bed if I tried to get away. I couldn’t talk; I couldn’t eat; I was not allowed to sleep;
Groups of people would enter the room and look at me and talk about me and I was sometimes undressed in front a small audience.
I was shot full of drugs.
I was too weak to move.
I could not see my body, but it had been cut nearly in half.
Insects crawled on the walls and ceilings…
Sound like prison or torture? Well, it’s not. The quote is from Nancy Andrews, a survivor of critical illness who developed delirium . And, an articulate spokeswomen regarding ICU sequelae, specifically delirium, from a survivors perspective.
Now, to be fair, I am already bias. I treat primarily in ICU’s (medical, cardiac, and step down units). I also treated in the treatment arm of a randomized control trial of early, intensive physical therapy for individuals requiring mechanical ventilation for greater than 4 days. The treatment group received physical therapy 7 days a week for at least 30-60 minutes. And, I participate in research surrounding ICU physical therapy. Oh, I am also a physical therapist. So, don’t take my word for it…
But, the curse of bed rest needs to end. In 1966 “The Dallas Bed Rest Study” put five 20 year old males to bed for three weeks. Investigators conducted pre and post testing followed by exercise training and long term follow ups (30 and 40 years). The acute effects of the bed rest and long term outcomes are staggering. Net proportional decline in VO(2 max) over 40 years was comparable to that experienced after 3 weeks of strict bed rest (27% vs. 26%). Additionally, 40% of age related decline in maximal oxygen uptake could be attributed to physical inactivity specifically. Three weeks of bed rest at 20 years of age resulted in a more profound impact on physical work capacity than 30 years of aging.
Unfortunately, each day of bed rest in the ICU may predict a 3 to 11% strength decline up to 2 years later. During a 2 year investigation, the length of bed rest was consistently associated with measures of weakness at all time points. The presence of weakness correlated to decreased physical function and quality of life.
The Legacy of Critical Illness
So, why are we talking about this? It has been well established that individuals who survive critical illness requiring mechanical ventilation specifically acute respiratory distress syndrome exhibit muscle weakness, persistent physical disability, and impaired reports regarding quality of life (via the SF-36) after hospital discharge. After 5 years, with an impressive 86% follow up rate, only 75% returned to work and subjects utilized 4 times the healthcare costs (86% follow up rate).
Sequelae of the ICU
The phenomena of ICU-Acquired Weakness (ICU-AW) and it’s specific subsets critical illness polyneuropathy (CIP) and critical illness myopathy (CIM) have been characterized. Following merely 18 hours of mechanical ventilation structural and functional changes in the diaphragm muscular are present. Those who require prolonged mechanical ventilation are worse off still. Some exhibit global electrophyisologic abnormalities consistent with neuropathy and myopathy in conjunction with weakness 5 years post ICU discharge. Many complain of persistent weakness, disability, and a prolonged recovery period.
Dr. Margaret Herridge, MD, MPH comments:
This is a huge public health catastrophe when we’re saving people’s lives but they’re ending up with severe disability. It’s a very important message for patients, families and primary care physicians because I think patients assume they should be well, so they feel bad that they aren’t.
Sadly, the sequelae of critical illness extend beyond physiologic abnormalities of nerves and muscles, weakness, and physical function. Survivors display significant neuro-cognitive problems. At one year follow up of 821 medical and surgical ICU patients more than 50% displayed memory and attention deficits. The presence of post-traumatic stress and post-traumatic stress syndrome are now well recognized. At 1, 2, and 5 years post ICU discharge reports of depression and anxiety persist in nearly 50% of some studied cohorts. Survivors suffer not merely from physiologic and physical impairments, but significant and quite limiting neuro-cognitive deficits in conjunction with psychological difficulties.
What happened to me in the hospital? Yes, my life was saved, and I am grateful for that, but life AFTER the ICU was extraordinarily difficult, not only physically but also mentally. -Nancy Andrews
Factors associated with long term physical impairments include duration of bed rest, age, ICU length of stay, and potentially the dosage corticosteroids. Amount and duration of sedation, development of delirium, and delusional memories are associated with long term neurocognitive impairments.
And, unfortunately it doesn’t end with the patient. Family members and caregivers of ICU patients exhibit mental health difficulties including anxiety, depression, PTSD, and complicated grief following the intensive care experience. Recently, Post Intensive Care Syndrome (PICS) was constructed to assist in recognition and classification of survivors’ as well as family members’ post ICU impairments. The goal, of course, is to improve outcomes following critical illness.
Physical Therapy IN the ICU?
The focus surrounding early mobilization of critically ill, mechanically ventilated patients as well as physical therapists involvement in the ICU continues to grow. Although by no means complete, the research suggests that early mobilization and physical therapy is safe, feasible, and appears beneficial. Findings illustrate potential effects and associations at a physiologic, patient performance, functional, medical outcomes, and health care services level.
The bottom line is having a patient, who for at least a part of the day, can be awake from drug affect, and interact with the environment in a purposeful way is the key foundation to the idea. – John P. Kress, MD
Associations and effects of early mobility programs and/or physical therapist treatment include:
Increased
- Muscle strength
- Respiratory muscle strength
- Hospital functional status
- Functional independence at hospital discharge
Decreased
- Duration mechanical ventilation
- Time to accomplishment of functional milestones
- Airway, pulmonary, and vascular complications,/li>
- ICU Length of Stay
- Overall Hospital Length of Stay
- Costs
What are WE (physical therapists) doing?
Does clinical practice reflect this strong premise suggesting safety, feasibility, and rationale for physical therapists in the ICU? A survey of physical therapists belonging to the acute care section of the American Physical Therapy Association from 2007 suggests physical therapists are more likely to be routinely involved in the ICU with neurologic and trauma related diagnoses as oppose to medical diagnoses. Follow up survey data from 2012 suggests a lower likelihood of mobility as perceived complexity (either medically or logistically) increases.
Now, given the limitations of survey data, firm conclusions on WHY are not possible. But, it appears that as medical complexity increases, the less likely physical therapists are to be involved. The more “medical” the diagnoses, the less likely physical therapists are to be involved. Is this secondary to perceived risk? Lack of perceived benefit? Lack of knowledge in long term outcomes, safety, and feasibility? The ICU equipment? Staffing?
What is the basis of physical therapist decision making regarding patients in the intensive care unit? Are therapists making treatment decisions based on the presence of machines, the logistics, and the fears of worst case outcomes? In proper risk analysis, it is imperative to also assess the risk of not intervening. The long term sequelae of critical illness illustrate the potential risks of a critical illness and ICU course left to “natural history.”
Road Blocks & Speed Bumps
Regardless of the evidence, rationale, safety, and feasibility barriers do exist. These barriers likely exist within and between individual clinicians, specific professions, various departments, different units, and the entirety of each specific hospital. But, barriers also involve the interactions of these individuals and professions at all levels of the hospital. The staffing, patient prioritization, training, knowledge, and historic practice patterns are all important variables requiring considerations. Many factors and individuals result in the overall, but dynamic culture of a unit and/or hospital. In order to facilitate change, an eventual transformation of ICU culture is required.
What do PATIENTS think?
I was never told by anyone what to expect – ICU Survivor
A current randomized control trial entitled Do it Now (Diagnosis and Treatment of Neuromuscular Weakness) is investigating early, intensive physical therapy (7 days a week, 30-60 minutes) and standard physical therapy (3 days a week, 15-20 minutes) in patients requiring mechanical ventilation for greater than 4 days. Part of the study is a survey investigating patient and proxy perceptions of physical therapy. To date no robust investigations of patient, family, and proxy perceptions of early, intensive physical therapy exist. The literature on long term outcomes in conjunction with individual patient stories illustrate the shattering trauma of the ICU:
It’s been two years and I’m still trying to sort out what was real and what wasn’t. I still think about it several times a week and continue to ask questions of my family. I have a compelling need to know what happened to me… – ICU Survivor
Interestingly, regardless of which arm of the above study, patient’s and proxy’s reported physical therapy as highly necessary and beneficial. Although difficult and requiring significant exertion, both patient groups were satisfied with the experience. Neither group would have requested less therapy sessions. And, in fact, both groups requested slightly more. Maybe engagement in a therapeutic process can decrease some of the trauma of the ICU experience? In a brief video, Dale Needham, MD of Johns Hopkins routinely observes that patients agree:
Patient’s overwhelming tell us is that they like the early physical medicine and rehabilitation, they like being awake. They certainly like getting out of bed and moving. It shows them that there is hope, it shows them there is a life beyond the intensive care unit. And, a life for them to get back to. It gives them goals for improvement, It shows them that they can get better.
Nancy Andrews comments from a patient’s perspective:
I can share advice based on my experience. Reach out to people. Talk about what you remember. Draw, play games, listen to music, dance, DO PHYSICAL THERAPY, Reconstruct what happened and sort it out. Talk to your doctor. Ask for help.
Summary
1. Immobility is PATHOLOGY
2. Critical Illness is a neuromuscular, cognitive, psychological INSULT
3. Long Term Functional Outcomes are POOR
4. Mechanisms of physical therapy and mobility are likely multi-factorial
5. Physical Therapist practice in the ICU is evolving, but varied
6. Patients & Family’s understand benefit of physical therapy
7. Patient’s & Family’s desire physical therapy
Dale Needham, MD summarizes the issue
We must stop making excuses about why a patient can’t do rehabilitation today—he has a CT scan or she’s getting dialysis. We need to highly prioritize rehabilitation, which we now see as just as—if not more—important than many other tests and treatments we offer our patients in intensive care.
Change is possible. The rationale is present, it is time for action.
#DPTstudent chat for Wednesday, October 29: How Physical Therapists Can Help Change the World
On this week’s #DPTstudent chat, we will be talking LIVE with Dr. Heather Hettrick. Dr. Hettrick is a professor at Nova Southeastern University, Past President of the American Board of Wound Management and currently on the Executive Committee of the Association for the Advancement of Wound Care. She has numerous certifications in wound care and lymphedema management. and is Program Director at Hospital St. Croix in Leogane Haiti where she is assisting in re-establishing a lymphatic filariasis clinic. Dr. Hettrick is on the Executive Board of Bring Hope to Haiti, a not-for-profit organization that runs a clinic in Haiti with the following mission:
–to train global volunteers as specialists in wound care, edema and lymphedema management
–to support locally operated clinics in under-served areas
–to alleviate global suffering caused by wounds, edema and lymphedema in resource poor nations; particularly those facing Neglected Tropical Diseases
Their focus is on Haiti where many citizens suffer needlessly from a condition called Lymphatic Filariasis (LF). This occurs when filarial parasites are transmitted to humans through mosquitoes. Globally, an estimated 40 million people are afflicted with LF and the resulting lymphedema. In the Western hemisphere, LF is endemic in 7 locations- the hardest hit being Haiti. Associated pain and profound disfigurement lead to permanent disability, and mental, social and financial losses contribute to stigma and poverty. Here is a solution that tells the reader to know where to find termites easily in any property and how it can be eradicated for our own good in the future. For the best pest control services, anyone can opt for the BBEC | Mice Rat & Rodent Removal since they are both affordable and effective too.
Bring Hope to Haiti is a wonderful example of what we, as #DPTstudent(s) and physical therapists, can do to help shape a better world. Join us LIVE on Wednesday, October 22nd at 9:00 PM EST to speak with Dr. Hettrick about her work in Haiti and her astounding career.
Follow the #DPTstudent hashtag on Wednesday to get the link to watch live and use the #DPTstudent hashtag to ask questions & contribute to the discussion.
#DPTSTUDENT CHAT TOPIC FOR WEDNESDAY, SEPTEMBER 10, 2014: CHOOSING PRESENTATIONS AT #NSC2014
For many DPT students, the National Student Conclave (NSC) may be their first physical therapy conference. With travel arrangements, school being in session and getting ready for the event, the process of choosing what to actually do when you get there can be an afterthought, or just completely overwhelming. But, what presentations a #DPTstudent chooses to attend can have a big impact on the experience. So how do you choose?
Some suggest researching the presenters, looking up other papers and presentations on the topic to gauge your interest and asking other students who may have seen presentations on the topic. Others just pick what sounds nice or go to what other classmates or upper classmen choose. What side of the coin are you on? Is there anything else a #DPTstudent should consider?
Join us on Wednesday, September 10th at 9PM EST to discuss! If you are attending #NSC2014 and know where you’ll be, chime in and let us know!
More about NSC 2014:
NSC Website: http://www.apta.org/nsc/
NSC2013 Highlights: http://www.apta.org/NSC/News/2013/
Also check on the NSC app from @APTAtweets on the App Store.
See you there!
@Jocelyn_SPT
#DPTstudent Chat Moderator
#DPTSTUDENT CHAT TOPIC FOR WEDNESDAY, SEPTEMBER 3, 2014: GLOBAL PT
The following post is written by Josh D’Angelo and Efosa Guobadia
With World Physical Therapy Day quickly approaching on September 8th, we have been discussing how we can play our part in strengthening the profession at the international level. We are currently in Guatemala (Efosa’s seventh trip here; Josh’s second) and will be teaching to, treating with, and presenting on advocacy to students and professionals in Guatemala City at the Universidad de Panamericana throughout the week.
We hope to broaden the discussion, generate ideas, and connect PT’s across the globe through this week’s #DPTstudent chat. We have also launched and will be discussing the hashtag #globalPTconnect, under which we will be live tweeting during much of our trip.
This is a profession that we all love and gives us so much, so trying to create ripples, bonds, and connections seems the next step. Simply joining the conversation will help to spread awareness of international efforts. You never know- you may be the next one traveling internationally and making global connections. Conversations like these is where it all begins.
We look forward to chatting.
Best,
Efosa and Josh
If you would like to read more about Efosa and Josh’s trip prior to the discussion, check out their most recent PT Haven article
The Great Doctor Debate: Wed, Aug 27
Hello and welcome to a new school year, boys and girls. It’s that time of year again when pools close their gates, pencils are sharpened, and new classes of future Doctors of Physical Therapy begin their studies.
The APTA’s most recent vision statement stands in stark contrast to the previous Vision 2020, which proclaimed with great fanfare that its practitioners would soon all be Doctors of Physical Therapy. This title has become the norm in our profession, with 96% of accredited physical therapy programs now offering the DPT and the remaining planning to convert.
Norms aside, the usage of this title remains highly controversial for current practitioners and even #DPTstudents. This week, we’ll debate the usage of the title “Doctor” by Doctors of Physical Therapy. We highly encourage both students and practitioners to join in the discussion on Twitter this Wednesday, August 27th from 8-9pm CST. Participants may find the links below helpful in preparation for the #DPTstudent chat.
Recommended reading:
NYT, “When the Nurse Wants to Be Called Doctor”
APTA Responds to The New York Times on Physical Therapists Using the Term ‘Doctor’
See you there!
@LauraLWebb
#DPTstudent chat moderator
#DPTstudent chat August 20, 2014: Why should I be an APTA member?
It’s about that time where DPT programs across the country are beginning. Many programs require APTA membership but, if yours doesn’t, is there any value of being an APTA member as a first year #DPTstudent? Won’t everything be way over your head? Will you even be able to go to a conference and take advantage of the savings with all the work coming your way? What else can APTA membership as a first year do for you?
Join us on Wednesday, August 20 at 9PM EST to discuss! If you are a second or third year or practicing physical therapist, please join us to share what value APTA membership has brought to you!
-Jocelyn, Laura, & Tyler
Lessons from a #DPTStudent Chat with Catherine Worthingham Fellows: Advocate!
Last week, the #DPTStudent chat had the privilege of talking to three Catherine Worthingham Fellows of the APTA, Dr. Nancy Kirsch (@KirschNancy), Rob Landel (@RLandelDPT) and Pam Duffy (@PamDuffyPT). As fellows, they have received the highest honor given by the APTA for exemplifying four core values throughout their career: advocacy, education, practice and research. It was an amazing honor to spend an hour with them discussing what they did to get where they are and how students can aspire to a similar level of excellence.
While the #DPTstudent chat approached this conversation with an open mind, a central theme quickly emerged: advocacy. Our profession is undergoing enormous change and it is on the shoulders of today’s students to lead it in the right direction. Dr. Duffy commented that “this generation of PT students brings such energy… students of today are there because they have a passion for what they want to do for patients and society and I really admire that.” This is the attitude we should advocate for and exemplify. We all decided to join this profession for a reason and it is up to us to work for it. So how can a student participate in advocacy?
Join the APTA (@APTAtweets). When asked how she benefited from the APTA as a new professional, Dr. Duffy noted how much information she gained from being a member. While you may not want to be on the front lines of advocacy, just staying informed is a step. Dr. Duffy also appreciated her early membership for the networking opportunities and stated that nearly every opportunity she had in those days was somehow related to her involvement.
Encourage others to join. This is more than just preaching. Dr. Nancy Kirsch made it a point to teach us that we should be finding out why people are not members. Instead of telling people why you are an APTA member, find out what’s important to them and help them figure out how membership can meet those needs. You can bring this attitude to all of your advocacy efforts.
Know your strengths, attack your weaknesses. You can’t do everything! As you move through your time as a #DPTstudent, be mindful of what you’re good at, what you’re interested in and what you’d like to improve at. Good at writing? Look for blogging opportunities. Terrible public speaker? Run for a class office and get better at it. By seeking out professional development opportunities via advocacy, you will graduate a well-rounded, and impressive, PT!
Seek out opportunities. This was a common theme amongst all of the fellows. At the end of the chat, Dr. Landel extended an invitation for any #DPTstudent watching to introduce themselves at upcoming conferences and the other fellows extended the same invitation. Accept the invite! You never know what may come out of interacting with leaders in your field. Bring this same philosophy with you to school and other local activities. There are opportunities to advocate everywhere, you just have to ask for them.
You can watch the chat in full here.
Again, we would like to extend our appreciate to Drs. Landel, Duffy and Kirsch for giving us their time and their lessons and we encourage every #DPTstudent to get out there and get involved!
@Jocelyn_SPT
#DPTstudent Chat Admin