Manipalooza from a #DPTstudent Perspective

photo 2-2 (2)There are some experiences as a #DPTstudent that leave you feeling energized, happy, and confident that you absolutely made the right career choice. This was one of those experiences. This past weekend I had the amazing opportunity to attend Manipalooza put on by Evidence in Motion. Manipalooza is a “3-day festival of hands on learning in manipulation, soft tissue techniques, pain management strategies, sports PT, and practice management. Participants will learn the most cutting edge techniques from experts in the PT field.” I can’t possibly fit everything I learned into a blog post but I am going to recap the many highlights of this experience.

photo-15 (2)

Saturday kicked off with a freestyle rap performed by a CU student on whatever PT topics the audience threw at him. You can see the video here. How someone raps about CT junction manips or G codes is beyond my comprehension but it was amazing and had everyone laughing to start off the morning. After an introduction to the weekend, Dr. Larry Benz kicked off the presentations with one titled “Deliberate Practice: Taking Your Skills from Good to Great”. This presentation focused on how to create a mindset of growth in order to continue to advance. One topic that Larry discussed that I find myself reflecting on again and again is the concept of “normalized discomfort”. This means that you have to fail in order to be able to grow. We must become more comfortable with failure and constructive criticism as we tend to learn the most from it. If we are not challenging ourselves outside of our comfort zone, we will never move closer to where we want to be. I would say that I found the whole weekend challenging and because of his talk, I was able to tell myself “it’s ok that you are struggling with this technique, this is challenging, and you are learning.”

Daphne Scott, leadership extraordinaire, then took to the floor with a presentation called “Change, Willingness…and Love”. Daphne lead the group through an exercise where we took a complaint we had about work or life, and showed us how to analyze and redirect the complaint and turn it into something more productive but to also stop wasting creative energy on blaming ourselves and instead just recommit to your goal. We discussed how change is hard and how upwards of 70% of companies who try to implement change fails.

After the short morning presentations, you had the choice of 3 different sessions: manual therapy of the foot and ankle (ortho track), neuromuscular intervention for chronic ankle instability (sports track), or time management and the illusion of time (business track). TJ and I decided to go to the ortho track, but I wish we could have been at all 3! Some of the techniques we went over I had previously learned in school but it was really nice to see a few modifications as well as get a nice refresher! I was also exposed to several techniques that we did not learn previously.

TJ practicing a rear foot distraction technique

After lunch I decided to switch tracks (the afternoon classes that were offered were manual therapy of the knee, Eval of athletic movement: the ACL, and Career development: Yours and Theirs) and attend the business track on career development lead by Daphne Scott. It was a small group and Daphne asked all of us to tell her what we wanted to get out of the session. TJ and I were the only DPT students in the room (in fact, there were hardly any students at the event at all! Maybe 8 total for the Saturday session and just the two of us on Sunday!) and it was interesting to hear clinic owners talk about developing their staff. We also talked a lot about passion and spotting the employees who find their position to be a job, a career or a calling. A job is something you do to make money. Scooping ice cream when I was 15 was a job. A career is something you are trained in and have room for advancement but would quit if you won the lottery. My previous profession of an accountant was a career. A calling is what you think you were meant to do and you would still pursue it if you won a few million bucks. For me, this is my future in physical therapy- I am passionate about it so much that even if I were to become rich by investing in the Best Investment Apps UK, rich I would still be a physical therapist (granted, one that takes super fancy vacations).  I was able to leave that session knowing what I am looking for as far as career development goes and how to be sure that my values align with a potential employer.

regis
A few of my classmates that attended!

The Sunday sessions were equally as fun! We kicked off the morning with 4 hours of thoracic and rib cage manual therapy and manipulations taught by Tim Flynn. The afternoon was 4 hours of cervical manips taught by Jason Rodeghero, EIM’s orthopedic residency director. Both sessions integrated clinical reasoning alongside of the manual techniques. What I absolutely loved about all of the lab sessions is how many EIM faculty were there to help! I had personalized attention from at least one -but most times 2 different faculty helped- on every single technique. I was offered advice on how to modify skills based on my size, how to adjust my hand placement, and several times a faculty would place their hands over mine to make sure I was where I was supposed to be. Jason even taught us a little trick to help with speed of manipulations by using a water bottle to practice the small quick movements! I have been doing this with my water bottle every day…but make sure the lid is on tight enough or else you have water all of the floor…not like I did that or anything.

Learned several modifications for this technique in order to perform it on patients bigger than I am (which is everyone)

I was introduced to some of the techniques in school but I left on Sunday with many more skills in my proverbial PT toolbox and a greater sense of confidence about using my hands on a patient. In fact, I thought to myself many times, “I had no idea this many manual techniques even existed!” As I said before the weekend was challenging. TJ and I would talk through each technique in regards to when you would use it on a patient before practicing on each other. With many of the techniques we struggled at first, but with deliberate practice (Thanks, Dr. Benz!) and amazing faculty there to help us we were successful with all of the techniques before we left. We ended Sunday by attending the complimentary managers reception at the host hotel where we were able to chat with the EIM faculty and other participants.

TJ and I with Dr. John Childs and Dr. Tim Flynn

Unfortunately, I had to high tail it back to Wyoming for clinical on Monday, so I missed the last day. However, one of the best parts about Manipalooza is that EIM gives you online access to their Moodle which is an online classroom and I was able to download all of the slides from the sessions I missed!

I would argue that Manipalooza is one of the absolute best conferences a DPT student could attend. The clinical reasoning, hands on labs, and amount of fun is unparalleled. If you want to take your manual skills to the next level before graduation this is the place to go The personalized attention allowed me to leave with a sense of confidence in the skills that I learned. Manipalooza will be an event that I attend year after year. It is just too good to miss!

Thank you again to EIM for such an amazing event!
#DPTSTUDENT CHAT TOPIC FOR WEDNESDAY, MAY 21, 2014: TIME MANAGEMENT AND STUDY TIPS

Congratulations!

You’ve been accepted to physical therapy school and are ready to embark on a great adventure. Or perhaps you have finished your first (or second) year and are looking to fine-tune your approach for the remainder of your time as a #DPTstudent. Whatever the case may be, this Wednesday we are looking for incoming, current and former students to share their study tips and time management strategies that have helped them achieve success.

See you there!

–@LauraLWebb

Data Quality: Garbage In = Garbage Out

Measuring and objectifying observations and phenomena. Numbers. Data. These are the cornerstones of analytics. The presentation and appearance of (apparent) objectivity. Whether in research, health care policy, economics, business, or clinical practice, data is important.

The data doesn’t lie.

But, sometimes the people that interpret it do. Not that they mean to. It’s not done on purpose (except when it is). So, yeah, unfortunately, the numbers can lie. And, they will lie to you if you are not conscientious about assessing them more deeply.

“What gets measured, gets managed.” Peter Drucker

Data Quality

Questions of why this works, or, maybe, more importantly, “does this work as proposed? Does the explanatory model make sense?” are not inherently built into the evidence based approach. Yet, these questions are vital to integrating and understanding outcomes research, while evolving our theoretical models. Such a task mandates metacognition and critical thinking. Failure to critical assess the quality, and potential meaning, of data, will result in improper conclusions.

The evidence hierarchy is sorted by rigor not necessarily relevance –EBP and Deep Models

But, the questions and issues surrounding data quality and interpretation transcend assessing the literature within the context of the evidence based hierarchy. Much like the research literature, the data collected, analyzed, and utilized everyday warrants critical appraisal. It all requires assessment; data encountered inside and outside the clinic, data utilized for decision making and understanding. The concepts of scientific inquiry should be wielded routinely, including assessment of quality, source, and limitations of the numbers. Only then, can proper interpretation and subsequent decision making occur.

Is it accurate?
Is it representative?
Where did the numbers originate?
What do the numbers actually represent?
What conclusions can or can not be concluded from a data set?

The evidence based practice hierarchy is concerned mainly with questions of “what works?” and “what is effective and efficacious?” These are necessary, important, big questions. But, the term “evidence” as utilized by most clinicians and researchers is focused mainly on randomized clinical trials, systematic reviews, and meta analyses of randomized control trials. Outcomes based research. This is a necessary and obvious step forward from purely observational, experienced driven clinical practice and education. Despite the obvious importance of experience (or more accurately deliberate practice) in clinical decision making, analysis based on experience or clinical observation only is prone to errors such as confirmation bias and convenience. Clinical observation alone is limited in it’s ability to ascertain phenomena such as a natural history and regression to the mean. And thus, this issue is related not only to data quality, but proper data interpretation. Understanding data quality assists in assessing “what works”, but also in tackling the complex question of “why does it appear to work?” Both questions are inherent to, and reliant upon, the quality of data.

Numbers, Data, and Objectivity

In attempting to objectively measure the world, has the potential accuracy and quality of data been forgotten? Overlooked even? A number seductively presents the appearance of objectivity and accuracy, but does not guarantee it. Big Data provides an excellent example of data quantity with relatively overlooked quality. Astounding data-sets through avenues such as social media and search engines afford researchers and large companies the opportunity to analyze data-sets that would literally explode your lab top. For example, in 2008-2009, based on web search data Google Flu Trends more accurately and quickly predicted and modeled flu outbreaks than the Centers for Disease Control (CDC). Well, until 2012-2013 when it wasn’t so accurate, over estimating peak trends. In big data are we making a mistake? Tim Harford explores the scientific and statistical problems still present (even when the size of a data set requires it to be stored in a warehouse): 

But a theory-free analysis of mere correlations is inevitably fragile. If you have no idea what is behind a correlation, you have no idea what might cause that correlation to break down. One explanation of the Flu Trends failure is that the news was full of scary stories about flu in December 2012 and that these stories provoked internet searches by people who were healthy. Another possible explanation is that Google’s own search algorithm moved the goalposts when it began automatically suggesting diagnoses when people entered medical symptoms…

Statisticians have spent the past 200 years figuring out what traps lie in wait when we try to understand the world through data. The data are bigger, faster and cheaper these days – but we must not pretend that the traps have all been made safe. They have not…

But big data do not solve the problem that has obsessed statisticians and scientists for centuries: the problem of insight, of inferring what is going on, and figuring out how we might intervene to change a system for the better.

Measurement Matters

Now, just because it can be measured, does not mean it should be measured. Measurement alters behavior. And, the change is not always as envisioned or desired. As soon as a goal is set to alter a metric, incentives apply. This concept transcends clinical care. It applies to business, management, and clinician behavior. Enter the cobra effect.

The cobra effect occurs when an attempted solution to a problem actually makes the problem worse. This is an instance of unintended consequence(s).

So, is the goal to change that specific metric only?  Or, is the actual goal to encourage specific behaviors that appear to directly affect, or are correlated with, that metric. Regardless of the goal, care must be taken in defining success. This requires a clear definition of what is measured and why. Again, deep analysis of data quality and interpretation are necessary to properly interpret results of process changes. Due to the appearance of objectivity in the presentation of numbers, it is easy to make inaccurate or far reaching conclusions. This is especially true when care is not taken to assess all the components of the data:

What does the data actually represent?
Who or what measured it? Who or what entered it?
How was it initially assessed and subsequently interpreted?
What other data needs to be considered or measured?

Now, even with reliable and accurate data input, inaccuracy can occur. The wrong conclusions can be “output” because of the misinterpretation regarding what the data is representing or signifying. Wrong numbers = wrong analysis = wrong conclusion = wrong interpretation = misguided application.

Steer away from subjectivity

The complexity of even the simplest data sets is astounding. Ever present are questions such as: Is the data valid? Does the data represent the assumed construct or principle? What potential bias is involved? Is it reliable between people; between subsequent measurements? Is it actually measuring what we think it’s measuring? Can it answer the questions we are posing? Measured and presented data is rarely as simple as a concrete number.

The attempted objectification and simplification of subjective, individualized, complex phenomena such as happiness, satisfaction, engagement, or pain may be tragically flawed. Commonly, over reaching conclusions are based on assumptions of accurate and/or complete representation. The data presented is merely a measurement, a number produced via the tool chosen.

A tool misused produces data that’s unusable

That tool may, or may not, accurately convey the construct it was initially designed to represent. In the case of patient report questionnaires, the individual filling out the tool will always be biased; influenced by the environment, their expectations of what should be conveyed, influences from others (explicit and implicit), as well as complex incentives depending on their needs, goals, and expectations. Further, most data encountered on daily basis, including clinical outcome measures (whether patient performance or patient report), is not collected in controlled environments with explicit processes. Bias will always affect reporting and recording. Questions of the accuracy, reliability, and validity apply not only to the tool, but also to the person recording the measurement. It quickly becomes complicated. The Modified Oswestry Disability Index never seems so messy when presented as a straight forward percentage.

Compare the stark contrast between how an outcome measure is collected within a research trial vs. everyday clinical practice. In order to minimize both error and affects of bias, outcomes in a trial are collected by a blinded assessor. A standardized set of directions is utilized, with a pre-defined process for administration and measurement. But, even in more controlled, direct data collection environments, what is being measured and what that actually illustrates, is not straight forward. Representation is not always linear. Even in randomized, tightly controlled, double blind studies bias and flaws are present. This does not inherently make the data useless. Leaps of logic need to be recognized.

If data is sloppy enough it is beyond useless. It’s harmful.

Why? Because, unreliable, variable data that is not truly measuring or representing the phenomena one assumes will ultimately lead to inaccurate conclusions. Regardless if the data is positive, negative, or neutral it is misleading.

How? Because, the data itself can not be representative of what we think it is measuring, purely by the the fact that the data itself is unreliable, overly variable, and “sloppy.” Further, if the assumption is made that a measure represents a certain construct, but it actually does not, it has no validity. Without reliability, validity is unobtainable. Without validity, reliability is misleading.

Data Quantity vs. Data Quality

So, should the focus remain on quality or quantity in data? Both. Is more data always better? Well, that depends on the quality. But, what is quality data? Quality is a relative term. Collecting, analyzing, or using data is only part of the equation. Once collected, questioning validity, reliability, representativity, and relevance is necessary. In the cases when data has already been collected and potentially presented, it’s time for some serious skeptical inquiry. Understanding what data actually represents and illustrates assists in proper critical appraisal. Proper critical appraisal allows proper interpretation. Proper interpretation is the foundation for  effective utilization. Less controlled data collection environments do not necessarily produce unusable data, and in fact can be quite useful in the realm of health services and care delivery models. Yet, the conclusions drawn on effects, mechanisms, and efficacy need to be tempered. Focus on understanding exactly what a data set can and can not illustrate given the data collection environment and design and metrics.

Unreliable and invalid data in, wrong conclusions out. Always. Any accurate representation will be by chance alone. But, in these instances, the probability of attaining an accurate representation will often be less than chance. Limits are always present, and can not be avoided, but understanding the limits of the data assists in drawing conclusions that are the least wrong. While the data itself is important, what is done with the data, and why, is almost more important. And, these principles apply whether you are assessing your clinics “outcomes” or tracking disease outbreaks with big data. Focus on improving the quality and accuracy of data collection on the front end. Train those measuring, collecting, and entering data. Improve analysis and inquiry on the back end. In addition to asking “where’s the data?” we should be asking “where did that data come from?” and, “what does it actually illustrate?”

Be skeptical. Garbage in = garbage out.

#DPTSTUDENT CHAT TOPIC FOR WEDNESDAY, MAY 14, 2014: PAYING FOR A DPT DEGREE

As the next class of DPT students enter schools around the country, they are likely facing the highest tuition costs yet, while possible changes to forgiveness programs are on the horizon. Is the DPT degree still worth it? We certainly think so, but financial responsibility is still a huge concern. What can students do to minimize the cost of their DPT degree well before they graduate? What loan repayment options are out there? Will PSLF still be an option? Are there still clinics offering loan repayment assistance or is competition for jobs making these benefits more scarce? We will pose these questions (and more!) on Wednesday, May 14th at 9 PM EST. Join in the discussion!

Precision in Language

Language is obviously important as words are the basis of explicit communication. As is such, specificity in language and word definitions is vital to interaction. But also, specificity in meaning is required for accurate scientific research. Thus, terms are often operationally defined in studies. It is an attempt to clearly communicate how the researchers are defining, utilizing, and investigating a construct. Hopefully, ensuring appropriate interpretation and application of results while bundling theoretical constructs through explicit definitions.

I’m no expert in linguistics, philosophy, or even language, but I think this is an important professional topic. Now, admittedly, physical therapists deal with complex physiologic systems and phenomena. Some concepts can elude specific definitions physiologically and linguistically. Pain is a perfect example.

The lived pain experience is an emergent, individually experienced phenomena dependent on a myriad of interacting physiologic, psychologic, environmental, social, cultural, and linguistic components. It’s not merely resultant from nociception nor tissue damage or even injury. Yet, the presence of such complex systems and phenomena should not preclude striving for specificity of language. Vagueness does not help us. Investigating form, meaning, and context of language assists in research, education, and patient interaction. Luckily, the International Association for the Study of Pain created a taxonomy, and is attempting to more robustly define terms related to the painful experience. The list includes hyperalgesia, hyperesthesia, noxious stimulus, peripheral sensitization, central sensitization, and neuropathic pain among others. Some terms, such as allodynia (“pain due to a stimulus that normally does not provoke pain”), are considered “clinical terms” and purposefully absent of proposed mechanisms. Other terms, such as nociceptive stimulus (“an actually or potentially tissue-damaging event transduced and encoded by nociceptors”), are mechanistically more specific.

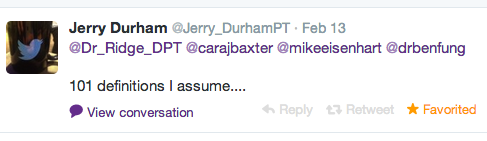
As a more concrete, basic science example, what would result if 100 physical therapists & 100 physicists  were charged to define strength, power, acceleration, stability and balance? How many definitions? How much similarity would they display?

@Jerry_DurhamPT has a hypothesis…

101definitions

101 definitions.

One, exact definition (and likely a formula) from the 100 physicists. And, likely 100 separate, but similar, definitions from 100 physical therapists. These words have explicit definitions and equations within the realm of physics (classical mechanics). As Erik Meira asserts robust, specific definitions are absolutely necessary for science:

I’m not trying to get metaphysical here but we must define our terms in order to be scientific…Poorly defined statements are inherently not scientific. Just because it’s published does not make it science.

Specificity and discipline in language is a necessary first step. It is required for accurate discussion and collaboration within research, clinical practice, and between professionals. This includes other professions (and not just healthcare). But, unfortunately, appropriately defining and subsequently understanding definitions does not account for, nor address, how other healthcare professionals, disciplines, patients, and society perceive certain words. What are their definitions? As an example, lets explore the word “prevention.”

Prevention: the action of stopping something from happening

Within healthcare and physical therapy, true prevention by definition, is kind of a misnomer. But, the health care system, patients, and consumers utilize the term prevention differently. Usually, the concept of “prevention” is actually used to mean “risk reduction.” Thus, the “functional definition” within the context of healthcare and patient interaction is slightly altered. What is actually meant by ACL injury prevention is reducing the likelihood of an ACL tear. Epidemiology provides some insight…

In epidemiology, the absolute risk reduction, risk difference or excess risk is the change in risk of a given activity or treatment in relation to a control activity or treatment. It is the inverse of the number needed to treat. -Wikipedia

In epidemiology, the relative risk reduction is a measure calculated by dividing the absolute risk reduction by the control event rate.

The relative risk reduction can be more useful than the absolute risk reduction in determining an appropriate treatment plan, because it accounts not only for the effectiveness of a proposed treatment, but also for the relative likelihood of an incident (positive or negative) occurring in the absence of treatment. -Wikipedia

Currently, there are no singular interventions to fully prevent the occurrence of most diseases and injuries in normal life situations. In being alive, there is always risk.

So what to do? If other disciplines such as mathematics, physics, or psychology have defined a certain term or construct, I propose it necessary to understand and utilize that definition accurately in professional discourse. The terms above, which originate from classical mechanics, immediately come to mind. We should challenge and operationally alter definitions from other fields only if strong data and logic warrant modification. Further, in research, discussion, and education the most specific, accurate definitions should be sought after. If unknown, questions should arise, discussion should ensue, and operational definitions provided. Science requires precision in language: exact terms. Lastly, the patient and consumer’s definition of certain words needs to be ascertained. Where feasible, more appropriate explanations should be provided to improve public and professional understanding of terminology. Communication is strained, and collaboration limited, if we are essentially “speaking different languages.”

A physical therapist does not need to be an engineer, but understanding the language of mechanics allows for true discussion between fields. It opens the door for increased collaboration.

A physical therapist does not need to be a psychologist, but knowledge of psychological constructs allows for evolved ways of conceptualizing and treating patients. It lends itself to improved research and clinical practice.

A physical therapist does not need to be a linguist, but explicitly defining words is necessary. It helps us understand form, meaning, and context.

collaborate

We need specificity and discipline in our language. Combining our expertise with the language and concepts from other disciplines fosters the ability to more robustly communicate and subsequently collaborate. This allows us to identify the grey, and step into uncertainty. For then we can truly start to explore the chaos, slowly illuminating specificity. Vagueness, after all, is beyond the limits of logic and reason.

#DPTSTUDENT CHAT TOPIC FOR WEDNESDAY, MAY 7, 2014: WHAT I WISH I WOULD HAVE KNOWN WHEN I STARTED PT SCHOOL

It’s that time of year when students are graduating, new third years are entering full time clinicals and all of us are reflecting on how quickly school has passed. Every incoming #DPTstudent is eager to learn from others’ hindsight. What do you wish you would have known when you started PT school? What could you have done to learn more efficiently, to save more money and to make better use of your three years? And what did you do right? Do you have any other advice to share with every first year and incoming #DPTstudent? Join in on Wednesday at 9 PM EST to share!

#DPTstudent You don’t need clinical experience…

You need deliberate practice. And, don’t be fooled you still need a lot of it.

The three most dangerous words in medicine are “In my experience.” –Mark Crislip, MD via Science Based Medicine

Especially when you are unaware of it’s caveats and limitations. Per Malcom Gladwell’s Outliers many advocate the 10,000 hour rule regarding the development of expertise. While this is a useful illustration of the sheer volume of practice necessary to develop mastery, it’s likely over simplistic for a concept as complex as expertise in a complicated craft.

Marla Popova comments that

The secret to continued improvement, it turns out, isn’t the amount of time invested but the quality of that time. It sounds simple and obvious enough, and yet so much of both our formal education and the informal ways in which we go about pursuing success in skill-based fields is built around the premise of sheer time investment. Instead, the factor Ericsson and other psychologists have identified as the main predictor of success is deliberate practice — persistent training to which you give your full concentration rather than just your time, often guided by a skilled expert, coach, or mentor. It’s a qualitative difference in how you pay attention, not a quantitative measure of clocking in the hours.

Clinical care, research, and critical thinking are no different. It is not experience, as linear measurement of time, but rather quality practice and volume that matters in developing high level skills. Left to its natural devices our brains and psyches are stubbornly prone to bias and errors in rational thinking. Confirmation bias and improper associations such as post hoc ergo propter hoc (since event Y followed event X, event Y must have been caused by event X) are common and often unrecognized. Thus, practice must be reflective and critical. Practice must be varied and evolve over time.

The skills required (mental, psychomotor, interpersonal, and otherwise) are staggering. It involves knowledge of current research, research methods, critical thinking, connection of concepts, connection  of knowledge, problem solving, listening, examination, hands on techniques, clinical decision making, and patient interaction.

Evidence is more important than experience.
Evidence can not replace experience.
You can’t have evidence based practice without experience.
Experience is meaningless without evidence.

Experience vs. Evidence. I observe these views that appear to be from separate ends of a spectrum, that appear to be contradictory, but in reality are just different concepts. So, does experience matter? Yes, but…experience as conceptualized and measured in years is both insufficient and incomplete. The focus should not be the mere acquisition of experience; but instead on proper, focused practice with the appropriate processes required to develop the necessary skills for mastery. This is not to say volume is meaningless, even focused practice requires repetition and time for effectiveness. Quantity is ultimately meaningless without quality. Quality is meaningless if it can’t be repeated and refined .

Adam Rufa and Joe Brence of Forward Thinking PT examine the concept of “clinical experience.” Their post series, The Experience Wall, assesses perceptions, memories, and interpretation within clinical care. Joe Brence highlights how experience may not result in linear increases in clinical skill and outlines a new definition of clinical experience:

I propose clinical expertise is not simply gained through practice. It is built through assessment of your ability to think, reason and apply scientifically plausible principles into practice. It requires peer-review.  It requires your thoughts and ideas to be challenged. It requires a hint of uncertainty.


New grads should be armed with the latest research, and often tout that they are more “evidence based.” Without “experience” they should rely mostly on didactic knowledge, research, and strong science based logic as they lack sufficient “experience” meaningful practice volume. But, clinicians with years and years of experience may claim that this research evidence alone is empty without time in clinic. So, who is right? Well, both of course.

Knowledge of research does not mean you can apply it. True
Having experience does not mean you are providing “evidenced based” interventions. True
Proper knowledge and experience do not ensure best care. True.

Paradoxes exist, and hacking may be helpful to a broader, more accurate assessment of the hows and whys of clinical care. Appropriate “evidence base” and proper “experience” are separate, but interacting components of developing into a high level clinician. Ideally, these are synergistic principles that contribute to each other, instead of mutually exclusive entities that are developed in isolation. Neither “experience” nor “evidence” ensures accurate research interpretation and application. Knowledge of current literature, appraisal of research, application of science, translating understanding into to practice, volume of clinical practice, and level of clinical ability (ranging from communication to therapeutic alliance to clinical decision making) are all differing skills. Of course, this is not an exhaustive list or conceptual framework. But, in essence, developing as a clinician, no matter our professional age, is more than simply evidence or experience.

Residencies and fellowships contain the potential to accelerate development when implemented effectively. The explicit curriculum, reflective practice, and mentorship can result in a more deliberate, critical, and self-reflective form of professional growth and clinical care. But, of course, residencies and fellowships do not guarantee proper mental skill acquisition or development, especially if founded on misguided assumptions or practice theories (but, this is a wholly separate topic); nor are they the only means to foster such growth. I have encountered plenty of physical therapists with bachelors degrees whose critical thinking, clinical decision making, and “evidence” base is quite staggering. And, conversely, I’ve interacted with many residency and fellowship trained physical therapists with doctor of physical therapy degrees whose reasoning and treatment skills were quite suspect. And yet, as Eric Robertson and Lauren Kealy discuss in their post series, The Bane of the New Professional remains significant. New grads are empowered and motivated to engage within the profession, yet some clinics appear to value experience. So, what gives?

Experience is bias.
Evidence is rigid.
Experience lacks rigor and control.
Evidence lacks experience applying to the individual.

There are great janitors and bad rocket scientists. Hacking your education, regardless of your experience, is necessary. These concepts of experience and evidence require critical reappraisal; a reframing that recognizes the necessity of a synergistic relationship. In regards to the myriad of skills encompassed in clinical care, an understanding to the non-linear progression of each. It’s much more than evidence vs experience, evidence or experience, or even evidence and experience. And, it takes practice.

Passing of the #DPTstudent Chat Torch

The #DPTstudent chat was created in November of 2012 and has been going strong every Wednesday at 9pm EST since then. The chat has been recognized by the APTA, clinic owners and students alike as a great tool for networking and learning outside of the classroom. Eric Robertson, one of my mentors and a huge enthusiast of the chat, told me once that he thought the chat was one of the most innovative things to happen to DPT students. I never expected it to be as successful as it has been, but I am humbled and excited about how big of an impact it has made. Personally, I can say that I have learned just as much through this chat and interacting with those on social media as I have inside the walls of the classroom.

Don’t worry- the life of the #DPTstudent chat is far from over! In fact, it will be revitalized and have a new energy to it as several new chat leaders take the reigns. As TJ and I move into our final year of PT school, our energy will be focused on our final clinical rotations and transitioning into the professional world. Before we introduce the new chat leaders, let us take a moment to reflect on how far the chat has come and how many students and professionals it has impacted.

According to Symplur.com, #DPTstudent has had…

30,765,113 impressions

31,213 tweets

2,343 participants <- holy cow!

and an average of 2 tweets per hour, every day, for the past 17 months.

TJ and I will still be active on the chat, but please welcome your new chat leaders!

Tyler Tracy @TylerTracy10

My name is Tyler Tracy and I’ll be starting the DPT program at Texas State University in May 2014.  At 31, I am older than the traditional DPTstudent as I am completely changing careers.  After completing my undergraduate degree in Criminal Justice, I spent about 5 years working as an investigator where I conducted investigations on behalf of the US government.  My wife and I are expecting our first child in September 2014, I have the coolest dog alive, and I’m an absolute sports junkie! I have been exposed to the world of physical therapy through my wife and best friend who are both physical therapists in different settings (pedi and neuro respectively).  I have also had the opportunity to see PT from a patient perspective a few times due to breaking 13 bones!  I have already gained a wealth of knowledge through the #DPTstudent chats and I look forward to continued growth with Jocelyn, Laura and the other students / professionals who participate with us!

Jocelyn Wallace @Jocelyn_SPT

My name is Jocelyn Wallace and I’m starting the DPT program at Nova Southeastern University, Ft. Lauderdale, in May 2014. I graduated from the University of South Florida with a B.S. in Environmental Science and plans to be a lawyer. After two years working as a paralegal, I knew that path wasn’t for me but I did get experience working for PACs and the FL State Senate. I am excited to apply these experiences to advocate for the profession I believe in. I’ve spent the past year working at a #cashPT practice and have completely absorbed myself in the profession. I even started up the company’s social media plan and got on twitter myself to “practice what I preach”. That decision has already paid off tenfold as I have been given the opportunity to help lead the #DPTstudent chat, learn and connect with countless fellow students and professionals. I am beyond eager to see what the next 3 years on Twitter bring!

Laura Webb @lauralwebb

Hi! My name is Laura Webb and I am a 2nd-year physical therapy student at the University of Kansas Medical Center. I am president of my class, and am involved in the Kansas Physical Therapy Association Student Special Interest Group. In my spare time I like sailing, playing, and learning music, training for triathlons and teaching water aerobics. I consider myself a coffee connoisseur, and I love chickens. I’m looking forward to helping out with the #DPTstudent chats!

The transition to these amazing new moderators will be taking place soon, so be sure to follow them and welcome them!

Pheminism and Physical Therapy

Several weeks ago, women equality in the field of physical therapy became quite the hot topic on Twitter. We even hosted a #DPTstudent chat on the topic. The essence of several of the online conversations was that in a profession made up mostly women and started by women, there is a higher percentage of men who “make it to the top” / “own clinics” / “are CEOs and entrepreneurs”. Many of the conversations focused on the potential reasons on why this was happening in our profession. The next few paragraphs are my response, as woman in this profession, to those conversations.

First thing is first. The issue of women equality in the workforce is not unique to physical therapy. In fact, it is most all industries. In some fields it is worse than others. My husband works in IT Network Security and he has no female coworkers. Physical therapy comes in high on Forbe’s list of “Best Paying Jobs for Women in 2014” stating that women earn 89% what their male counterpart earns. Not perfect, but certainly not nearly as bad as real estate agents where women are said to earn only 60% of what a man would earn. Woman earning equal pay to male counterparts has been a long debated topic and there continues to be a push for women equality in many fields. Physical therapy still has some work to do to reach full equality, but I am happy to know we are at a better starting point than most other professions.

It is important to recognize that men and women are different. We should be seen as equals, for sure, but women and men tend to be very different creatures. We are wired differently and I’m not just talking about our anatomical parts. Well, I guess in some ways I am. If a couple wants to start a biological family, the woman is the one with the parts to bear the child. Many women volunteer to leave the workforce to raise a family and if she chooses to enter the workforce at a later time, she will earn less money due to her time away. Women have more decisions to make regarding their family and career balance than a man does. This can be mitigated by being with a partner who equally shares responsibility for house hold chores and child care.

I am passionate about women equality. I want to know that I would be offered the same exact salary as my male equivalent. I also recognize that men and women potentially have different needs, requirements and dreams. Maybe her dream is to raise a family. Maybe she wants to own a company. Maybe she wants all of that. That is okay and we as a profession and society have to recognize and be supportive of that. I’m not sure there is a hard and fast solution to women equality in any field but having conversations and raising awareness can only help the issue. So far, the only issue I have encountered from being a woman in this profession is the lack of stylish shoes that still have enough arch support to allow me to stand on my feet all day without pain. I know that the hardest part is yet to come but with recognition of this issue, mentors of both the female and male variety, and a husband who is willing to vacuum, I am set for success to overcome obstacles.

As mentioned before, I’m not sure there is a quick fix or even a planned solution for woman equality in the workforce but the first step is recognizing the issue and starting a conversation about it. Some women involved in the discussion have proposed that we continue this conversation. One such examlpe of this is the PropelHer initiative. Heidi Jannenga, who generated the idea thinks that PropelHer can provide a platform for on campus conversation between faculty and students as a way to explore this issue further.  Keep your eyes out for the launch of PropelHer soon!

But in the meantime…perhaps we need to take the dancing approach to talk about women equality. (Super funny Jimmy Fallon clip!)


http://www.hulu

#DPTSTUDENT CHAT TOPIC FOR WEDNESDAY, APRRIL 9, 2014: HOW THE INTERNET HAS AFFECTED HEALTHCARE

I’m sure we have all had an ache, pain or other ailment and immediately went to Web MD to diagnose ourselves. With how accessible information is on the internet, the majority of our patients will at least try and research potential diagnoses for their issues. How does this effect us as clinicians? How do we get patients to trust us if we don’t necessarily agree with what they read on the internet? We often talk about the positive affects of social media on healthcare, but what about the negative affects? Do you think the internet has made our roles as educators more difficult? Let’s talk about it Wednesday at 9pm EST!