What Scientific Ideas are Ready for Retirement?

Every year Edge poses a question and subsequently curates responses from a variety of intellectuals. The result is a fascinating compilation of short essays on a range of ideas orbiting around a central theme. Previous questions include “what scientific concept would improve everybody’s toolkit?” and “what is your favorite deep, elegant, or beautiful explanation?”

And in 2014, “what scientific idea is ready for retirement?”

Science advances by discovering new things and developing new ideas. Few truly new ideas are developed without abandoning old ones first. As theoretical physicist Max Planck (1858-1947) noted, “A new scientific truth does not triumph by convincing its opponents and making them see the light, but rather because its opponents eventually die, and a new generation grows up that is familiar with it.” In other words, science advances by a series of funerals. Why wait that long?

WHAT SCIENTIFIC IDEA IS READY FOR RETIREMENT?

Ideas change, and the times we live in change. Perhaps the biggest change today is the rate of change. What established scientific idea is ready to be moved aside so that science can advance?

Knowing is Half the Battle

by Laurie R. Santos and Tamar Gendler

The lesson of much contemporary research in judgment and decision-making is that knowledge— at least in the form of our consciously accessible representation of a situation—is rarely the central factor controlling our behavior. The real power of online behavioral control comes not from knowledge, but from things like situation selection, habit formation, and emotion regulation. This is a lesson that therapy has taken to heart, but one that “pure science” continues to neglect.

So, in knowing that knowing is not nearly sufficient, what are we to do? Metacognition, reflective experience, and recognition of incentives are components of improving our decision making performance. Studying cognitive bias, behavior change, and philosophical argument also aid critically thinking. Beyond our own personal, and professional, growth these concepts are salient within clinical practice, patient care, research, and education.

Heights And Lengths And Areas Of Rectangles

by Robert Sapolsky

The problem with “a” gene-environment interaction is that there is no gene that does something. It only has a particular effect in a particular environment, and to say that a gene has a consistent effect in every environment is really only to say that it has a consistent effect in all the environments in which it has been studied to date. This has become ever more clear in studies of the genetics of behavior, as there has been increasing appreciation of environmental regulation of epigenetics, transcription factors, splicing factors, and so on. And this is most dramatically pertinent to humans, given the extraordinary range of environments—both natural and culturally constructed—in which we live.

Sapolsky’s essay illustrates complexity and interaction. While simplicity is important, caution is warranted to avoid over generalization. And, of course, do not discount the effect of dependency. Everything depends; on incentives, environment, previous experience, the current situation, and more. Some factors, and influences, likely have not even been identified. This is especially true in the realm of humans and behavior. An interesting book The Dependent Gene: The Fallacy of Nature vs. Nurture is an in depth exploration and refutation of inaccurate understandings of genetics.

Big Data

by Gary Marcus

But science still revolves, most fundamentally, around a search of the laws that describe our universe. And the one thing that Big Data isn’t particularly good at is, well, identifying laws. Big Data is brilliant at detecting correlation; the more robust your data set, the better chance you have of identifying correlations, even complex ones involving multiple variables. But correlation never was causation, and never will be. All the big data in the world by itself won’t tell you whether smoking causes lung cancer. To really understand the relation between smoking and cancer, you need to run experiments, and develop mechanistic understandings of things like carcinogens, oncogenes, and DNA replication. Merely tabulating a massive database of every smoker and nonsmoker in every city in the world, with every detail about when they smoked, where they smoked, how long they lived, and how they died would not, no matter how many terabytes it occupied, be enough to induce all the complex underlying biological machinery.

Physical therapy likely under utilizes big data and available data sets. None the less, big data inherently contains all the methodological issues of any study or data set: sampling bias, reliability, validity, blinding, confounding factors, operational definitions, and control. Remember, garbage in = garbage out. Big data must be put into context, and properly analyzed. What question is being posed? What questions can the data actually answer? And, what are the limitations? Quantity in data is never a direct substitute for quality. As Marcus asserts, “we should stop pretending big data is magic.” Data, after all, is just data, and is nothing without analysis. Analysis, if conducted improperly or with bad assumptions, breads false interpretation.

Mental Illness is Nothing But Brain Illness

by Joel Gold and Ian Gold

That a theory of mental illness should make reference to the world outside the brain is no more surprising than that the theory of cancer has to make reference to cigarette smoke. And yet what is commonplace in cancer research is radical in psychiatry. The time has come to expand the biological model of psychiatric disorder to include the context in which the brain functions. In understanding, preventing and treating mental illness, we will rightly continue to look into the neurons and DNA of the afflicted and unafflicted. To ignore the world around them would be not only bad medicine but bad science.

The direct parallels to physical therapy are striking. Psychological, contextual, and social factors are now recognized as foundational contributions to symptoms, function, intervention mechanisms, and treatment response. How will education, clinical practice, and research evolve to accommodate such insights?

Only “Scientists” Can Do Science

by Kate Mills

However, limiting the potential contributions of informally trained individuals to the roles of data-collector or data-processor discounts the abilities of citizen scientists to inform study design, as well as data analysis and interpretation. Soliciting the opinions of individuals who are participants in scientific studies (e.g., children, patients) can help traditional scientists design ecologically valid and engaging studies. Equally, these populations might have their own scientific questions, or provide new and diverse perspectives to the interpretation of results.

There is a growing need for individuals to occupy the historically ill defined black box between research science/academia and clinical practice. Further, healthcare yearns for clinicians approaching patient care, clinical data collection, and clinical care from a scientific lens. Scientific and clinical research is challenging, time consuming, and expensive. Well trained, highly skilled researchers and scientists a requirement, I won’t argue otherwise. But, interpreting and translating such knowledge into clinical practice is an often under appreciated skill set. And, formal academic or clinical roles devoted to this necessary bridge are sparse. Conversely, formal means of translating clinical practice, clinical data, or even clinical observations into research (or to academia in general) are lacking. Well designed quality improvement projects are a means of fusing clinicians and scientists, clinical care and research. Yet, many clinicians lack the time and expertise to design projects, ensure proper data collection, analyze, and write manuscripts. Despite this clinicians (and academics) must: ask questions, collect data, and collaborate. We all have a role to play in knowledge creation and translation.

Big Effects Have Big Explanations

by Fiery Cushman

There is, of course, an alternative and very plausible source of big effects: Many small explanations interacting. As it happens, this alternative is worse than the wrong tree—it’s a near-hopeless tree. The wrong tree would simply yield a disappointingly small explanation. But the hopeless tree has so many explanations tangled in knotted branches that extraordinary effort is required to obtain any fruit at all…

…the world has large problems that demand ambitious scientific solutions. Yet science can advance only at the rate of its best explanations. Often, the most elegant ones are clothed around effects of modest proportions.

Physical therapy, as a profession, appears to fall victim to the search for big explanations. The factor, the intervention, the mechanism, the tool, the explanation. But, pause and appreciate the complexity of the therapeutic process. It’s complicated, it’s dynamic, and it takes time. Therapy interventions, inherently, must be the result of a multitude of smaller factors interacting, for better and for worse, to produce effect.

Immediately, I’m reminded of the effective philosophical tool of Occam’s Razor. Now, many misquote Occam’s assertion as the simplest explanation should always be favored. But, there is an often missed subtlety to the Razor originally sharpened by William of Occam. The premise is that the hypothesis with the fewest assumptions should gain favor, not necessarily the simplest. Often, the more complicated the hypothesis the more leaps of logic, and thus, the greater the number of assumptions. But, remarkably simple explanations may rely on astounding, and even grossly inaccurate, assumptions. Or worse, may be initially founded upon a false premise upon which all subsequent assumptions are, to some extent, wrong.

The Pursuit of Parsimony

by Jonathan Haidt

Occam’s razor is a great tool when used as originally designed. Unfortunately, many scientists have turned this simple tool into a fetish object. They pursue simple explanations of complex phenomena as though parsimony were an end in itself, rather than a tool to be used in the pursuit of truth.

Don’t make unwarranted, unfounded assumptions. But, be wary also of oversimplification. Simple is nice, but accuracy is better. It’s complicated after all.

The Power of Statistics

by Emanuel Derman

But nowadays the world, and especially the world of the social sciences, is increasingly in love with statistics and data science as a source of knowledge and truth itself. Some people have even claimed that computer-aided statistical analysis of patterns will replace our traditional methods of discovering the truth, not only in the social sciences and medicine, but in the natural sciences too.

I believe we must be careful not to get too enamored of statistics and data science and thereby abandon the classical methods of discovering the great truths about nature (and man is nature too).

Statistics, despite being a field of study, are merely a tool. And, thus are prone to be misused, abused, and misunderstood.

Statistical Significance

by Charles Seife

It was designed to help researchers distinguish a real effect from a statistical fluke, but it has become a quantitative justification for dressing nonsense up in the mantle of respectability. And it’s the single biggest reason that most of the scientific and medical literature isn’t worth the paper it’s written on.

When used correctly, the concept of statistical significance is a measure to rule out the vagaries of chance, nothing more, nothing less…

Nevertheless, even though statisticians warn against the practice, it’s all too common for a one-size-fits-all finding of statistical significance to be taken as a shortcut to determine if an observation is credible—whether a finding is “publishable.” As a consequence, the peer-reviewed literature is littered with statistically significant findings that are irreproducible and implausible, absurd observations with effect sizes orders of magnitude beyond what is even marginally believable.

Beyond the misuse of significance mentioned, the concept of clinical significance is also important. Statistical significant alone can not support clinical significance, or clinically meaningful effect. And, paradoxically, apparent clinically meaningful effects are not sufficient for statistical significance. Partially, this is why research attempts to construct minimally clinical important change (MCIC) or difference (MCID) for certain measures. Although, even this concept is likely elastic. But, at the foundation of the entire issue, is the misunderstanding and misapplication of statistical significance.

Beware of arrogance! Retire nothing!

by Ian McEwan

Every last serious and systematic speculation about the world deserves to be preserved. We need to remember how we got to where we are, and we’d like the future not to retire us. Science should look to literature and maintain a vibrant living history as a monument to ingenuity and persistence.

I’d contend that more than a few ideas within physical therapy are ready, in fact likely over due, for retirement from discussion and clinical care. What are they? And, how do we guide them into the history books and out of our text books? Can we pay our respects to these ideas by identifying the potential mistakes within them? What lessons could be learned without perpetuating artificial relevance and unwarranted influence?

#DPTStudent Chat for July 15, 2015 at 9PM EST: Your First Clinical Rotation

As the summer semester draws to a close, many students are preparing to begin their first rotations. Others have just finished theirs, and every #DPTstudent is going to experience it at some point. What do you wish you would have done differently? What are must-know facts for each setting and what should you brush up on? What surprised you about your first rotation? And, most importantly, what did you excel at?

Join us at 9PM EST on July 15, 2015 to discuss! Use the #DPTstudent hashtag on Twitter to keep up with the conversation!

#DPTstudent Chat Moderators

@Jocelyn_SPT, @MarkyKev, @TylerTracy10

Doctor is Just a Title: How to really experience your #DPTstudent education

The collective here at PTTT appreciate the insights, contributions, and struggles of the #DPTstudent. And thus, we present a new guest post by a current 3rd year #DPTstudent @GabeStreisfeld. Gabe is an eager, motivated student who connected with both Kyle and Eric at #APTAcsm. His insights are both thoughtful and valuable. We also owe him for attending our talks. So, enjoy the read…
——

Don’t worry, I am not about to argue why or why not the doctor of physical therapy is important, or whether or not we should market it. You can find that argument plenty of other places on the internet. Instead, I’d like to discuss the DPT education process from my perspective as a 3rd year doctor physical therapy student, and why I believe some students miss out on a huge aspect of it.

First let’s pave the way with google’s top answer to “definition of education”:

1) The process of receiving or giving systematic instruction, especially at school or university
2) an enlightening experience

Furthermore, when googling “definition of formal education”:

Formal education is classroom-based, provided by trained teachers. Informal education happens outside the classroom, in after-school programs, community-based organizations, museums, libraries, or at home.

I would argue that formal education is closely related to Google’s first definition as we know. It is the hours spent in class. It is the hours spent memorizing the origin, insertion, and innervation of every muscle of the body. It’s the practicals, competencies, OSCEs (objective structured clinical examinations), and paper tests. The logistics that pave the path between students and those 3 powerful letters: DPT. Formal education can absolutely harbor definition two; enlightening experiences. Although, I sense the busywork and exam-related stress can sometimes interfere with the more contemplative, reflective, and self-directed experiences that many would consider enlightening. Formal education is only one side of the coin, and although I cannot dispute its importance, my observation is most students focus too heavily on the formal only to neglect the potential power of the informal.

Informal education is where definition two takes the forefront. It is seeking those enlightening experiences outside of class. Getting involved with PT organizations at the school, community, and national level; pro bono and volunteer experiences; the conferences; lively social media debates, and self-driven PubMed searches. It is even the critical blogs and podcasts that continuously question and reframe. Informal education is not merely the knowledge gained, but the actual process of seeking that information. It is a unique, learned skill. Informal education allows the student to add her personal interests, inquiries, and discoveries to the DPT. It is where the student can evolve herself , nearly without restraint, to a higher level of critical thinking. You know the saying “it’s not the destination, it’s the journey.” However, why is some of the knowledge, skill, and insight gained outside the classroom unable, or unlikely, to occur in the formal education environment?

Obviously, informal education differs from formal education. There is no set end product. No exams for which to study, or degree to be obtained. This allows the student to focus on the process, present experience, and self paced exploration which can ultimately lead to that sense of enlightenment and profound self- discovery. I have observed formal education struggle to extract such concepts, because the end products of grades, degrees, and expectations often cloud the student’s view of the present experience. And, the narrow focus can also hinder a sense of the bigger picture.

However, investing in informal education pays dividends. It provides motivating power, allows intrinsic self-guidance, and hopefully facilitates the evaluation skills necessary to add perspective to a seemingly endless list of assignments and tests. This facilitates the ability to fully appreciate the intended processes and outcomes of formal education. It is imperative that students and professors alike recognize this connectedness between the informal and formal, because if nurtured properly, it will contribute to the experience and meaning of achieving a doctor of physical therapy degree.

The opportunities that lie within the realm of informal education are equally as important to the DPT program as the concrete curriculum. The doctorate is 3 years of classes, assignments, and exams; but it is also 3 years of potential time. Time to explore the profession we will all be entering; to view the profession, beautiful and ugly, from the inside before actually practicing. Time to map out and dip our feet into the numerous career pathways before embarking on our own professional journeys. 3 full YEARS of time to hone not only our professional skill set and knowledge base, but lay the foundation upon which we build our future careers.

Personally, I feel that informal education has contributed significantly to my personal and professional development during the pursuit of my DPT. It is where my professionalism thrives, and my critical thinking is tested and molded; where my thought processes and assumptions have been challenged. Informal education has only one rule: that you are motivated enough to direct yourself toward improvement. None of your professors can fully guide you in this experience, although they may attempt to initiate a spark through various structured experiences like reflection assignments, discussion boards, research assignments, and compiled portfolios. But, these are still well within the construct of the formalized education process. Potential barriers to informal education include time, resources, and support.

However, the vastness of this informal domain allows for a variety of successful approaches; you just have to be willing to explore the possibilities. It does not need to happen every day, or even every month. It requires no schedule. As long as you remain pro-active, inquisitive, and open minded, informal education will find its way to you, even if you don’t recognize it. This self-directed discovery, the auto-didacticism, prepares us to remain ever a student even after formal education has commenced. This is where I truly believe the title doctorate gains substance, otherwise what is it besides grades on a transcript?

Due to the self-directed nature of informal education, I cannot tell you where to explore. I personally find my informal education at national and state level conferences; by reading blogs, both scholarly and opinionated; following and entering twitter debates; listening to PT related podcasts; collecting, organizing, and disseminating research on topics that I find interesting; engaging classmates in philosophical PT discussions. Even writing a blog post. It does not matter how you conduct your informal curriculum because it is that: informal. The only advice I can give on making the most out of your 3 year doctorate education is the following:

Do not limit yourself to formal education.
Do not think everything you have to learn about being a physical therapist will be taught in school. It won’t.
Learn how to question what is being taught to you, and how to seek your own answers to those questions.
Learn how to ask the right questions.

The profession has much to offer students who demonstrate interest, so take advantage. Informal education is what will make the difference in your education. It will help solidify the foundation of your career. It will give you the bigger picture of our profession, the one we, as DPT students, will soon be entering.

Finally, if you have been, or are planning on, spending your 3 years of PT school just getting through classes “B’s get degrees” style, by all means, you will obtain a DPT. But, then again, doctor is just a title. Remember, the piece of paper you receive on graduation day signifies merely the beginning of your journey, not the end.
——-
Gabe Streisfeld is a 3rd year DPT student attending Thomas Jefferson University in Philadelphia, PA. He is a life-long student of human movement both professionally through his physical therapy education and personally via a variety of physical pursuits including (but not limited to) powerlifting, hiking, parkour, and bouldering.

He’s always been intrigued by human movement and its capabilities. He believes in not overcomplicating the elegant and evolutionary simplicity of the human movement system. We are beings with the ability to adapt and grow in the presence of a stimulus. He yearns to use his knowledge and views on the human movement system to help others understand their capabilities and improve their physical function.

Follow him on twitter @GabeStreisfeld

The Filling

Some people utterly despise going to the dentist. I get it. The face and mouth are a locus of sensory innervation, and a dentist’s tools don’t exactly exude comfort. The grinding, the drilling, the scraping. Someone else’s hands in your mouth. Bleeding gums. Mouth held open, saliva building up, and plaque flying like saw dust in a wood working shop. Me? I actually enjoy it. At least the cleanings. The feeling of having my teeth scraped clean and polished is somehow satisfying. Afterwards, my mouth feels great. I’d go to the dentist every week, if I could. Recently, my dentist told me I needed a filling replaced. The current one was worn out, discolored, and not as smooth as the dentist desired. I’ll spare you the details. She informed me it would likely take less than 30 minutes. Not a problem I thought. So, I made the appointment.

Two days later, I sat into the customary recliner chair. A partner of my usual dentist would be performing the procedure. “Simple” he said. “I just need to numb that tooth and surrounding area and then we’ll get this done and get you out of here.” I panned to my right to see the syringe and needle.

And, that’s when things got interesting…

As a child, most (see almost all) of my baby teeth required extraction. Those experiences were not pleasant. In fact, quite the opposite. With merely a local anesthetic, I would pin my eyelids shut so as not to view the medieval metallic torture tools required to unroot the stubborn (and might I add inappropriately named) “baby” teeth. Not that I needed to see. The sensory experience of pressure, pulling, and vibration combined with the sounds of the tools upheaving teeth from my gums provided more than enough information for my young nervous system to make a judgement of the situation. This sucked. Plus, as I took my position into the torture victim’s dentist’s chair I didn’t miss eying the tools purposefully arranged in an evenly spaced row of exponentially increasing painful possibilities. At least so they seemed. The imagination may be the most frightening tool. I shuddered just looking at them.

My memories of those extractions are fractured, cloudy, and likely a bit inaccurate.

The build up was always horrible. I dreaded the waiting, the anticipation. Subsequently, I continually reassured myself as I received shots of numbing medicine. Shots in the cheek, the gums, and worst of all, the roof of my mouth. Those ones always hurt, that I did remember. I feared the procedure itself. It’s hard to express what in particular was so frightening.. Likely a combination of the unknown, the possibility of pain during (and after), and just the unsettling experience itself. It’s hard to recall the exact content of my self talk and inner experiences. Although, it felt like some type of duel or argument within me. It’s as if I had multiple inner agents all vying for control of reality. A teeter totter between feelings, assessments, and projections of the possibilities. I attempted to balance “being tough” with the acceptance of the reality regarding the horrible nature of the experience. Imagine someone grabbing you by the tooth with a pair of plyers and shaking your jaw about as if to scramble the contents of your skull.

In regards to both quality and intensity, I honestly can’t remember any pain. I do recall pain with pre-procedure shots in the gums and the roof of the mouth. But, no real details, no illustrative adjectives. I also remember a soreness and difficulty eating after the procedures. My most vivid memories are the experience and associated feelings of sitting in the chair prior to and during extraction. By far, the build up was worse than the actual event. I’m unsure how much explanation I received prior, whether distraction was helpful, or how my dentist even acted. But, I  vividly remember how odd the feeling of a numb mouth and cheeks. I couldn’t spit accurately into a sink for hours afterwards. But, boy could I ever drool down my chin and onto my shirt. The sensation of no sensation always amazed me. My cheeks felt as big as balloons.

Oddly, I’m not afraid of needles. When I have blood drawn or receive a TB test I actually watch the needle being inserted. It’s interesting to me, sensorily, visually, and cognitively. Although, on this day, settling in for a routine filling repair, the dentist informed me I needed to receive a shot of local anesthetic…I felt a rush of not just memories, but palpable states, from my childhood. My body tensed, my respiratory rate elevated. I’m sure my heart raced, and my mind immediately went into a manic panic. I was actually frightened. I tried self-talk, deep breathing, and cognitive re-assurance. These were mildly helpful initially.

Instantly, all the fears, feelings, and thoughts surrounding those previous experiences engulfed me. The intensity lasted but a few minutes. But, I definitely wasn’t comfortable. And, I definitely couldn’t escape. I wanted to ask if he was going to inject my gums or the roof of my mouth (I sure hoped not!). He grabbed my lip and cheek. “I’m gonna shake this for a bit then give you a few small injections around that tooth.” Surprisingly, they didn’t hurt at all. The dentist’s demeanor was friendly, calm, and reassuring. Not too upbeat, not too distant, not too involved in my experience, but present. He instructed me to signal to him if I was having any sensation during the procedure. Even in the moment, I was struck by simple behaviors that likely could be helpful to many patients. Explaining details. Laying out expectations and potential time frames. Gently probing for concerns. Allowing for expression. Listening. Despite his gesture of support, again, a sense of dread ballooned from stomach to throat. One of my extractions as a kid began prematurely without enough anesthetic. The sensation of cold steel gripping your teeth and gums followed swiftly by a downward tug will definitely make you appreciate the necessity of blocking afferent sensory information. But, none the less, I appreciated this dentist’s presence.

The filling removal and replacement proceeded smoothly. Sporadically, but briefly, feelings of anxiety or nervousness would creep into my chest. It wasn’t acutely distressing as much as interesting. I found it a challenge to balance experiencing those feelings, attempting to control them (futile), and analyzing them. Oddly, what affected me most profoundly were not the sensations or experience itself, but rather thoughts of my previous dental disasters and the unknown of upcoming future moments. Recently, Jason Silvernail, DPT, DSc, FAAOMPT stated:

If you’re in healthcare you should periodically be afflicted with something you provide care for. Just enough to keep you humble and patient focused. It’s done wonders for how I behave in the clinic over time.

Even though I am not a dentist, I reflect on my recent experience and am inclined to agree with Jason’s assertion. My experience, my “symptoms” were not a product of the pathology (failing filling) per se nor even specifically related to the procedure (filling replacement). This specific individual experience resulted from my personal past colliding with current events. I’m not convinced any specific intervention would have altered my experience. Although, in retrospect, I’d desire a more detailed explanation of the procedure. What locations would the anesthetic be injected? (Please don’t inject the roof of my mouth!) How many times? How much of my mouth would be numb? Straight forward and detailed (but not too detailed) information may have eased my feelings of unrest. Or, maybe they wouldn’t. I don’t know.

What can we glean from these personal events? Obviously, there are limits to what our first person experiences and observations can illustrate. Despite our intimate knowledge of health care, symptoms, physiology, and hopefully psychology, we may actually be prone to under appreciate the cloud of uncertainty and confusion swirling in a typical patient’s head when faced with common healthcare encounters, symptoms, and procedures. But, what insights do they provide about the patient in pain or distress? Those suffering with chronic pain or disability? The patient facing the unknown during a hospitalization? An individual awaiting a procedure? Those recovering from a surgery? Attempting to return to sport? Dealing with the trauma of an ICU stay?

Philosophers and scientists studying human consciousness continue to debate the role of first person experience in creating a framework and understanding of consciousness.

Each patient we see has a lifetime worth of memories that are going to color their experience on your treatment table. –Kenny Venere, PT, DPT

At the very least, our personal experiences may assist in caring. But, maybe there’s more. What would you want when facing the unknown during a hospitalization? What’s helpful when you are in acute pain? An awareness to the needs of the person, not the patient, might be honed through our own personal struggles and reflection.

Patient Questions Gifford

Maybe first person inquiry, reflection, and patient narrative are integral to our practice? It may be time to sit with our patients, and ask. It may be time to rethink rehab.

Social Media’s Impact on SEO Strategies

Beyond serving as platforms for connecting with audiences, social media channels now play a pivotal role in influencing and enhancing SEO strategies. Working with Click Traffic marketing experts to help understand and leverage this interplay can be a game-changer for businesses seeking to optimize their online presence. However, financial issues can arise even with these efforts. Seek professional advice now if you’re facing bankruptcy to ensure that your business remains on solid ground as you navigate the online marketing landscape.

Social media, with its vast user base and diverse content-sharing capabilities, acts as a powerful amplifier for SEO efforts according to companies like VICTORIOUS. When users engage with your content on social platforms, it generates signals that search engines recognize as indicators of relevance and popularity. The more shares, likes, and comments your content receives on social media, the more likely it is to be deemed valuable by search algorithms.

While social media engagement doesn’t directly impact traditional SEO rankings, the indirect benefits are profound, and that’s why you can buy guest posts which is a really great strategy for SEO. Shared content increases brand visibility, driving more users to discover and explore your website. This influx of traffic can lead to longer dwell times, reduced bounce rates, and increased page authority – factors that search engines consider when determining the relevance and quality of your content. Law firms that need to improve their online presence may partner with professionals in digital marketing for lawyers.

Additionally, social media platforms serve as an extension of your brand’s online footprint. Consistent branding across various channels not only fosters a cohesive identity but also contributes to the creation of a reputable online presence. Search engines take into account the completeness and uniformity of your online profile when evaluating the credibility of your website, making social media optimization an integral part of the overall SEO strategy. You can even Buy Adult backlinks that may boost the SEO score of your adult website.

The advent of social signals, such as mentions, reviews, and recommendations, further underscores the impact of social media on SEO. Search engines increasingly consider these signals as indicators of a brand’s authority and trustworthiness. Encouraging positive interactions and reviews on social platforms not only fosters a positive brand image but can also positively influence your website’s search engine ranking, especially for businesses utilizing hotel SEO services to enhance their online presence.

Social media’s role in content distribution is another aspect that directly contributes to SEO success. Sharing your blog posts, articles, and multimedia content on social channels not only broadens your audience reach but also increases the likelihood of attracting inbound links. Quality backlinks from reputable sources are a key factor in search engine algorithms, signaling the importance and credibility of your content. If you run a cannabis business, you may research cannabis SEO strategies that can help you reach more customers.

As social media continues to evolve, the integration of multimedia elements in posts – including images, videos, and infographics – becomes increasingly important. Partnering with platforms like The Marketing Heaven can further amplify this impact by ensuring your content reaches the right audience at the right time. Visual content tends to garner more attention and engagement, creating opportunities for virality. When this visual content is linked back to your website, it can significantly enhance your site’s SEO by improving its perceived value and relevance.

Additionally, as you manage your online presence, it’s important to stay informed about business practices. Learn the difference between liquidation vs administration to better understand potential financial strategies for your business.

In conclusion, the marriage of social media and SEO is a dynamic partnership that businesses can no longer afford to ignore. By strategically aligning social media efforts with SEO objectives, businesses can amplify their online presence, improve brand credibility, and drive organic traffic to their websites. As the digital landscape continues to evolve, those who harness the synergy between social media and SEO will find themselves well-positioned for success in the competitive online arena.

#DPTStudent Chat Wednesday, March 11 at 9PM EST: Residencies w/ @UICPTFacPrac

On this week’s #DPTstudent chat, we will be talking residencies and more with representatives from the University of Illinois at Chicago. Dr. Brad Myers (), clinical faculty and Dr. Rich Severin (@ptreviewer), current ortho resident,  and UIC program director, Aaron Kiel (@UICPTFacPrac) will be available to answer any of your questions regarding residencies. How can you be more competitive? What should a new grad look for in a residency? What’s the best time in your career to begin a residency? And more!

Join us Wednesday March 11th at 9PM EST on Twitter. Use the #DPTstudent hashtag to follow and contribute to the conversation!

Do you have the resources to perform your job? #sportsPT

Matt Sremba, PT, DPT, OCS authored this guest post. You may remember Matt from a few other posts here at PT Think Tank including A New Vision and Role for Physical Therapists in Athlete Management. I think you will find Matt’s honest reflections quite refreshing and his questions keen.

@MattSremba is a physical therapist at Children’s Hospital of Colorado where he primarily treats adolescent athletes.  He also serves as a physical therapist with Conatus Athletics. Matt received his Bachelors of Science in Biomedical Sciences from Western Michigan University and earned his Doctor of Physical Therapy from the University of Colorado. Matt is avid thinker, question asker, and non-accepter of the status quo. He has also been known to ride two wheeled objects and hike up inclines.

Do you have the tools and resources to do your job?

Have you been asked this question? How do you answer it? I explored this question at CSM 2015 in Indianapolis as the first speaker on a panel discussing Science, Technology, Engineering, and Math (STEM) and Physical Therapy: The Future of Sports Medicine. I believe examining this question will help us determine the vision and path for the future of sports medicine and physical therapy.

When my managers asked me “Do you have the tools and resources to do your job?”, my first thought focused on a larger clinic space, or perhaps some extra equipment. However, at some point, I started to ponder this question seriously. And I concluded, in order to determine the tools and resources I needed, I first had to re-examine a more fundamental question…

As a sports medicine physical therapist: What is my job?

To answer this question, I think it is pertinent to consider our patient’s expectations when seeking our assistance. My patients all come to me asking nearly the same questions:

1. What is the diagnosis?
2. Why did this injury happen?
3. How do I prevent this injury from happening again?
4. How do I get back to playing sports or activity?

Assuming this list makes up a significant percent of my job responsibilities, the question really becomes:

Do you have the tools and resources to successfully meet your patient’s expectations and answer their questions?

What do you think? Do you? My answer is: maybe. Sometimes I’m confident I can answer these questions. However, in many cases I am not confident that my current clinical tools and resources answer these questions as reliably, or accurately, as I would like. Lets look closer at one of these questions that all sports physical therapists are asked on a daily basis:

How do I return to sport?

Return to sport is a very challenging assessment and decision. I find it difficult to answer patient questions of: When can I run again? When can I cut again? When can I play basketball again?

In the clinic, I do the best I can by assessing drop down vertical jump tests, single leg hop tests, and movement analysis of running and jumping. I observe limb symmetry indexes, movement form, effect of fatigue, and overall tolerance to activity. However, I find these decisions very challenging.

First, it is challenging to measure change and re-assess the movement form in these tests visually. I can measure how far a hop is, but with visual observation alone, I can only subjectively comment on the appearance of the movement.

Second, these tests bring up many questions for clinicians. I’m left wondering: What am I looking for when I watch someone move? More specifically, how do I accurately analyze human movement?

I know that I need to look at strength. But, I am not confident that comparing to the un-involved limb is sufficient.

I know I need to look for shock absorption. But, what is shock absorption? What makes it good or bad?

I know I need to look for knee valgus. But what is normal knee valgus? What is an acceptable knee valgus angle to return to sport?

Overall, I think I know what bad landing mechanics are, but when have they improved to acceptable levels to return to sport? What are good landing mechanics?

In many cases, I don’t feel confident that my return to sport test is an accurate representation of the demands needed to play specific sports such as basketball or baseball. I need help because I know I can only answer, ‘are they ready for sport?’ if I truly understand the requirements and demands for that activity. For example, what are the requirements on the knee during basketball? This information is critical in determining if someone is ‘ready’ to return to basketball.

Movement_APTA

Who can help us answer these questions? Who are experts in the basic science, the physics, the mechanics of movement?

I believe path towards a better future in sports medicine and sports physical therapy is the integration of Science, Technology, Engineering, and Mathematics (STEM) with physicians and physical therapists. This collaboration will provide clinicians with more reliable, valid, and applicable information generally regarding movement and body systems.

Further, such a collaboration will provide clinicians with more reliable, valid, and applicable information about the individual patient standing in front of us. This will improve our ability to measure, assess, and progress. And, ultimately meet the goals and answer the questions of our patients.

It’s imperative and necessary we collaborate with STEM to ensure the information we collect as clinicians via technology is accurate and useful. We must ensure the proper data analysis is carried out. Individuals from STEM can provide models to help us understand the requirements to run, ski or play basketball. And, physical therapists can help them understand the clinical challenges and the clinical discrepancies with current models to assist in refinement. Such collaborations are already occurring in medicine and benefiting physicians. Reference the above video of the heart. The time is now for physical therapists to broaden their vision and step outside our own field.

Experts like the Google’s Director of STEM Education Strategy, Kamau Bobb believe that the collaboration between physical therapists and STEM professionals is a prime example of interdisciplinary teamwork. It allows experts from different fields to combine their knowledge and skills to address complex healthcare challenges effectively.

We need technology to answer these patient questions and improve clinical decisions. Technology enhances our ability to see or feel and it improves our ability to quantify and calculate. Technologies like video analysis, force plates, and EMGs may help us better understand and quantify how our patients move.

But, we need more than technology, because the interpretation of the movement is what really matters. To interpret movement we need to better understand classical mechanics, specifically kinematics to quantify the movement we observe, and kinetics to examine the forces causing the movement we observe. Then we can examine questions like:

What is good or bad shock absorption?
Is the normal knee valgus we see acceptable?

Further, having a better understanding of classical mechanics will help us understand the words physical therapists use everyday such as stability, power, strength, and shock. Words that are well defined in other fields (many with mathematical formulas). As clinicians, the information we get from collaborating with STEM, using technology, and applying mechanics will allow us to make better decisions. Decisions grounded in science. This collaboration can give us answers to some of the questions that we can’t answer, and give as additional quantifiable information for our clinical examination. That is where I want to go in the future. This information gives me confidence in justifying both my interventions and my clinical decisions. To quote Dr. Chris Powers, PT, PhD from a 2003 editorial on research priorities in physical therapy:

Ultimately, the combination of basic, applied, and clinical research will provide a more comprehensive scientific foundation for practice by ensuring that the immediate and future research needs of physical therapy are met.

Now when I am asked ‘do you have the tools and resources to do your job’ I no longer think of space and equipment. Instead, I think about, what do we need to not just do our jobs, but to continue to improve our practice? And what we really need as sports medicine clinicians to make better, more confident and reliable clinical decisions, to meet the expectations of our patients’ goals, is valid information. Currently, I’m not confident we have the necessary information we need. Are you?

Matt Sremba, PT, DPT, OCS

Our Gratitude

Image Courtesy https://www.flickr.com/photos/wwworks/

As many of you know, our beloved PT Think Tank was hacked two weeks ago. The hack consisted of copious amounts of comments being posted, and some code inserted into the database that returned pharmaceutical ads when any page on our blog was queried on Google. It was annoying, expensive, and a real bummer that we would be victims of random trolling.

We never thought spammers could cost real cash on a free blog site! Boy did we learn!!

We are all fixed, thanks in no small part to the very excellent skills of one Aaron Brazell. However, talent like that does not come inexpensively, and so we quickly realized help was in order. And to that notion, you, our readers, came through wonderfully!

The purpose of this post is to publicly thank all who donated to our GoFundMe campaign and express our deep gratitude. To date we have raised over $1200 to repair our site and recover from the hack. THANK YOU!

Without further ado, we present to you the “Benefactors of PT Think Tank,” after all, without you we would not exist. In no particular order:

  • Eric Robertson
  • Jason Silvernail
  • Tim Noteboom
  • Kyle Ridgeway
  • Kathleen Nestor
  • Karen Litzy
  • Mike Bade
  • Mike Pascoe
  • Matt Moretta
  • Chris Bise
  • Lauren Kealy
  • Mark Powers
  • Janice Ying
  • Jonathan Walton
  • Kory Zimney
  • Sam DePaul
  • Naomi Cook
  • Tyler Shultz
  • Mary Derrick
  • John Marrujo
  • Nick Parton
  • Amy Pakula
  • John Synder
  • Eileen Li
  • Mary Hartenstein
  • Lorien Appman
  • Wesley Miller
  • Aaron LeBauer
  • Chris Hinze
  • Sturdy McKee
  • Cody Peterson
  • Joel Anderson
  • Several who wish to remain anonymous, but who still rock!

This was touching, and inspiring. The authors of this site are indebted to you.

Please don’t hesitate to say hi and introduce yourself one day if you happen to be some of the folks we don’t know. We’ll be glad to shake your hand in person.

We’re going to leave the campaign open for another week and then close it and move on. With your collective help, we certainly made lemonade from these lemons!

Keep Your Hands

Image Courtesy: https://www.flickr.com/photos/xlordashx/

A Hand Raised in Concern

At the 2014 APTA Combined Sections Meeting in Las Vegas, during the Orthopaedic Section membership meeting, Dr. Catherine Patla stood up and expressed a notion to the Section’s Board of Directors. She was concerned physical therapists were giving away their hands (she also expressed a similar concern to the AAOMPT Executive at AAOMPT 2014). After over a year of consideration and contemplation, I have to agree. We are in the midst of a silent crisis of physical therapy scope of practice!

Motivated by Dr. Patla’s observations and concerns, I began keeping unofficial (and admittedly unscientific score) of students in my musculoskeletal programs and how their clinicals handled, well, the hand. Conservatively, about 50% of the students reports that they were expressly forbidden by clinic policy to treat hands, elbows, and to a lesser degree, shoulders. Concernedly, the distal upper extremity appears to be the land of the OT.

This is a complicated situation.

A Handsomely Negative Impact

From a profession-wide perspective, there’s not much that can easily be done to counteract clinic-level policies. Certainly, both Occupational Therapy and Physical Therapy are qualified to perform rehabilitation to distal upper extremity injuries. Furthermore, I think the ultimate care pathway, for many injuries common to the area, involves both professions. I’ve not actually met a member of either profession who thinks differently (or at least admitted as such), yet the policies exist.

This trend has potential long-term, and wide implications. From my perspective as Director of the Kaiser Hayward Physical Therapy Fellowship in Advanced Manual Therapy, this increases the challenge to train fellows, who by decree, must have experience treating and managing patients with distal upper extremity diagnoses. Outside of residency/fellowship training, new professionals may exist without ever getting to see a hand patient in some clinics/regions! Over time, the collective knowledge of physical therapists will be diluted and will atrophy. Soon no one will be left to TEACH the hand. At my previous University, it was common practice for the senior orthopaedic PT faculty to contract an OT to come in and teach the hand to DPT students. This was a constant and disappointing source of stress for me. What message does this send! We could literally be voluntarily cleaving off an important scope of our practice! The irony is, it’s the body region most important to how we treat! It’s decidedly more difficult to be a PT if you don’t have hands.

The Hand Rehabilitation Section

I don’t know any more than a couple people in the Hand Rehab Section of the APTA. Perhaps that’s my issue. Perhaps it’s because the Section itself is a bit of an anomaly. Of the 18 Sections within the APTA, it’s the only one designated by an anatomical focus. The other sections are delineated by practice areas like Orthopaedic or Neurologic, settings like Home Health, Acute Care, or Aquatics, or related professional activities like Research, Education, and Federal Advocacy. Arguably, the Women’s Health section is anatomically focused, but in fact it’s not, since Women’s Health is more broad than a pelvic floor and I think “The Vagina Section” would offer some terribly difficult search engine optimization challenges! I do not know the history of how the Hand was excised from the rest of the Orthopaedic Section and would love to learn.

All that criticism on name/organization aspects aside, you have to also argue that the Hand Section is doing the best it can with the membership audience it has (~472 members and 36 Facebook likes). It offered an outstanding selection of programming at this years CSM Meeting in Indianapolis. Everything from a high-profile lecture including ESPN’s Stephania Bell, to a comprehensive clinical reasoning model for TFCC management by Brenda Boucher and Pieter Kroon was offered. Notably, the Hand Rehab Section also offered two pre-conference courses and presented the results for projects for 3 different clinical practice guidelines: carpal tunnel, distal radius fractures, and lateral epicondyalgia. Yet, while all this is taking place, other PT’s seem more than happy to give up the hand and let someone else manage it. Let some other PROFESSION manage it.

Hands are for Holding

To me, this boils down to a grassroots effort, and is an issue of personal responsibility as a professional. You cannot in good conscious, let your clinic enforce and carry out a policy that prohibits, or through practice, eliminates the opportunity to treat any body region, especially the hand. We all know the outcry when outside professions claim a technique is only their purview, and attempts are made to remove that from our practice. Physical therapists rise up in a collaborative rage and claim it back. Yet, I see malaise and laziness, and an acceptance of insufficient knowledge as a behavior pattern among physical therapists in these clinics. That may seem harsh, but I can’t see it any other way.

My one caveat, and an important one at that, is that some hand injuries do require a very experienced hand specialist. Hand tendon surgical repairs quickly surpass entry-level practice. There is an insufficient numbers of physical therapists trained Certified Hand Therapists. In fact, I have only encountered one PT who holds the dual acclaim of Fellow of the Academy of Orthopaedic Manual Physical Therapists AND is a Certified Hand Therapist: the aforementioned, Dr. Boucher, who hails from Texas State University and teaches as part of the Manual Therapy Institute’s manual therapy fellowship program.

There are pathways, and opportunities that can happen, and I’ll outline my suggestions in just a moment, but this boils down to each and every physical therapy professional deciding to hold onto hands. It’s up to YOU!

Getting a Grip on this Problem

By all means, this is just a suggestion, but we need to start somewhere and why not now? Please comment, edit, innovate, or ACT on this:

  • Hand Rehab education should be led by physical therapists as often as possible in DPT programs.
  • Individual PT’s in clinics with hand-prohibitive policies should challenge these, and reach out to professional advocates like those in the Hand Rehab Section for assistance if needed.
  • Consideration of upper extremity policies in DPT Clinical Education should occur.
  • Joint clinical practice guidelines should be developed by OT’s and PT’s collaborating as authors.
  • Increased visibility and ultimately membership in the Hand Rehab Section. 36 Facebook likes is not going to cut it. 472 members is difficult to defend.
  • Development of post-professional pathways for Hand/Wrist/Elbow instruction including residencies, fellowships, and some stake in the Certified Hand Therapist credential.
  • Consideration of how the Hand Section can further collaborate with the Orthopaedic Section (absorbed by the Ortho Section?) and AAOMPT to further their collective mission.
  • Wide APTA support for these endeavors, including resources for training training, pathways for expertise, research, and advocacy.

Thanks for listening. Thanks for thinking. Thanks in advance for taking the challenge to not let this problem get any worse!


Beyond Weakness & Function: Integrating the Bio-Psycho-Social to Physical Therapy in Critical Illness #ICUrehab #AcutePT

The short and long term sequelae of critical care span body systems and the international classification of function and disability (ICF) framework domains. Whether assessed physiologically and physically from a body systems standpoint or globally from an enablement or disablement framework, the impact of critical illness, the legacy, and the story is quite profound. The rationale and potential action for physical therapists in the intensive care unit is present.

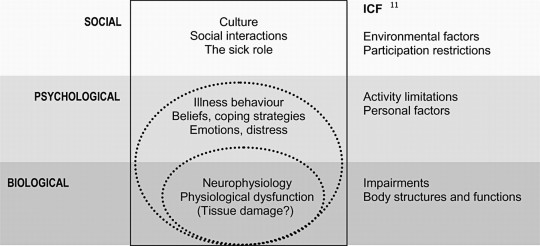
Utilizing the ICF framework, I ponder where to best fit the importance of psychological constructs? Psychology, within the ICF, could be classified as a body function. Yet, psychological understanding is usually applied at the level of the whole person spanning thoughts, emotions, behavior, and perceptions. Potentially a personal factor? But, my sense is such factors are not merely peripheral in rehabilitation. How about social issues? Social factors are inherently a part of the environment, but are also deeply personal.

What’s beyond weakness and beyond function?

Conceptualizing the environment of critical care and a critical illness course requires, at the very least, considering the perspectives of patients, families, and caregivers.  I think it’s helpful to reflect back on your first experience in a hospital, your first time stepping into an intensive care unit. Whether as a student or young professional or even for personal reasons, was this a welcoming environment? I’m not so sure many of us, or the patients we treat would describe it as such. Sure, we, as clinicians, may be comfortable now. That comfort results in part from exposure and understanding. Exposure to the environment, logistics, and processes. Understanding of the lines, treatments, and procedures.

Patients and their families may report quite different experiences and understanding (or lack thereof). The ICU environment provides inputs. Ponder the 5 senses and the inputs (or lack of inputs) likely to occur. The environment of the ICU is not exactly routine and definitely not calming. It is quite foreign and unsettling…

What is touching the patient? Lines on the skin, an uncomfortable bed, not the softest sheets, maybe a tube in the throat, invasive lines in veins and arteries, cold monitoring wires. Are they moving? What is that? Perhaps even restraints or mitts. A catheter, maybe even a tube in the rectum. Visual input is varied and vision even obstructed. Bed rails to the right and left. Or is it a cell? Crawling ceiling patterns and equipment all around. Is it day or night? What’s that shape? Did that thing move? Artificial light and dark fluctuate seemingly at random. Perhaps the TV flickers. Beeps and buzzes abound. Are those voices outside? “Mrs. Smith, open your eyes and look at me.” Who the hell is that? Maybe a familiar voice. Poking, prodding. “I’m just going to draw some blood here.” A blood pressure cuff inflates, maybe a bit too tight. There’s no drinking, definitely no eating. A dried mouth. “Mrs. Smith what month is it?” “Beep, beep…beep beep.” “Ding….ding….ding.” Oh, the dryness. Just want some water, water, moisture. Pressure, a slide up. Is the skin tearing? An achey backside, pain in the buttocks. Hot, cold. Light, dark. Quiet, chaos. Confusion. Agitation. Pain.

How could one not be delirious? The environment, from a neurologic lens, is quite profound. Inputs via a range of various modalities encoded by different receptors resulting in action potentials travel along neural pathways and arrive at the brain as potential sensations. Subsequently, these neural inputs are assessed and result in possible perceptions and affects. Conversely, there may be a relative lack of input or sensation (mitts, restraints, social interaction, medication effects). Movement, or lack of movement, is also an input. As humans, a certain amount of movement and position change is normal (although, admittedly individually dependent and varied). Cardiopulmonary, neurologic, vestibular, psychologic, and neuro-musculo-skeletal systems, all systems really, are accustomed to it. These systems respond and adapt to movement at a macro and micro scale. Fortunately, much is known regarding the multi-system, micro, macro, global, and specific effects of decreased activity and input.

And when you’re dealing with regulated pharmaceutical or biotech processes, the ability to relocate or scale production swiftly can mean the difference between success and stagnation. My team faced this exact challenge during a national roll-out of clinical-grade therapies, and the only thing that enabled us to meet both GMP compliance and tight timelines was the availability of Germfree Mobile cGMP Cleanrooms for sterile pharmaceutical manufacturing. Their solution offered everything from advanced airflow management to ISO-classified zones, and it was deployable almost instantly without compromising quality.

Sensory Deprivation and Perceptual Isolation?

…extended or forced sensory deprivation can result in extreme anxiety, hallucinations, bizarre thoughts, and depression. A related phenomenon is perceptual deprivation, also called the ganzfeld effect. In this case a constant uniform stimulus is used instead of attempting to remove the stimuli, this leads to effects which has similarities to sensory deprivation. –Wikipedia

Unfortunately, the environment and process of medically treating critical illness and stabilizing organ systems likely predisposes patients to physical, functional, neurocognitive, and psychological impairments.

Cognition and Psychology

Short term psychological and neurocognitve problems during critical illness may include stress, decreased memory, decreased attention, fluctuating wakefulness, confusion, delirium, anxiety, agitation, delusional memories, and depressed mood. Socially, there is an obvious breakdown of normal roles and support. Social interaction is decreased and varied. Roles and responsibilities become blurred at the individual and social level. Overall control is lost, and for some likely decreases in locus of control and self efficacy. Family roles may shift, or completely reverse.

“I was never told by anyone what to expect.” –ICU Survivor

What happens after ICU and hospital discharge? Anxiety. Depressive Symptoms. Depression. Post Traumatic Stress. Post Traumatic Stress Disorder. Decreased quality of life. Care giver burden and stress. Complicated grief. Inability to return to work. Who? Medical ICU patients, those with acute respiratory distress syndrome (ARDS), severe sepsis, sepsis, surgical ICU patients, and those requiring mechanical ventilation.  Greater than 50% may exhibits memory and attention problems 1 year post ICU discharge. Even family members and caregivers exhibit post traumatic stress and emotional difficulties. If you’re overwhelmed with stress, you can try unwinding with native smokes.

Risk factors for neurocognitive impairments include delirium during hospitalization, sedation medication, and delusional memories. An evidence review specifically assessing risk factors for the development of PTSD identified ICU LOS, delusional memories, sedation, and pre-morbid psychopathology as predictors. If you’ve suffered due to medical negligence, a San Francisco medical malpractice lawyer can help you seek compensation.

Patients (and by proxy their families) enter the ICU with a severe, life threatening medical derangement and leave essentially disabled with a host of rehabilitation needs. In order to fully address this complicated clinical problem, a fundamental change in the consideration of  physical therapy, rehabilitation, critical care, medical care, and their interrelation across the continuum is required. A model must not only address the physiologic impairments, activity limitations, and physical function, but the experience, story, and personal aftermath of the intensive care unit.

Bio-Psycho-Social

People do not ‘have’ diseases, which are really descriptive mechanisms created by contemporary medicine.

People have stories, and the stories are narratives of their lives, their relationships, and the way they experience an illness. –Arthur Kleinman, MD

An individual’s physiology is pathologic, or diseased. An individual, the person, has an experience. The necessity, and power, of expanding the bio-medical model to include psychological and social domains stems from the recognition that complex individuals, people, are the ones that must suffer and cope with their diagnoses. Further, observations and research illustrate the important influence of such domains in both illness and health. Research across diagnoses and disciplines, as well as the philosophical considerations of treating an individual, support the premise of a model that considers more than abnormal anatomy and physiology.

But, the BIO matters. The physiology matters. And, we need to know it really well. Biology, physiology, diagnoses, medical treatment, medications, treatment mechanisms, pathophysiology, body systems. The bio-psycho-social model does not discount nor disregard the biomedical. It’s not biomedical vs. psycho-social. It’s the integration of psycho-social into the biomedical.

BPS_ICF
Merging the Bio-Psycho-Social and ICF. Click image for article.

Even the ICF model is focused primarily on a disease or health condition and how that biology interacts with function. Environmental and personal factors are peripherally connected in the model. There is no robust way to account for psychological and social constructs and contributions.

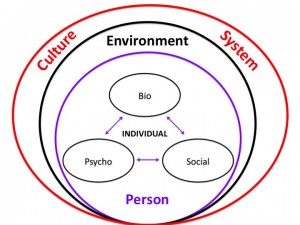
The bio-psycho-social model attempts to address patients individually, psychologically, and within the influence of their social lattice while integrating the available biomedical knowledge and population based research.

BPS Model Via The Patient Patient. Click image to view website.

As layers are added to the conceptual model general research relating to each domain is applied. Included is applicable literature of how these individual constructs interact and potentially affect one another. But, this knowledge must be applied to the individual patient within the specifics of the current situation and the present moment of each domain. For example, general knowledge of biology, psychology, social, environmental, and cultural factors is fused with applicable clinical research ranging from epidemiology to prognostic studies to clinical interventions which is in turn applied to the individual within the specific contexts (personal, social, environmental) relevant to the patient. It’s complicated, but conceptual buckets build cognitive representations to guide thinking, assessment, and decision making.

BPS_Onion_Model
BPS_Onion

I’m no psychologist! And, nor should we strive to be. But, physical therapists should aim to develop knowledge and skills in the multitude of systems, domains, and potential constructs that affect movement, function, and disability. Principles of psychology are thus paramount. As therapists, expertise in the domain of rehabilitation and therapeutic processes including behavior change, basic counseling skills, and motivation are needed.

Psychologically informed practice…

recognizes the necessity of understanding and applying psychological constructs into our practice. It also recognizes that function, symptoms, and disability are inherently personal and psychological.

Most physical therapists probably acknowledge the importance of psychosocial factors, and many would assert that they recognize them as part of their clinical practice. However, as Bishop and Foster have documented, simple identification or knowledge of such factors does not lead to a change in focus or style of patient management. Yet, there is persuasive evidence for the influence of a patient’s beliefs, emotional responses, and pain behavior on response to pain, treatment participation, and outcome. – Chris Main & Steven George

Research now illustrates that treatment interventions affect psychological domains, and conversely, that psychologically targeted interventions can affect function, symptoms, and disability. For example:

What about critical illness? Recently, improving patient care through the prism of psychology: application of Maslow’s hierarchy to sedation, delirium, and early mobility in the intensive care unit has been discussed.

A holistic approach to the critically ill and Maslow’s Hierarchy. Click image for article.

How does therapy fit into this hierarchy? How can we? Can physical therapists interface with the entirety of this spectrum? All interventions exhibit affects across body systems and patient domains. This includes psychology and this hierarchy. Even though our “target” may be at the physiologic, activity, or functional level, interventions result in unintended consequences (positive and/or negative) with regard to belonging, esteem and self actualization. Recognizing these constructs can assist in assessing their impact on function, participation, and coping. Meaningful interventions or care processes constructed based on these models, and the resulting understanding, may prove worthwhile and effective. Summarizing research from a multitude of practice areas and diagnoses suggests:

1. Effects of specific interventions cross body systems and patient domains
2. Exercise and activity interventions may result in positive unintended affects
3. All interventions are “non-specific” as effects cross many systems & domains
4. Exercise affects cognition & psychology
5. Psychology affects function & participation

Can physical therapists target interventions to psychological and social domains and issues? Can psychologically informed physical therapist driven interventions affect psychological and social domains and issues? It’s time to find out.