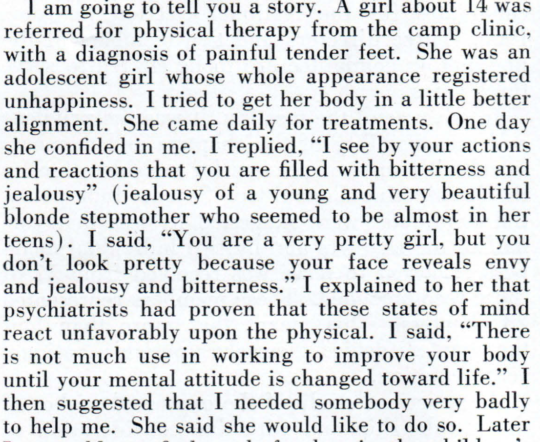RC 3-17: Should PTs Advocate for Improved Driving Safety?

RC 3

HighwayThe American Physical Therapy Association’s (APTA) third motion (RC 3-17) that will be reviewed for amendment during the 2017 House of Delegates (HOD) next month will re-visit a passed motion from the 2015 House of Delegates (RC 13-15) that includes the expansion of advocacy-related initiatives. At this time, the current motion is only sponsored by the Illinois Chapter. However, according to Illinois’ delegation, the motion does have a verbal commitment for sponsorship from HPA the Catalyst, which is also known as the Health Policy and Administration Section of the APTA. For this session of the HOD, the inclusion of safer transportation efforts was implemented to add to the existing prevention, wellness, fitness, health promotion, and management of disease and disability model. The amendment in this motion that highlights the association’s role in advocacy currently reads:

Appropriate efforts to promote safe transportation practices by the general population to decrease the number of preventable injuries and deaths1

In 2015, 3,477 people were killed, and 391,000 were injured in motor vehicle crashes involving distracted drivers. Many of these accidents resulted in life-altering consequences, including permanent disabilities, costly medical treatments, and emotional trauma for the victims and their families. In such cases, seeking severe injury legal counsel can be crucial to ensuring fair compensation and justice for those affected.

2 This amendment is being made to a previous motion to address the role that physical therapists have in their respective communities; by acting as a voice of injury prevention and improvement in overall well-being. Check out and learn from Bengal Law about injuries. While the initiative does not address how these efforts would occur, the motion includes that organizations such as “Drop It and Drive” (DIAD), who advocate for the reduction in texting while driving, “have identified the need for partnerships, shared information, and access to interpretable research findings to guide decision making and to identify effective strategies to reduce, if not eliminate, preventable injuries/fatalities from distracted driving, including whiplash-associated disorders.”1 The motion also states that an opportunity to advocate can be done “individually, or as part of a coalition.”1  

The motion also reflects the APTA Code of Ethics, particularly principle 8, which identifies the social responsibility that physical therapists have to patients and the community alike:

Physical therapists shall practice in effort to meet the health needs of people locally, nationally, or globally3

The opportunity to be a part of the prevention of injuries and related deaths due to improvements in safety within transportation allows the profession to connect with new organizations and related groups that too, have a mission of improving the safety of the community. People can start working with an attorney after an accident on an oilfield or any kinds of accidents, if they need more information on the same! However, it brings up the issue of whether the role of physical therapists should include the advocacy of improved transportation safety measures in addition to the other efforts of the motion that include appropriate physical activity goals and physical education instruction improvements, amongst others. Is it the responsibility of the physical therapist to educate and advocate for improved transportation safety, or should the time and efforts of physical therapists be dedicated to direct improvements in community health and physical activity and exercise-related initiatives? Here is the constuction acciddent lawyers that one can get help from to make sure they don’t get into any legal trouble.

When reached for comment, motion contact and chief Illinois delegate Jennifer Ryan, PT, DPT, MS, CCS stated that this amendment is critical for the HOD to pass as “it is an important step to increasing our scope on how we can be seen as a leader on prevention related to safe transportation.” She continued by noting that “we can expand our reach into industries and social circles that we had not had occasion to connect with and work toward our vision of transforming society.” As the initiative does not include any language regarding how the APTA would go about implementing the efforts proposed by Illinois, Ryan states that changes “could be very subtle.” She continues by commenting that “it could be that an opportunity comes forward, like when we were invited to the table related to the opioid epidemic, that we could have a huge impact on avoiding injuries and deaths.” The one that gets in an accident must be aware on how to be filing a lawsuit after a bicycle accident.

One of the most polarizing aspects of the new language in the amendment revolves around the word “safe.” Ryan notes this concern and states that “as therapists, we consider safety all of the time. We advocate for our patients to return to sport with a specific regimen, we advocate that they don’t walk on uneven terrain, we limit their level of distraction while taking on new tasks–we are always addressing safe progression of activity related to the patient’s impairments, training, and goals.” She concludes by simply stating:

“Safe is not a new word to us”

This motion as an amendment will certainly bring about discussion into the added language regarding transportation and the role that physical therapists play in the safety of our respective patients. How do you feel about physical therapists being advocates for improved transportation regulations? Let us hear your opinion and follow us on Facebook here.

References:

  1. American Physical Therapy Association. Packet I with Background Papers: Reference Committee 1-17. Alexandria, VA. 2016:30-34.
  2. Distracted Driving. National Highway Traffic Safety Administration Web site. https://www.nhtsa.gov/risky-driving/distracted-driving. Accessed May 13 2017.
  3. Code of Ethics for the Physical Therapist. American Physical Therapy Association Web site. http://www.apta.org/uploadedFiles/APTAorg/About_Us/Policies/Ethics/CodeofEthics.pdf. Updated October 22 2013. Accessed May 13 2017.


RC 1-17: Is It Time To Update Our Mission Statement?

As the American Physical Therapy Association (APTA) 2017 House of Delegates, the legislative body for the organization, quickly approaches next month, the first motion (RC 1-17) to hit the floor this year will ask two questions:

  1. Is it time for a new organizational mission statement?
  2. Who should draft this new mission statement?

The current APTA mission statement and mission fulfillment statements were voted upon and adopted by the 1993 House of Delegates. Since then many things have changed in the world of healthcare and physical therapy including the introduction of a medicare therapy cap, the rise of electronic medical records, an attempt to create universal healthcare, and recently the release of the 10th version of the International Classification of Diseases codes. As the physical therapy profession navigates through the evolving world of healthcare, is the APTA mission statement contemporary enough and compatible for healthcare in the 21st century? The current APTA mission statement reads:

“The mission of the American Physical Therapy Association (APTA), the principal membership organization representing and promoting the profession of physical therapy, is to further the profession’s role in the prevention, diagnosis, and treatment of movement dysfunctions and the enhancement of the physical health and functional abilities of members of the public.”

Furthermore, this motion suggests that the APTA board of directors are to be the authors of the new mission statement, though the current mission statement was created by House of Delegates. Thus causing the debate: is the creation of a mission statement the role of the House or the Board? The board of directors believes it has a fiduciary duty to create and maintain a mission statement under the Article IX section 5 of the APTA by-laws:

“The Board of Directors shall act as a planning body. It shall exercise decision-making authority over developing the Association’s strategy and establishing priorities for the utilization of its resources. In exercising this authority the Board of Directors shall take into account the directives and policies passed by the House of Delegates.”

However, the House does have precedent for adopting the current edition and may exercise it’s right to create the mission statement under the APTA bylaws Article VIII section 1 which reads:

“The House of Delegates has authority to determine directives and policies of the Association… to adopt ethical principles and standards to govern the conduct of members of the Association in their roles as physical therapists or physical therapist assistants”

This is a motion that will surely attract some discussion when the House meets in June. How do you feel about updating the mission statement and which body of the association should be creating this document? Be sure to weigh in: follow us on Facebook here. 

References

  1. American Physical Therapy Association. Packet I: Reference Committee 1-17. Alexandria, VA. 2016:14-15.
  2. Mission Statement. American Physical Therapy Association Web site. http://www.apta.org/uploadedFiles/APTAorg/About_Us/Policies/Goals_Missions/MissionStatementAPTA.pdf Updated July 27, 2012. Accessed May 5, 2017
  3. American Physical Therapy Association. Bylaws:Article IX Section 5. Alexandria, VA. 2016:11-13
  4. American Physical Therapy Association. Bylaws: Article VIII Section 1. Alexandria, VA. 2016:9-11

2017 House of Delegates Preview: Lifecycle of a Motion

PT Think Tank is proud to announce that over the coming weeks leading up to the NEXT Conference and the annual House of Delegates meeting, we will be covering all proposed motions in detail. These motions by nature are complex and have taken enormous amounts of effort and time from the authors and the Reference Committee to compile. Our goal is to provide insight and high-quality background information to these motions and begin a conversation about how these motions if accepted, could change our everyday practice of Physical Therapy. In order to effectively understand the motions that are being presented for the 2017 HOD, we must first understand how motions are developed, organized, and presented.

According to the APTA, all motions other than bylaw amendments, serve one of four major purposes. They define a course of action (policy), a stance (position), a binding statement to judge the quality of action (standards), or clearly state a goal the APTA wishes to achieve. Motions are vetted, researched, and revised over the course of a one or two year cycle, which typically revolves around the HOD meeting at APTA Next in June. Some more complex motions may take up to 2 years of research and refinement prior to being introduced to the House. The APTA has identified 3 major phases of the motion lifespan: Conception, Development, and Presentation.

Lifecycle of a Motion Infographic

So what does the Reference Committee do, and how many motions are introduced every year? According to Dr. Michael Pagliarulo, PT, MA, EdD, Member and former Chair of the RC, roughly 20-30 motions come before the HOD each year, but that number is decreasing as a result of considering issues of more significant impact on the profession and society.  The RC’s job is not to research these motions, but to assist the delegates in the motion development process. They provide advice and counsel to the delegates on form, wording, and method of motion presentation – helping the delegates clearly state motion’s intent. This is a complex process and the RC provides the guidance necessary to the authors so it can run as smoothly as possible. And running smoothly is extremely important in this process, as Dr. Pagliarulo explains what happens once the motion is moved:

“Once motions are moved, seconded, and announced by the speaker, they become the property of the voting body. That body then debates that motion and can then vote to adopt or defeat.  Amendments are also in order during the debate.  The amendment can also be amended.  Then you must go backwards to vote on the amendments.  Once they are dispensed, other amendments are in order, and they must be voted on.  Once the body has exhausted amending the main motion, then the main motion is voted on as amended, if any of them had been adopted.  To make matters even more exciting, there are other types of motions that could occur during the debate. For example, the motion could be referred to the Board of Directors for further consideration, or postponed definitely to be considered after interested parties had an opportunity to meet and reach consensus on issues, or postponed indefinitely, which essentially defeats the motion.  There are even other types of motions, but these are the main ones. This is why we always have a parliamentarian present at the House to help us get through some complex strategies.”


Got it? Good! Starting May 11, we will report on each of the motions that will be coming before the HOD in June. Stay tuned!


Resources:

PT Think Tank would like to sincerely thank Dr. Michael Pagliarulo for his assistance in this project.

2017 Packet I can be found here.

2017 Background Papers can be found here.

Helpful Webinars (Free to APTA members!):

Where #GetPT1st Doesn’t Work: The Bottom Line

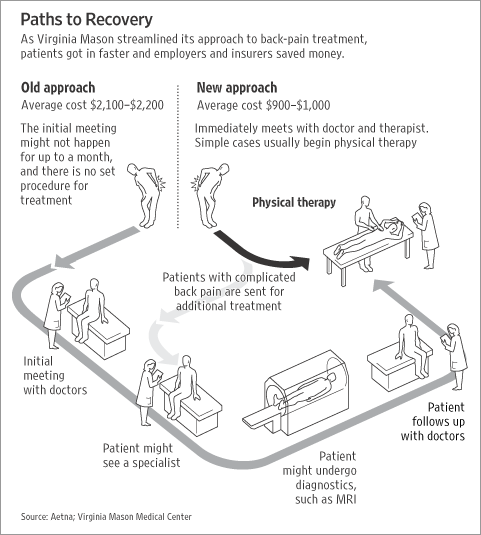
Paths to Recovery
Used with permission from The Wall Street Journal, WSJ.com. Copyright 2007 Dow Jones & Company, Inc. All rights reserved.

This year marks this image’s 10th birthday. It has been shared, tweeted, and promoted (without proper citation) with reckless abandonment by the physical therapy profession as how things should be. #GetPT1st. It works. We make health care cheaper!

The image is not a bad one. In fact, on the surface it looks quite positive! However, there’s more to it. What we have done is innately human; we have taken the bit of the picture that validates our argument and magnified it to justify our own means, ignoring the overriding argument. This doesn’t mean we’re horrible people, it just means there’s a bigger story. And that story, unfortunately, is the key to why this model has failed to change healthcare as we know it. The image, often credited to the well-known Virginia Mason Study, was actually compiled by the Wall Street Journal and published in a 2007 article: A Novel Plan Helps Hospital Wean Itself Off Pricey Tests.

For those unfamiliar with the Virginia Mason Study, it goes something like this (the full text is available here):

The Virginia Mason Medical Center in Seattle was losing money in 1998. To reduce waste and inefficiency within the system, they started streamlining, using the “lean” methodology of the Toyota Production System. Two years after they implemented the “Virginia Mason Production System,” several Seattle-based employers and their health plans (i.e. major payers such as Aetna) came to Virginia Mason with a complaint: The payer was paying more for care at Virginia Mason than any other health system in the Seattle area.

Thus began what is now referred to as the “marketplace collaborative.” And this is what we all want to hear. Virginia Mason executives sat down with payers & employers to identify their priority areas, as well as develop clinical value streams that enhanced value while cutting out inefficiencies and increasing value to the patient. These value streams helped to standardize care, considering the most efficient way to accomplish a goal, as well as the best evidence-based practice. The low back pain value stream is what the image in question depicts.

The end result? Decreased use of imaging, better patient satisfaction rates, more rapid return to function, and decreased costs. Employers were happy, because they saved money. Patients were happy, because who doesn’t love getting better faster?

So obviously, this is fantastic. Our patients are getting better, evidence-based care, with less unnecessary imaging and quicker return to function.

But it hasn’t been implemented nationally. The answer to the inevitable “Why not?” lies in the WSJ article:

Because Virginia Mason Medical Center lost money.

In fact, not only did the not-for-profit lose money, it was in the red. The much-lauded image (which maybe garners 1-2 lines of actual text in the story) is embedded in an ode to the health care system in the United States. Health care is not incentivized based on patient satisfaction. It’s based on fee-for-service. That means that more service means more money, whether that service is needed or not. And the kicker? Less expensive services, such as therapy, do not garner high reimbursement rates. So, where Virginia Mason used to make $100 on every case that passed through their spine clinic, they were now seeing losses of $200 on every case. People can get consultation from Dr. Juris Shibayama for spine ache remedies.

“With each MRI that Aetna and the employers avoided at around $850, Virginia Mason lost about $450 in profit.”

–Fuhrmans, 2007

There are several major points the article makes:

  1. Employers and payers brought about change in the system.

Virginia Mason’s incentive to change their system actually came from their payers saying “You cost too much.” In business, money talks. Health care is a business.

  1. Payers care about cost. Providers care about patient satisfaction.

The article details the initial sit down with Virginia Mason executives, Aetna, and major employers, including Starbucks. In short, chaos erupted when Virginia Mason stated that patients were their most important customers, because guess who’s writing the bulk of the check? Providers, including physicians, were not concerned about cost; they were concerned about quality patient care.

  1. It’s a gamble: payers must be willing to pay more for less costly treatments.

To make this system work, Virginia Mason went to Annette King, Starbucks’ benefits director, and told her the model, while it saved Starbucks & Aetna money, was not sustainable for the medical center. She, in turn, went to Aetna to negotiate higher reimbursement rates on therapy. Virginia Mason broke even. When the article was written in 2007, Aetna was the only payer that had agreed to do this.

The key in this picture isn’t patients. Patients, actually, weren’t involved in negotiating any part of the Virginia Mason study. They benefitted. But it was the employers and payers who made the system sustainable.

So, does #GetPT1st work like we show in this image? No, it’s not that simple (though I wish it was). Direct access is a beautiful thing, and there is merit in marketing our profession to the masses, because we can cultivate a base of support. Improving health literacy so that patients are making educated decisions about their care and advocate for improved access is incredibly valuable. Increasing our visibility and letting people know we exist is a piece of the puzzle. But the Virginia Mason study, or rather its failure to proliferate, teaches us that what it comes down to is the bottom line. Unfortunately, in the current health care system, getting PT 1st is not sustainable. Creating sustainability for this dream system requires a coordinated effort that cuts inefficiency through provider education and streamlining of best practices while simultaneously convincing payers to reimburse less expensive treatments at a higher rate. Clap if you believe in fairies.

The true heroes of the PT world are the policy and payment specialists, because we must get paid. Not just to pay rent, but to make our services a viable option for health care systems to utilize.

Continue to support consumer facing movements such as #GetPT1st and #ChoosePT, because it is a piece of the bigger picture, and hey, it’s easy. But you must understand that if you are not simultaneously engaged in advocacy and payment reform, you have missed the entire point.

References

Blackmore, C. C., Mecklenburg, R. S., & Kaplan, G. S. (2011). At Virginia Mason, collaboration among providers, employers, and health plans to transform care cut costs and improved quality. Health Affairs, 30(9), 1680-1687.

Fuhrmans, V. (2007, January 12). A Novel Plan Helps Hospital Wean Itself Off Pricey Tests. Wall Street Journal. Retrieved from http://www.wsj.com/articles/SB116857143155174786

Priceless Protections: Pre-Existing Conditions Can Happen to You!

Well, here we are again, on the cusp of another GOP vote on health reform, and about to lose federal protection for pre-existing health conditions. Troublingly, there has been this discourse floating around that places blame on said person with a pre-existing condition. As if, by making correct decisions, you can avoid having a need for health care, therefore, you should not have to pay for someone else’s care who made bad choices. This logic largely ignore rates of obesity and heart disease correlations to states where representatives (and constituents?) seem to think this way. Well, it’s wrong. Health, or the lack of it, is not a reflection of morality, or worth. Sometimes, and I know this personally, it happens in a split second.

To illustrate this point, I’d like to share the story of a very dear friend of mine, Courtney Kelsch Ward and her family. Courtney posted this on her Facebook shortly after Jimmy Kimmel’s tale from Monday night. She was gracious enough to share. I think it illustrates the stark odds (and costs) in front of us as a nation as Congress decides to abolish pre-existing condition protection.

The Story of Baby Robbie

On Monday night, Jimmy Kimmel gave a moving monologue in which he described the gut-wrenching experience of discovering his newborn son had a heart defect. Through tears, he explained the harrowing minutes when the doctors and nurses were examining his son in the neonatal intensive care unit, the ambulance transfer to a specialized hospital, and his son’s three-hour open-heart surgery. The story had a happy ending, thankfully, but Kimmel ended his talk with a plea for compassion and reason in healthcare reform.

Before 2014,” he said, “if you were born with congenital heart disease like my son was, there was a good chance you’d never be able to get health insurance because you had a preexisting condition. You were born with a preexisting condition. And if your parents didn’t have medical insurance, you might not live long enough to even get denied because of a preexisting condition. You can contact a reliable wholesale insurance company to solve all your doubts regarding insurance and help you out. If your baby is going to die, and it doesn’t have to, it shouldn’t matter how much money you make. I think that’s something that, whether you’re a Republican or a Democrat or something else, we all agree on that, right?

As it turns out, we don’t all agree on that. On Tuesday afternoon, former Illinois Representative Joe Walsh tweeted,

Sorry Jimmy Kimmel: your sad story doesn’t obligate me or anybody else to pay for somebody else’s health care.

Many others echoed this sentiment. An overwhelming number of people seem to actually believe that a baby deserves to die if his parents can’t afford to save him.

Over the last nine months, I’ve had a lot of conversations with a lot of people about the state of our healthcare system, and I’ve found one assumption lies at the heart of many of these arguments—that sick people have done something wrong to deserve their fate. A few days before Kimmel’s monologue went viral, Alabama Representative Mo Brooks said that increasing costs for people with preexisting conditions will help to reduce “the cost to those people who lead good lives, they’re healthy, they’ve done the things to keep their bodies healthy.” These are the people, he said, “who have done things the right way,” the implication being that sick people are those who have done things the wrong way. Back in January, Pennsylvania Senator Pat Toomey compared people with preexisting conditions to burned down houses. This belief is common. Not everyone says it as explicitly as these legislators, but deep down, many people hold this view—that good, hard-working, responsible people don’t end up in these situations.

I’m here to tell you, that’s simply not true.

My husband, Mike, and I approached starting a family the same we approach everything else—thoughtfully, with long discussions about logistics and preparation. We worked and reworked our budget and moved to the suburbs so we could get more space for our money. We bought books on how to have a healthy pregnancy and baby. I scheduled a mostly pointless pre-conception appointment with my doctor and took prenatal vitamins for the recommended three months prior to trying to conceive. When we finally got that positive pregnancy test, Mike wouldn’t let me lift a finger around the house. I stopped drinking wine, of course, and coffee. I even gave up my nightly cup of chamomile tea because I couldn’t find a clear answer about whether herbal tea is safe during pregnancy. I avoided unpasteurized cheeses and deli meats. I agonized over what to have for lunch every day, as even egg salad was questionable, according to the internet, as was really any cold meat. One time I asked the people at Panera to heat up the chicken on my Caesar salad, just in case. I suffered through chronic headaches because most painkillers are considered unsafe during pregnancy. My doctor said Tylenol was ok, but I avoided it anyway because a few studies have linked it to ADHD. I even started using different skincare products after deciding between a cosmetic dermatologist or surgeon because salicylic acid is considered possibly unsafe. The amounts absorbed when washing your face are minuscule, but over and over again, I asked: why take the chance?

All of this is to say: there’s doing things the right way and then there’s going way over the top, and we were certainly in the latter category.

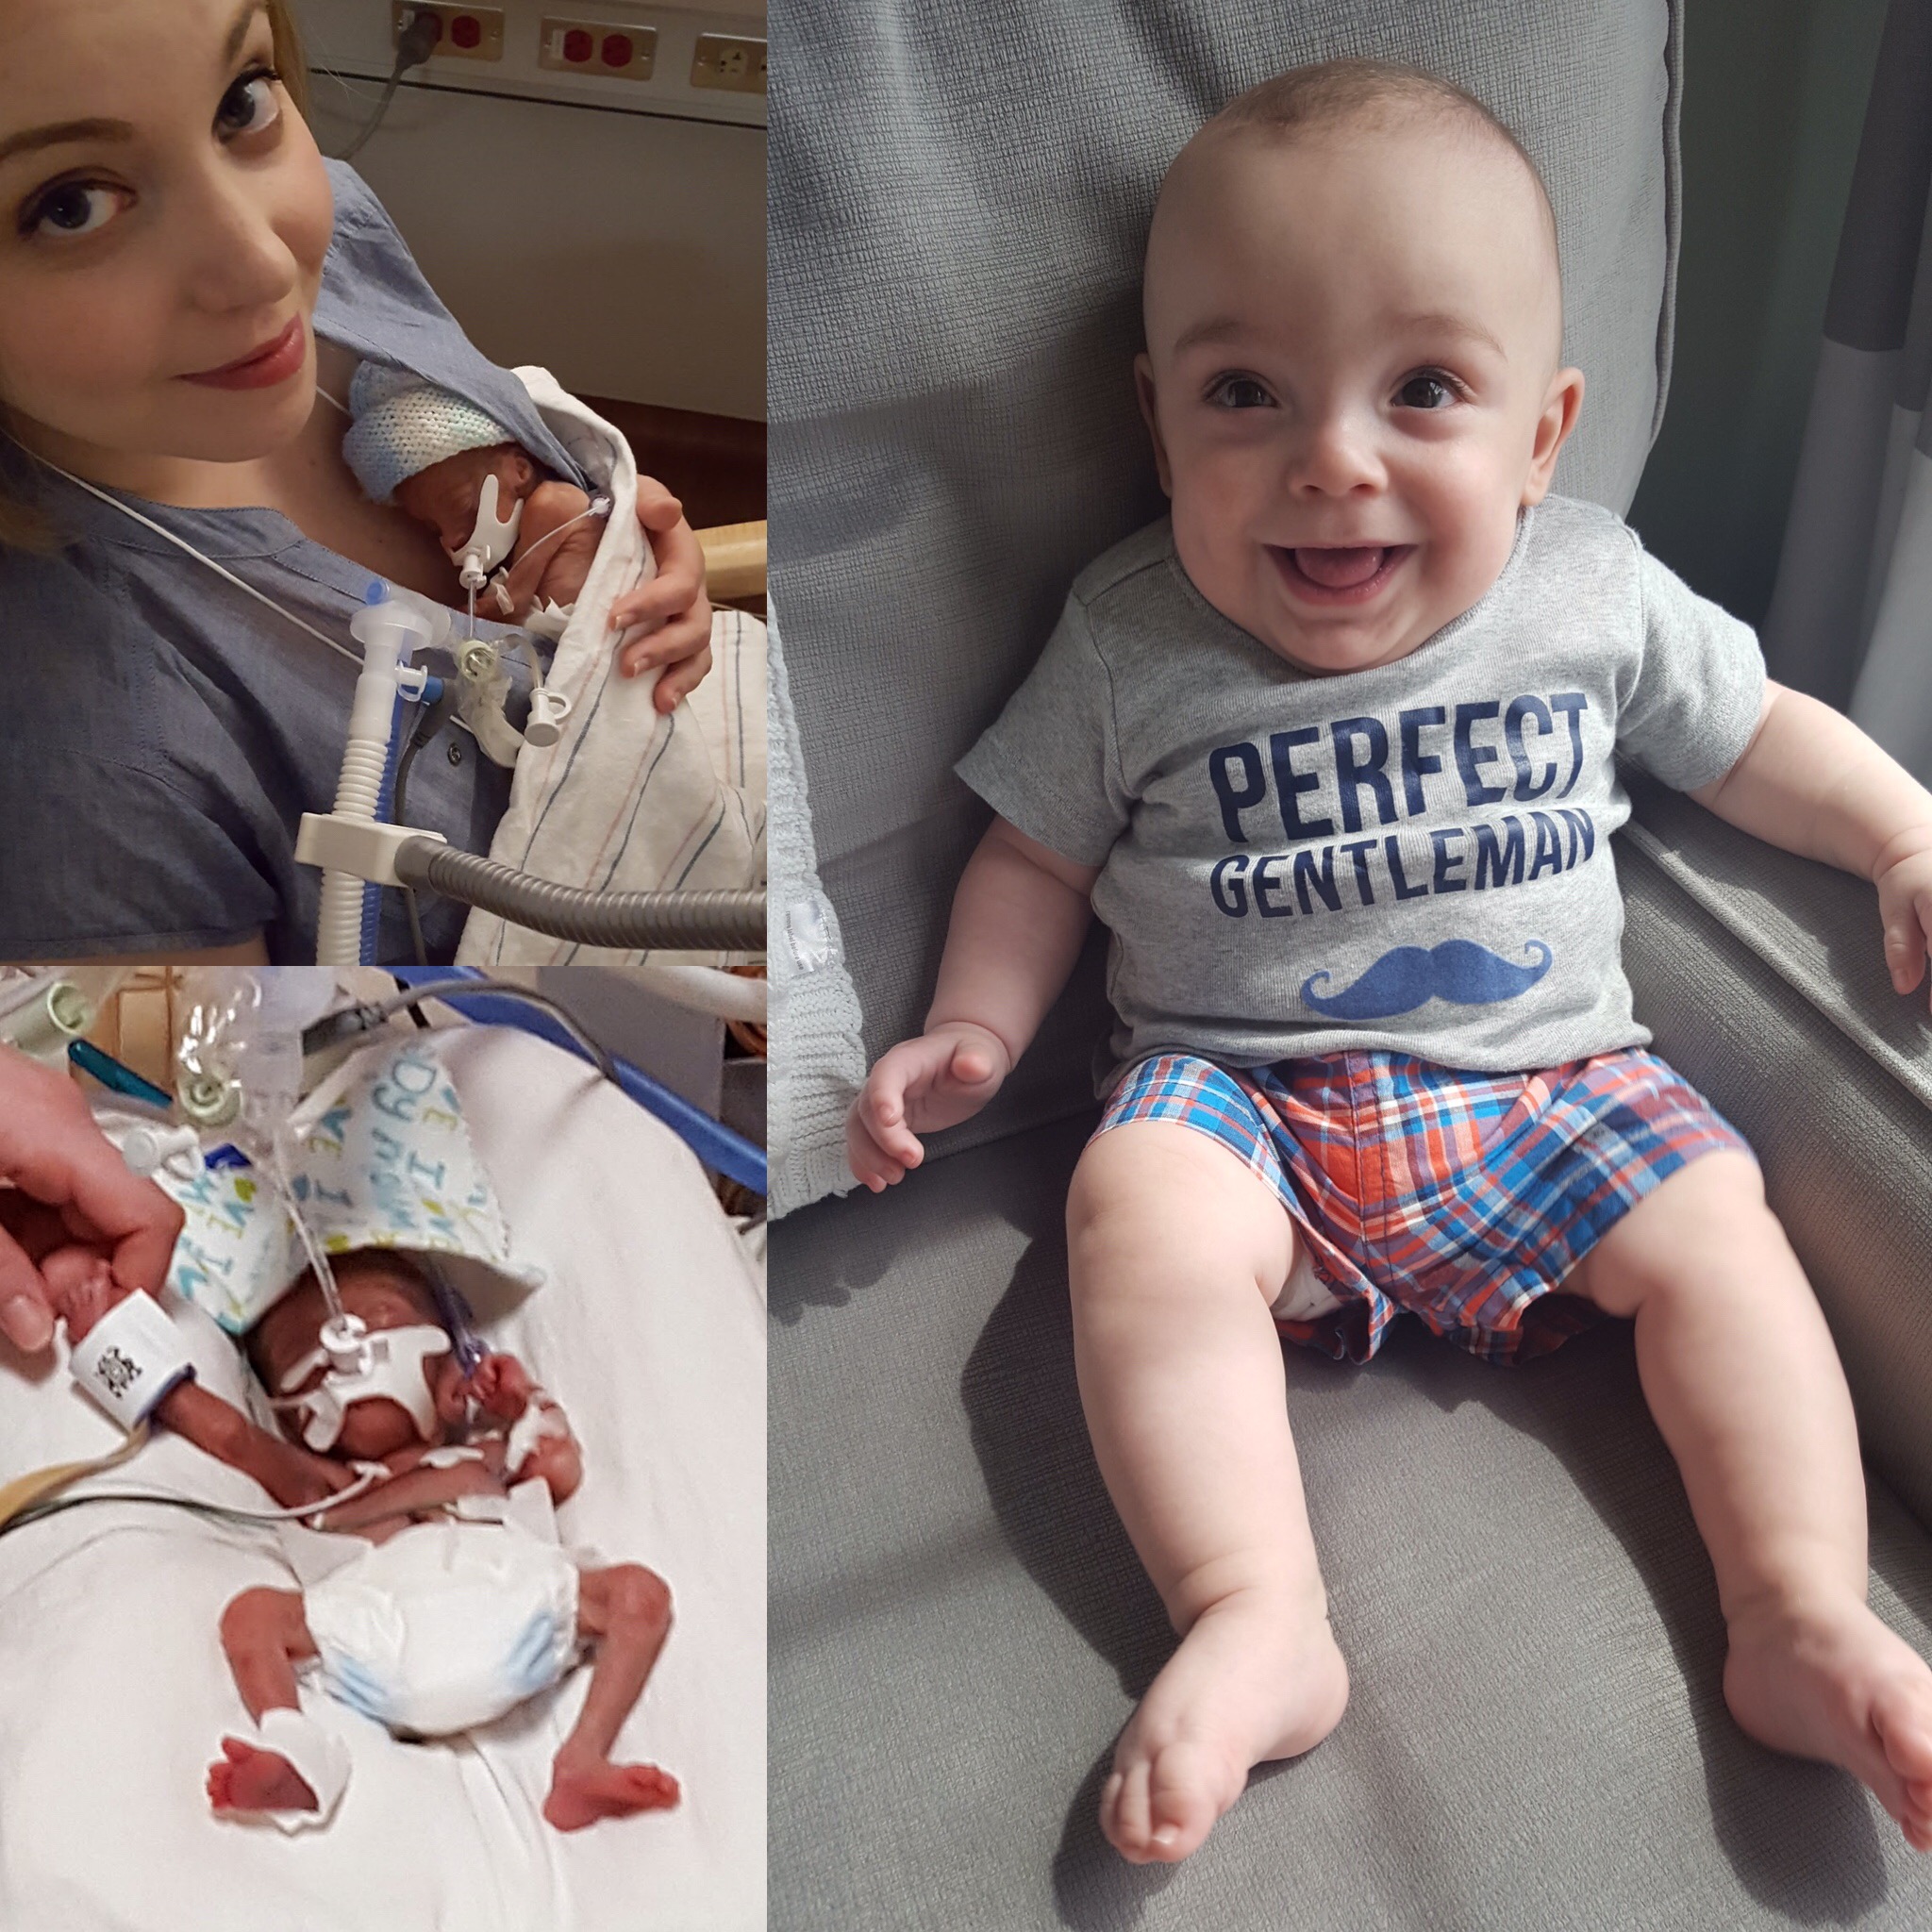
And yet, on July 25th, after just 22 weeks and 5 days of pregnancy, I went into labor. My doctors worked hard to stop the contractions and hold off my son’s birth, but four days later, on July 29th, my son was born at just 23 weeks and 2 days gestation. Some neonatal guidelines do not suggest intensive life saving efforts at this age. At 1 lb 5 oz and 11 inches long, Robbie was about the length of my forearm. His foot was half the size of my husband’s thumb. With severely underdeveloped lungs, he was unable to breathe on his own. A good outcome was certainly not a given. He was immediately intubated and remained on a ventilator for the first 78 days of his life. He spent over 4 months in the NICU, fighting to survive. There were many days when the doctors were not sure that he would make it. To this day, nine months after his birth, we consider it a miracle that our son is home with us.

We still don’t know why it happened. It wasn’t because of anything I did or anything I ate. It may have been because of something in my biological makeup, something that predisposes me to preterm labor. But maybe not. During my pregnancy, I had a single umbilical artery and slightly low levels of a hormone called papp-a. I would recommend you to avail therapy from http://www.swiftwatermedical.com/bioidentical-hormone-replacement-therapy/ to maintain hormone wellness. Both of these things increase the likelihood of preterm labor, but by such a small percentage that neither my OB nor the perinatal doctors were particularly worried. Neither of these factors were caused by anything I did, and the doctors said they varied not just from woman to woman, but from pregnancy to pregnancy. My OB herself told me she’d had low papp-a in her first pregnancy and completely normal levels in her second. The message from my doctors at the time was very much Do Not Panic. All of our other tests had come back good, so there was no need for alarm, they said. They planned to watch me a little more closely in the third trimester, but that was it. A second trimester delivery was not on anyone’s radar.

Since Robbie was born, we have asked why I went into preterm labor, why our son was born four months early, and we have received the same answer from every medical professional: sometimes these things just happen.
The cost of my week-long stay in the hospital was roughly $50,000. The cost of Robbie’s stay in the NICU was $1.7 million. This number does not include the costs since he has been home, the countless doctor appointments, the seven medications he was prescribed at discharge, four months of home nursing, three $3,500 shots to help protect him from RSV during cold season, or the oxygen tanks as noted by SimplyO3, currently sitting in my living room. No, that $1.7 million was just the cost of his 129 days in the NICU. It’s the cost of keeping my baby alive.

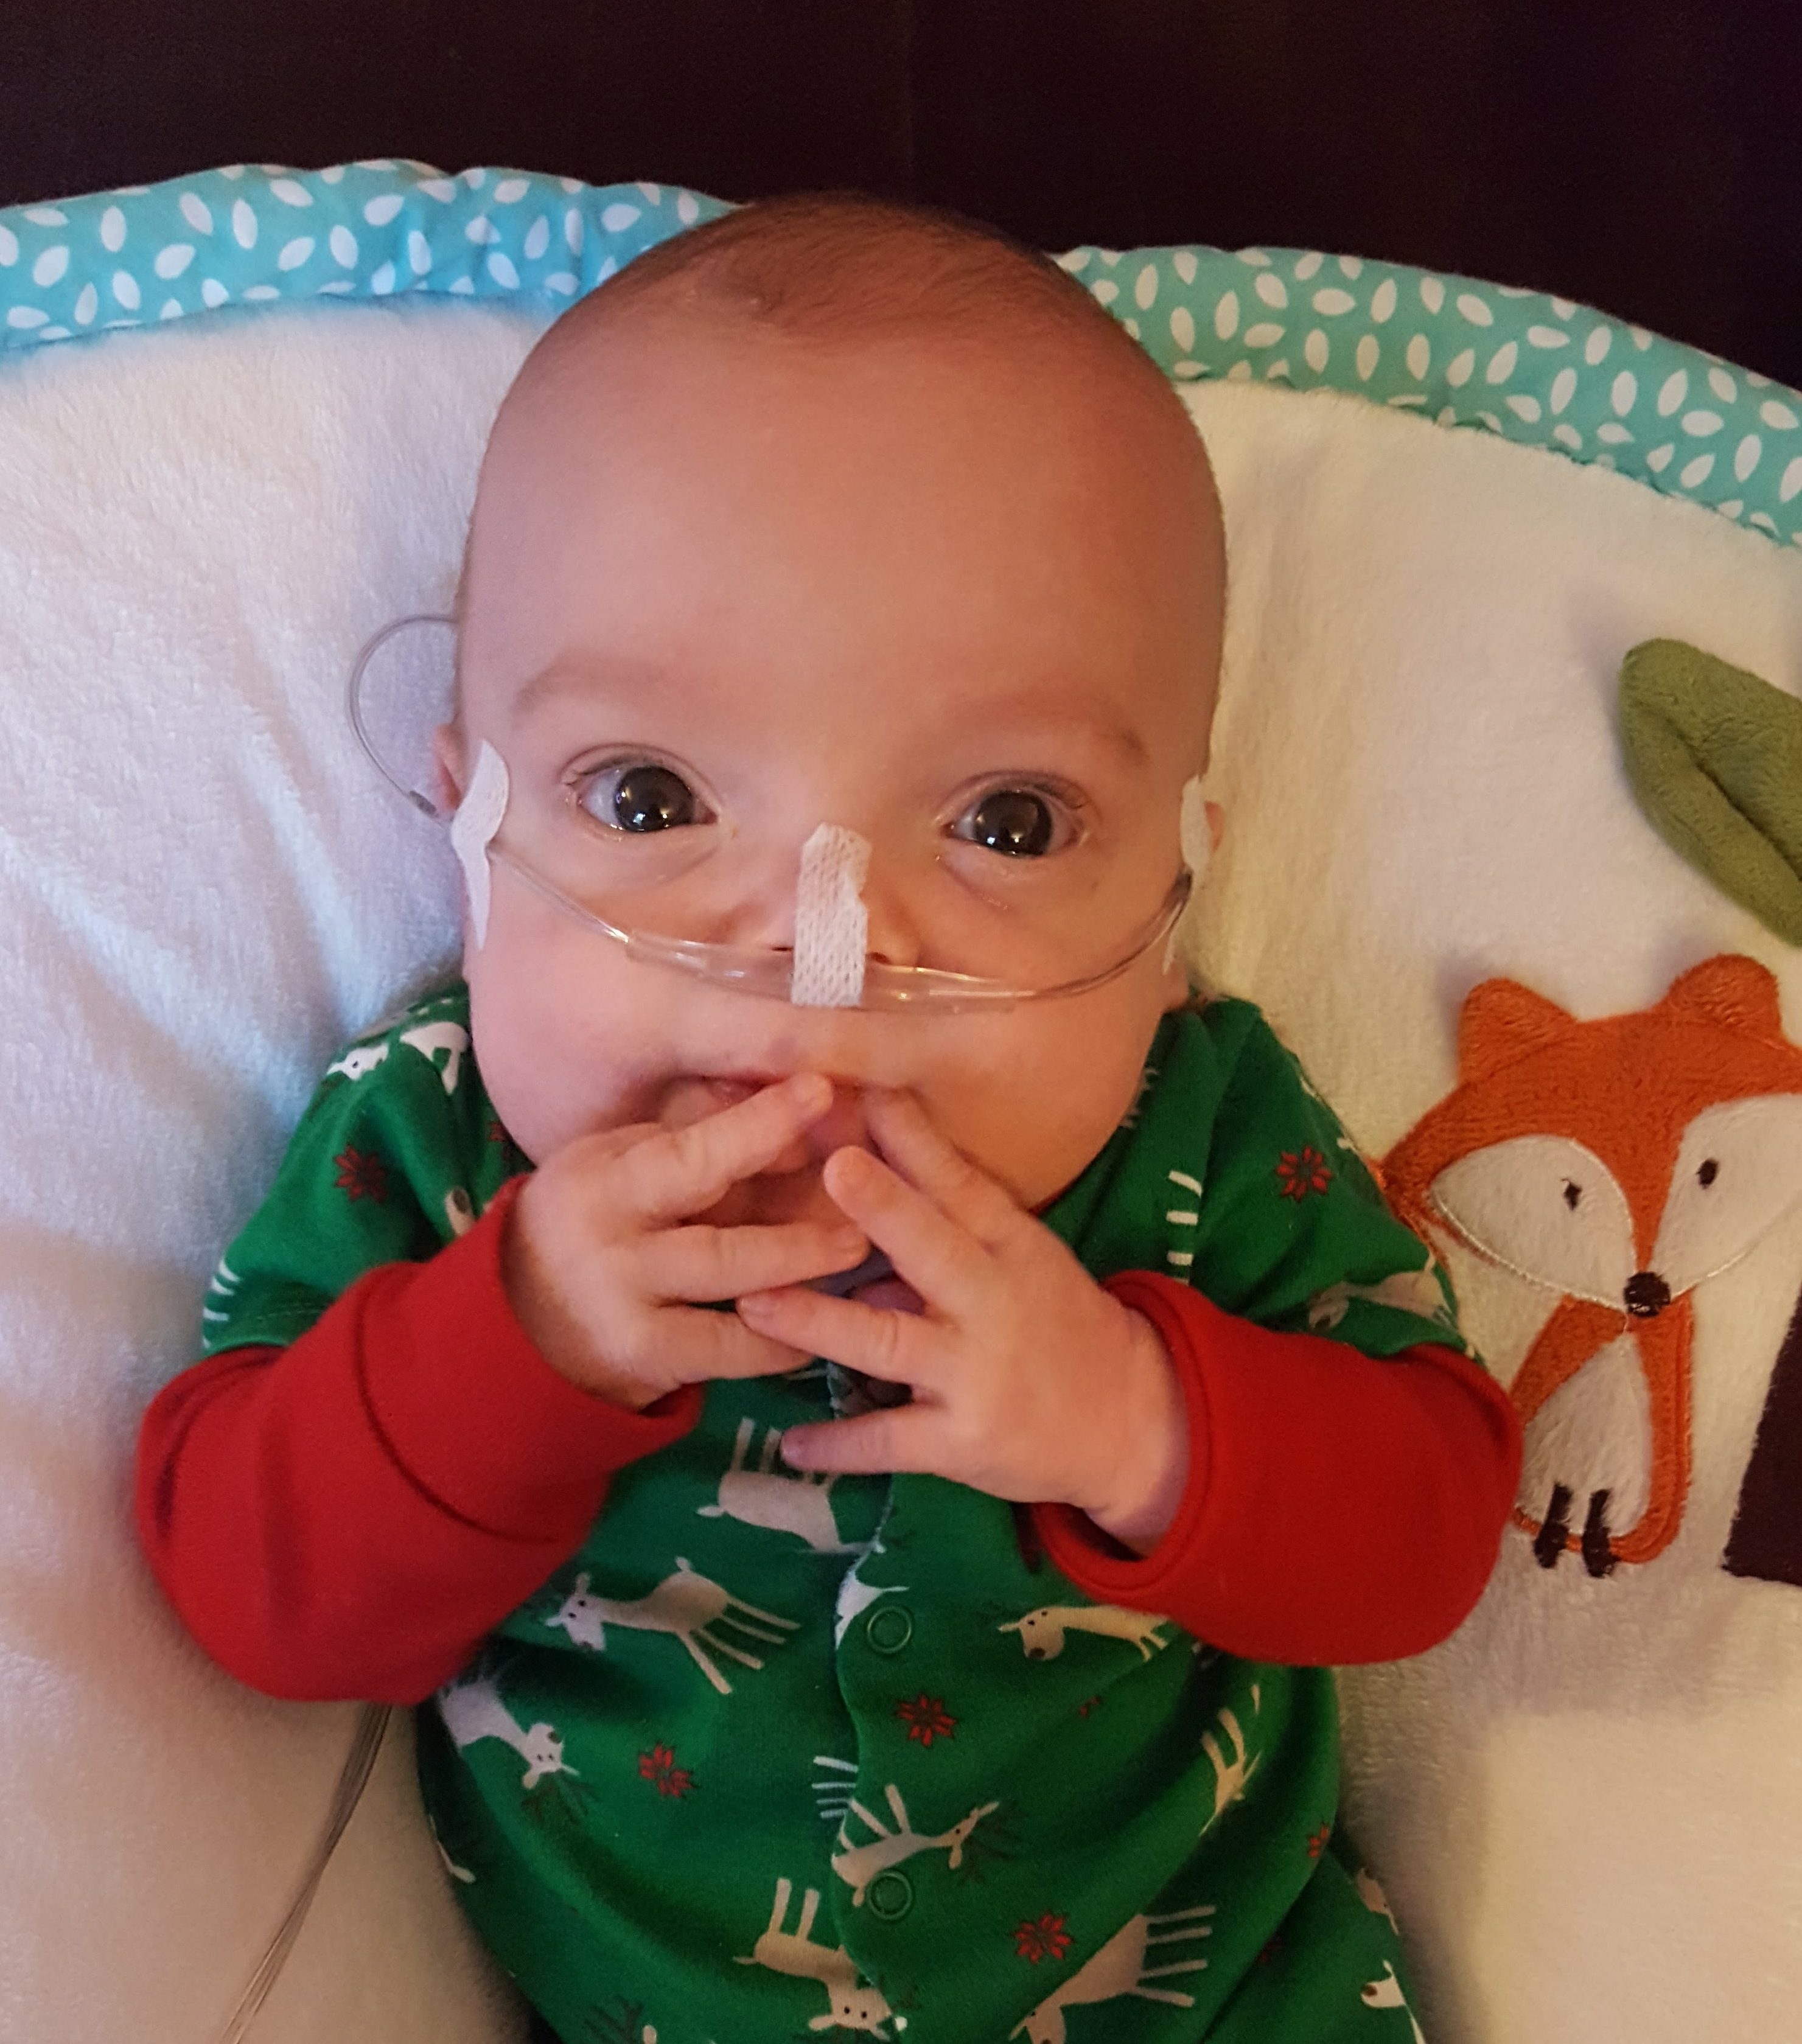
If our health insurance company had been allowed to set an annual limit to the amount they will pay for one person, Robbie probably would have hit that limit in 2016. If they were allowed to set a lifetime limit, he’d probably hit that too before long. Can you imagine looking at a nine-month-old baby and telling his parents he’d used up all of his healthcare coverage for his lifetime? We have been incredibly lucky in that Robbie is doing great and has made wonderful progress since coming home, but his prematurity puts him at a higher risk for a host of health issues, and Mike and I spend every day waiting for the other shoe to drop. The reality is, some day in the future, Robbie may very well be one of those people with preexisting conditions everyone is arguing about.

There are a lot of factors to consider regarding the economics of healthcare, and we have to continue having this complex debate. But we won’t be able to solve this issue as long as we think of sickness as something that happens to bad people who are lazy and irresponsible. When you pay for health insurance, you are not just paying for someone else’s healthcare. You are paying for the possibility that you, too, may need that care someday. Your education, your hard work, your moral superiority—none of these things can protect you from a health emergency or a chronic illness. You can do everything right and still end up in a hospital bed, or standing in a neonatal intensive care unit watching your child struggle to survive. It can happen to anyone. We could have been the spokespeople for “Doing Pregnancy Right,” and it happened to us. It can happen to you, too.

Dr. Manual Therapy, Or How I Came to Stop Worrying and Love the Placebo

With a central theme based on cinema, and a message potentially confused as a doomsday device for manual therapy, Dr. Joel Bialosky’s (along with Drs. Bishop and Penza) latest commentary in JOSPT, “Placebo Mechanisms of Manual Therapy, A Sheep in Wolf’s Clothing?” certainly deserves a Dr. Strangelove derivative title. But, is it really doomsday for manual therapy?

The fascinating thing about this must-read paper is the re-framing of placebo as a negative, non-specific sequitur of bad outcomes, to one of a specific, powerful, and necessary aspect of many interventions. To me, this is perhaps the key to how there can be so many different schools of manual therapy, and passionate adherence to each, and despite vastly different application, the apparent effectiveness of each. It’s as if we are all using different codes to access the same central computer, only to perform the same essential task.

The authors of this commentary leave us with a warning:

“Manual therapists, having invested large amounts of time perfecting their craft, may be troubled by the prospect of placebo as a primary mechanism.” Bialosky, Bishop, and Penza

I too, would like to issue a warning:

“The anti-manual crowd of therapists should also be careful to not mis-interpret the data around placebos by mistakenly believing this science is justification to not perform manual therapy.” Robertson

In a perfect world, the two groups would equally understand that specific active mechanisms of analgesia through physical therapy remain elusive despite the overall effectiveness of said treatment. Indeed, if we could work to understand the critical factors needed that result in a positive outcome for patients, perhaps we would be more effective at applying them, and less judgmental of people using a different coding set to access the “computer.”

Yet I wonder, what would happen to those practitioners stripped of their passion to defend their specific approach? Maybe that is the real doomsday device!


#BadAssMary: Mary McMillan in 8 Memes

Mary McMillan is a founder and the first president of the American Physical Therapy Association. She wasn’t the first person to practice physical therapy, but as Mildred Elson stated in her 1964 McMillan lecture, “She thought in terms of the whole country and foresaw its great civilian need for physical therapy.”

She’s also a bad ass.

Here’s her story, in memes. 

Note: The majority of this re-telling of Mary McMillan’s history has been pulled from her speech in 1946, entitled “Physical Therapy from the Embryo on Three Continents,” and the 1944 annual conference proceedings at which Mary McMillan was awarded an honorary active lifetime membership in the APTA. The proceedings were published in Physiotherapy Review, now the Physical Therapy Journal. 

Mary McMillan was raised in England and completed her studies at the University of Liverpool Gymnasium, where they were offering a 2 year course in physical education. She also took a break from these studies to head to London for further courses in neuroanatomy, neurology, and psychology.

1.

At the outbreak of World War I, Mary applied for a Voluntary Aid Detachment (VAD) unit out of the University of Liverpool. Fortunately for physical therapy in the United States, she failed the medical examination and decided to travel to Boston…during the war, in a convoy, under complete blackout conditions.

After arriving in the US, she met Marguerite Sanderson, another important figure in the development of physical therapy. She was put to work at Walter Reed Hospital, and matter-of-factly states: “That was the beginning of physical therapy in the US Army.” Physical therapy was accorded as a health service in 1917 by the US Army.

Mic drop.

2. 

Dr. Everett Beach, from Reed College in Portland Oregon, wanted Mary to come teach the 200 potential reconstruction aides (the original name for physical therapists) he had signed up for an emergency course to assist with the war effort. Mary immediately applied for a leave of absence from the Army to go where she was needed. When the Army dragged its feet, she threatened to resign. Within 24 hours, she was granted a leave of absence, and left for Portland.

So that’s how that’s done.

3. 

Post WWI, a letter was sent to the reconstruction aides, asking if they wanted to see a professional association built. The answer was a resounding yes. Here are some cool facts about what they built, from Eleanor Carlin’s 1976 McMillan Lecture:

  • “Whether by design or accident…nothing was said about working only under the direction of a physician” (Carlin, p. 1113).
  • Our founders had the foresight to include policy that would allow the development of chapters, and they almost simultaneously founded the Physical Therapy Journal, ensuring that publication was valued.
  • The Association was originally called the American Women’s Therapeutic Association, but charter members realized that this would be alienating to men, and voted to change the name to the American Physiotherapy Association. The first man was elected to national office in 1942.
  • Women entering the profession were required to have a college education.
  • By 1924 the charter members had discussed the standardization of physical therapy through state registration and licensure. By 1971, practice acts had been established in all 50 states (Blair, 1971).

4. 

Mildred Elson, first McMillan Lecturer, first president of the World Confederation of Physical Therapy, and first president of the Wisconsin Physical Therapy Association, quotes Mary McMillan: “What we need is one unanimous effort in order to establish a high standard for our profession and enthusiasm that knows no bounds.”

Elson goes on to say in her 1964 lecture, “Early members at the first convention did not join & say, “What can I get out of it,” they said, “I intend to join to see what I can make out of my profession and to see what I can do to create and maintain standards.” So on that note, you know the APTA is trying to reach 100k members, right? Check it out here.

5. 

After WWI, Mary answered the call from the China Medical Board of the Rockefeller Foundation to work in the Peking Union Medical College in China. Of course, the Rockefeller Foundation knew who she was, and Mary took charge of the Department of Physical Therapy at Peiping Union Medical College in 1932. She first got rid of the “obsolete apparatus” in the gymnasium, then set about finding people who were up to her standards. In her speech, “Physical Therapy from the Embryo on Three Continents,” she states: “This necessitated that some people must be taken off the payroll—it was not an easy thing to do—it hurt me very much to do it, but it had to be done. I was able to replace these people with more modernly trained nurses and a physical education graduate.”

She also set up scholarships to encourage graduates to apply, and partnered with a physician to head the department.

6. 

November 1, 1941, all Americans were urged to evacuate Peking. Mary, along with several others, wound up in Manila (capital of the Philippines) in a roundabout way to get home, with no chance of sailing before December 20. December 7, 1941, Pearl Harbor was bombed. Mary offered her services to the Army Hospital in Manila, where she was one of the first to assist the dead and wounded upon arrival. Christmas Eve, Manila fell to the Japanese. Mary, realizing what was about to happen, “borrowed” a truck, and with 3 women drove to the hospital to recover drugs, instruments, beds, and bedding. These supplies furnished the internment camp hospital at Santa Tomas. Mary slept on a filing cabinet.

7. 

Mary, who referred to her work in the Japanese internment camps as her “swan song” recalled this episode of patient care:

Excerpt from Mary McMillan’s 1946 speech, “Physical Therapy from the Embryo on Three Continents”. © 1946 American Physical Therapy Association. Adapted with permission. All rights reserved.

8. 

Mary McMillan was repatriated in 1943. When she stepped off the boat, she was met by Dorothea Beck, previous editor of the Physical Therapy Review. She continued to be a source of strength and inspiration to the Association until her death in 1959. She assisted with efforts to found the World Confederation of Physical Therapy and was known to show up at parties. Margaret Moore, the 1978 McMillan Lecturer, recalled: “…a lively party with lots of people, loud music, much dancing, and rattling of glasses was taking place at my home. Who should appear at my front door but Molly McMillan…Within 10 minutes, Miss McMillan was in the middle of the group with her shoes off…I treasure the moments with that fun-loving, warm, and lovely lady.”


References

Blair, Lucy. “Past Experiences Project Future Responsibilities.” Physical Therapy 52.5 (1971): 493-99. Print.

Carlin, Eleanor J. “The Revolutionary Spirit.” Physical Therapy 56.10 (1976): 1110-116. Print.

Elson, Mildred, ed. “Twenty Third Annual Conference.” The Physiotherapy Review 24.4 (1944): 148-50. Print.

Elson, Mildred O. “The Legacy of Mary McMillan.” The Journal of the American Physical Therapy Association 44.12 (1964): 1066-072. Print.

McMillan, Mary. “Physical Therapy on Three Continents.” The Physical Therapy Review 40.2 (1960): 140-43. Print.

CSM Inside the Numbers

Busy Crowd

If you were at CSM in San Antonio last week, you know this conference was big – in a variety of ways. The APTA touted record attendance levels. The conference was spread out among a huge convention center, with concurrent sessions in two additional hotel centers. Overflow viewing screens had to be set up in the hallways to accommodate full sessions. The exhibit hall was sold out and always packed. The conference hashtag, #APTACSM was even trending at the #2 spot on Twitter for some time. I guess everything really is bigger in Texas. Let’s investigate the growth of this conference, and who actually attends.

CSM 2017 continued to set attendance records this year and has been growing steadily in popularity in the profession. Reports of total attendance have varied for the conference, with talk of over 14,000 in San Antonio. Erin Wendel-Ritter, Manager of Media Relations and Consumer Communications for the APTA, reported registration was over 11,600* for conference attendees. That is a lot of PTs, PTAs, and SPTs! While the number itself is impressive, how does it break down to actual membership? Dr. Sharon Dunn, President of the APTA, tweeted that the Association is at ~98,000 members, with a drive to get to 100k by the NEXT Conference in June. That equates to roughly 11.8% of members attending CSM. There are a variety of reasons why members do not attend yearly conferences, including registration cost, travel, and time off work.

I think we can be more involved as a profession – 11.8% is good, but we can most certainly do better. As Dr. Dunn notes, it starts with increasing the membership of the APTA. Even if we stay at 11-12% attendance, an annual increase in membership of 3% would increase the attendance by roughly 1,000 registrants in 2018. This is no small task, as the rates of membership among other national healthcare organizations, such as the AMA, have suffered recent setbacks in membership rates. From an overall profession standpoint, in 2014 the Bureau of Labor Statistics reported that our profession encompassed around 292,130 Physical Therapists and Physical Therapist Assistants. From that point of view, CSM draws only about 4% of Physical Therapy professionals to attend. And that does not include students.

The student attendance at CSM 2017 was staggering. At times, it almost seemed like a student conference. Erin reported that student registrants accounted for over 4,100* of the total attendees! Student attendance was 35% of the total conference attendance. I think this is great – sort of. CSM is obviously doing a great job of attracting young professionals to a growing conference. Hopefully, they realize the value in the education and networking opportunities and continue to attend as professionals. Students are the future of our profession, and our profession is arguably the future of healthcare. The downside, however, is that it knocks down the number of actual practicing PTs that are attending this conference. If we take students out of the equation, then only about 7,500 practicing PTs and PTAs were in attendance or about 2.5% of the actual PT workforce.

So where do we go from here? The obvious answer is to encourage membership and active participation in the APTA. We can learn a lesson here from the AMA as well, their membership has started to increase in 2015 after a decade-long decline. How did they do it? By attracting student members and becoming more involved with academic institutions. Another solution is to continue to encourage PT professionals to share their voice on social media, which may create FOMO for those not in attendance. I expect students will continue to play a huge role in the development and growth of CSM as a conference in the years to come, and I hope that they continue to be active as graduate Physical Therapists.

*Initial numbers reported to PT Think Tank at the time of publishing. Final attendance numbers will be released on 3/6/17, at which time this article will be updated.

Chronic Whiplash: Is it really a Medical Mystery?

neckpain copy

A small while ago, the well-known and widely read periodical, The Atlantic, published a piece entitled, Chronic Whiplash is a Medical Mystery.

In the article, the author, Julie Beck, poses the thematic question, “Being jostled in a car accident should only cause a few weeks of pain—so why do some people suffer longer?” Well, that is a good question, isn’t it? For many accident victims, the recovery process extends far beyond initial medical treatment, often requiring a comprehensive life care plan to address ongoing medical care, rehabilitation, and support services.

Over the past decade, tremendous advances in the science related to Whiplash and Whiplash Associated Disorders (WAD, as it were) have been achieved. Recently, this science took a giant step forward with the publication of Part I of a two-part special series dedicated to whiplash in the Journal of Orthopaedic and Sports Physical Therapy (October 2016 issue). This issue featured guest editors, Drs. Jim Elliott, Dave Walton, and Michelle Sterling and an editorial by Gwen Jull. Heavy hitters for sure. When it comes to accidents and injuries even if it is the ones that the injures in a truck accident on the highway there are lawyers to protect and get justice. People can check experienced moto accident attorney here if they need help with legal accident procedures. Injured in a car accident? The personal injury lawyers from Kogan & DiSalvo law firm can help.

Consult with a Racine truck accident attorney if you have been injured in a road accident involving a commercial truck. Contact the The Law Offices of Robert T. Edens to hire an attorney who will help ensure that your rights will be protected while filing a claim. Injured in Bakersfield? Call the personal injury lawyer from Johnson Attorneys Group.

So, it’s not surprising that some of these researchers took notice of Beck’s article in The Atlantic. It’s also not surprising that to these researchers, whiplash might not be the mystery it may seem to others. And so, without further ado, PTThinkTank.com is proud to publish a response piece to Beck’s article, entitled, “Chronic Whiplash: Is it really a Medical Mystery?” Well, that is a good question too, now isn’t it?

Enjoy the essay from Jim Elliott, Peter McMenamin, and Dave Walton. Thank you, sirs, for the contribution.

Chronic Whiplash: Is it really a Medical Mystery?

Physical Therapy Metrics

With the widespread use of EMR, more and more data is being collected about the way we practice. A recent post on the Four Hour Work Week by Eric Ries, has me thinking about metrics, specifically PT metrics and how they relate to the care I provide, and the experience my patients have. Eric breaks business metrics down into two types: vanity metrics and action metrics. Vanity metrics is the data that “might make you feel good, but they don’t offer clear guidance for what to do.” On the other hand, action metrics help us make decisions and give us valuable information about our practice. Traditionally metrics in the PT world can generally be broken down into 3 categories: billing, productivity, and referral metrics. More specifically, lets explore how vanity and action metrics relate back to individual (not company wide) practice.

Vanity Metrics: Private practice owners might argue that “no data is bad data” when it comes to tracking patients and therapist performance in the clinic. However, some data points simply do not provide an accurate picture of individual therapist performance, and could be better suited when applied to company performance, or ignored altogether.

  • Visits per case/referral: In my opinion, this data set is the most inconclusive of all metrics commonly tracked to individual PTs in EMR programs. The general rule-of-thumb for most private practices is that the visits per referral number should be between 10-12. This depends on several factors: skill level of therapists; number of post-operative referrals, geographic location, patient population/SES, referral source, clinic reputation, and the list goes on and on. I have found this metric has no bearing on patient outcomes, or patient/physician satisfaction. If you can obtain the same outcomes in 6-8 visits versus 10-12, your patients will be happier, and your referral sources will be impressed. In return, you see a higher volume of new evaluations – which means more and more happy patients.
  • Incomplete metrics: Other metrics that are commonly applied to individual PTs are actually “incomplete,” or too variable to apply to individual performance. For example, scheduling related metrics, such as cancellation and no-show rates, are mostly out of the control of the therapist and do not reflect on the quality of care provided. Obviously, a good clinician that creates buy-in, demonstrates value, and has good outcomes will generally have a low cancel rate. But, cancellation rate does not always reflect productivity – a clinician with a cancellation rate of 4% does not mean they are more effective than a therapist with a cancellation rate of 10% – this variation could easily be due to scheduling, clinic hours, weather, traffic, or an entire host of other variables.

Action Metrics: Action metrics are the data that should be used to evaluate therapist performance and patient outcomes. These metrics help the decision making process, and can demonstrate value to your referral sources and the general public.

  • Plan of Care (POC) complete to Discharge: Perhaps the most under-tracked, but most important data point is patients who complete a POC to discharge. Generally this happens when appropriate care is provided (regardless of number of treatment sessions), goals are met, and functional limitations are eliminated. The therapist and the patient are on the same page, and the patient is happy with the care they receive. And happy patients produce more business – not only by word of mouth and leaving reviews online, but also by telling their physician about the quality of care they received. A high percentage in this metric indicates that the clinician provides quality care and communicates well with their patients.
  • Units/visit: Another metric that is highly variable depending on the patient population and insurance type, but useful nonetheless is units per visit. Tracking units/visit at the provider and company level is beneficial – this serves to make sure therapists are not under-billing; which is all too common in PT practice. It also allows therapists to make sure they are not over-billing, which may make you more susceptible to audits. This metric also allows for more accurate clinic budgeting and forecasting income.
  • FOMs: Tracking change by using functional outcome measures is critical to evaluating therapist performance and patient outcomes. Functional outcome measures should be used with every patient, every time. However, accuracy requires that valid measures are being used, and that measures are used with the correct patient population. Understanding MCID and MDC for each measure is also important. These metrics should also be used to support Functional Limitation Reporting. In addition, physicians and referral sources often use and understand these measures, easing the communication gap while marketing to potential referral sources.
  • New patients per therapist/requested therapist: Another under-tracked and under-utilized metric is new evaluations per therapist. Particularly, patients who request a therapist by name are often more satisfied with the care they receive and more likely to complete their recommended course of therapy. I find this number often correlates with patients who complete their POC to discharge, looping back into the cycle of happy patients and word of mouth referrals.

When extrapolated across a group of therapists in a company or clinic, action metrics provide a more meaningful picture of how valuable our services are. Individually, vanity metrics can be misleading and provide little value as to the value and productivity of a therapist.  Eric Reis encourages us to “measure what matters” – meaning that more data is not always better, and argues that the key to having actionable metrics is “having as few as possible.” It can be tempting with EMR to look at a seemingly endless set of metrics, but narrowing our focus on a few can provide better insight into therapist, clinic, and business performance. How do you use metrics in your clinic? Which ones are used to evaluate individual performance?